分类: health

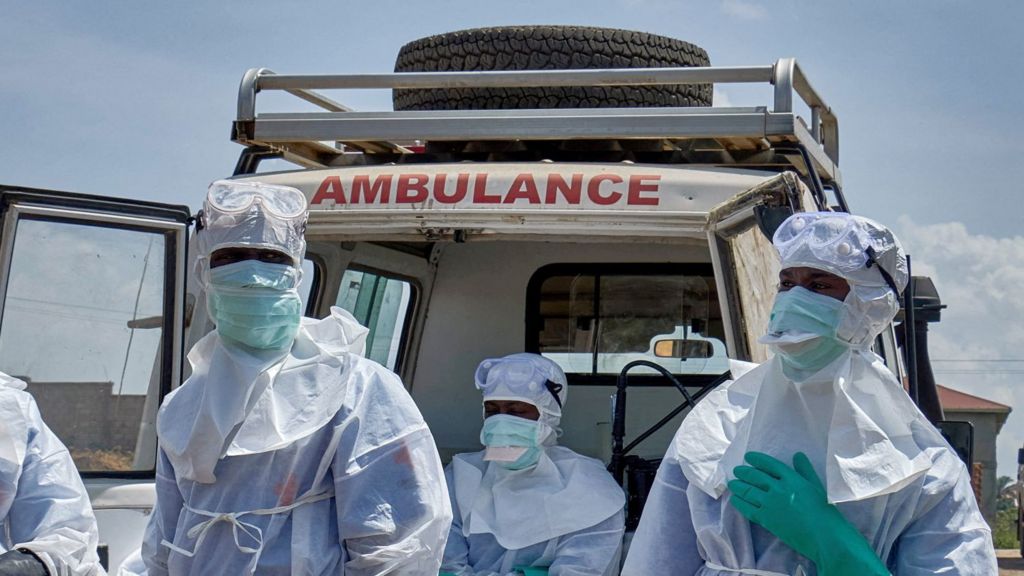
  • France confirms first Ebola case

    France confirms first Ebola case

    In a development that marks the first confirmed Ebola case on European soil, France has announced that a doctor returning from a humanitarian deployment in the Democratic Republic of the Congo (DRC) has tested positive for the deadly virus. The French Ministry of Health disclosed Wednesday that the infected medic was promptly isolated and admitted to a specialized treatment facility, where the patient currently remains in stable condition. The outbreak currently ravaging eastern DRC was formally declared by public health authorities last month, but epidemiologists have confirmed the virus had been quietly spreading in local communities for several weeks prior to the official announcement.

    As of the latest updates, the outbreak has already claimed more than 260 lives across the central African nation, with over 1,000 confirmed total infections. While this is the first confirmed Ebola case detected in Europe, an American healthcare worker who tested positive in DRC was transported to Germany for care just last month. Cross-border spread has already reached neighboring Uganda, where the World Health Organization (WHO) has documented 20 confirmed infections and two recorded deaths.

    Public health officials have moved quickly to reassure the general public that broad population risk remains minimal. French authorities emphasized the overall risk to French citizens is “very low”, a sentiment echoed by WHO Director-General Tedros Adhanom Ghebreyesus, who stated global risk remains low and there is no justification for widespread public panic. Contact tracing operations are currently active to identify and monitor all individuals who may have had close exposure to the infected French doctor.

    Healthcare workers on the frontlines of the outbreak response face disproportionately high danger, as Ebola spreads through direct contact with infected bodily fluids. Last week, WHO data revealed 17 out of 75 healthcare workers who contracted the virus in DRC have died from their infections. A complicating factor in this outbreak is that it is driven by the Bundibugyo strain of Ebola, for which no widely approved vaccine currently exists.

    In response to the imported case, France has activated a dedicated monitoring system to track all aid and humanitarian workers returning from DRC. Both the Africa Centres for Disease Control and Prevention (Africa CDC) and United States public health agencies have warned that the ongoing outbreak has the potential to become one of the largest Ebola events on record if containment efforts are not scaled up rapidly.

    Confirmed cases in DRC are currently concentrated in three eastern provinces: Ituri, North Kivu, and South Kivu. Ituri remains the epicenter of transmission, accounting for more than 90 percent of all confirmed infections. Persistent armed conflict in the region has severely hampered outbreak response efforts, according to WHO. The M23 rebel group maintains control over large swathes of both North and South Kivu, making it difficult for response teams to access affected communities, conduct surveillance, and deliver care to infected patients.


  • French health ministry confirms Ebola virus in patient who worked in Congo

    French health ministry confirms Ebola virus in patient who worked in Congo

    On Wednesday, French health authorities announced the country’s first confirmed Ebola case linked to the ongoing outbreak in the Democratic Republic of Congo, marking a worrying cross-border spread of the currently untreatable virus. The unnamed patient, who had just completed a humanitarian deployment in one of Congo’s active Ebola transmission zones, was quickly taken into specialized medical care immediately after entering French territory.

    According to the French Ministry of Health, the patient is currently in stable condition, and all required infection control protocols were activated from the moment the case was flagged. Strict isolation protocols were implemented, and the patient was transported to a specialized treatment facility via secure pathways designed to eliminate any risk of community contamination. Public health teams have also launched a full epidemiological investigation to track down every person who may have had close contact with the infected individual. All identified contacts will be placed under 21-day at-home isolation, a period matching the virus’s maximum incubation window, and monitored closely for any early symptoms of infection.

    The case comes as Congo grapples with a growing public health crisis that has so far recorded 1,094 confirmed Ebola infections and 277 confirmed deaths, according to Congolese health ministry data. What makes this outbreak particularly dangerous is that it is caused by the rare Bundibugyo Ebola strain, for which no approved vaccines or specific antiviral treatments currently exist.

    Outbreak officials have warned that the true caseload is likely much higher than official counts, as many infections in remote affected areas remain undetected. Since the outbreak was first officially declared on May 15, transmission has continued to accelerate, and experts caution that the worst of the crisis is still ahead. This imported case in France underscores the ongoing global risk posed by unmanaged Ebola outbreaks in central Africa, even as wealthy nations maintain robust systems to contain the virus after it crosses their borders.

  • Kenya minister found in contempt of court over US-backed Ebola centre

    Kenya minister found in contempt of court over US-backed Ebola centre

    In a high-profile legal ruling that has amplified tensions around a controversial public health project, Kenya’s Health Minister Aden Duale has been convicted of contempt of court for violating a court order to halt construction on a US-funded Ebola quarantine facility in Nanyuki.

    Last month, Kenya’s High Court issued an immediate stop-work order for the 50-bed isolation center, which is planned to be built on a local military base. The order paused all construction until the court could hear a legal challenge brought by Kenyan rights organization the Katiba Institute. But in Monday’s ruling, Justice Patricia Nyaundi confirmed that Duale had deliberately ignored the court’s command and permitted construction work to continue uninterrupted. Sentencing for Duale is scheduled to be handed down on Tuesday.

    The facility, funded through a US regional Ebola response package, is designed to quarantine US citizens suspected of exposure to Ebola during the ongoing outbreak centered in the eastern Democratic Republic of Congo. The project has sparked widespread public outrage and mass protests across Nanyuki, a town located roughly 140 kilometers north of Kenya’s capital Nairobi. Three people have been killed during clashes between demonstrators and police, who were deployed to disperse the crowds. Among the fatalities is 17-year-old high school student Sylvester Muigai Ndung’u, who had hoped to train as a Catholic priest. Witnesses report the teenager was shot in the head during the unrest, though police have stated they are waiting for post-mortem results to confirm the cause of his death, and have not yet responded to accusations that officers used excessive force against unarmed civilians.

    The Katiba Institute first filed its legal challenge to halt construction in May, warning in its petition that the facility poses “grave and imminent risks” to Kenyan public health. Following the stop-work order, Kenya’s Ministry of Health attempted to defend its actions by claiming it had not violated the court’s ruling. The ministry argued any ongoing work was being carried out independently by the Kenyan government, in the national interest of protecting Kenyan citizens from potential Ebola exposure. Justice Nyaundi rejected this justification outright in her ruling, stating the government cannot “avoid compliance by recasting or re-characterising the ongoing construction”. She emphasized that a court order “is not an invitation to ingenuity – it is a command to be obeyed”, and confirmed Duale clearly understood the requirement to stop all work at the Nanyuki site, yet chose to allow construction to proceed.

    In recent weeks, Kenyan President William Ruto has publicly defended the quarantine facility project. Ruto stated he received an official request from the US government to host the center, and argued that turning down the request would be “inhuman”. He has also urged Kenyan politicians not to politicize the Ebola response, calling for an end to “reckless” rhetoric around the project.

    As of Monday, Kenya had not recorded any confirmed cases of Ebola. The ongoing outbreak is concentrated in the Democratic Republic of Congo, where more than 1,000 confirmed cases have been recorded, with an additional 20 confirmed cases reported in neighboring Uganda, nearly all of which are imported from DR Congo. Notably, the outbreak epicenter in Bunia, DR Congo is more than 780 kilometers from Nanyuki, with Uganda lying between the two locations.

    The project has also faced fierce pushback from the Kenya Medical Practitioners, Pharmacists and Dentists Union (KMPDU), one of the country’s largest medical professional associations. Union leaders have publicly questioned why Kenya was selected to host a quarantine facility for exposed American workers, amid an outbreak centered hundreds of kilometers away in another country. KMPDU Secretary General Davji Bhimji Atellah stated the union “will not sit back and watch Kenya be treated as a containment colony for a lethal pathogen that we did not generate”.

    A spokesperson for US Secretary of State Marco Rubio confirmed that Washington has committed $13.5 million (£10.7 million) to fund Kenyan Ebola preparedness initiatives, including the Nanyuki facility. That funding is part of a broader $112 million US commitment to support regional Ebola outbreak response across Central and East Africa.

  • DR Congo Ebola cases top 1,000

    DR Congo Ebola cases top 1,000

    KINSHASA, June 22 — Health authorities in the Democratic Republic of the Congo (DRC) announced in an updated epidemiological briefing on Sunday that the total number of confirmed Ebola cases across the country has crossed the 1,000 threshold, marking a worrisome milestone in the ongoing outbreak.

    Latest official data released by the DRC Ministry of Health puts the current cumulative confirmed caseload at 1,003. As of the update, the outbreak has claimed 254 lives, bringing the overall case fatality rate to 25.3 percent. Of the active cases, 365 patients are currently receiving care in isolation facilities or hospital wards, while 100 people who contracted the virus have successfully recovered and been discharged.

    The outbreak is concentrated across three provinces in the eastern part of the country, where public health teams are working to trace all close contacts of confirmed cases to slow transmission. Current data shows that just 58 percent of identified contacts are successfully being monitored and followed up, a gap that response teams are working to address.

    Even as case numbers continue to climb, health authorities emphasize that all outbreak response operations remain fully active. Response measures include enhanced pathogen surveillance at border crossings and community levels, expanded public outreach and education campaigns to raise awareness of transmission risks, and ongoing work to boost clinical case management and expand diagnostic testing capacity across affected regions. The photo provided, captured on June 16 at an Ebola treatment center in Rwampara, eastern DRC, shows frontline health workers drying disinfected protective gloves ahead of their next shift caring for patients.

  • Confirmed Ebola cases in Congo outbreak top 1,000 with 254 deaths, authorities say

    Confirmed Ebola cases in Congo outbreak top 1,000 with 254 deaths, authorities say

    BUNIA, Democratic Republic of Congo — A worsening Ebola outbreak in the eastern region of the country has hit a grim new milestone, with confirmed infections climbing to 1,003 and confirmed deaths totaling 254, according to an official statement released by Congolese health authorities late Sunday.

    Since the outbreak was first declared on May 15, the virus has been concentrated primarily in Ituri province, where 100 infected patients have successfully recovered to date, the Congolese Ministry of Health confirmed.

    What makes this outbreak particularly alarming is that it is driven by the rare Bundibugyo Ebola virus, a strain for which no approved vaccines or specific targeted treatments currently exist. In its first month of spread, the outbreak already became the most severe recorded event caused by this specific strain, and health officials have acknowledged that the true scale of the crisis is likely far larger than current confirmed numbers suggest. Many unreported cases are still undetected across the affected region, and top health leaders warn that the outbreak has not yet reached its highest point.

    Contact tracing, a core public health intervention to stop Ebola transmission, remains a major unmet challenge for local response teams. As of the latest update, only 55 percent of required contact tracing has been completed across the affected zone. Compounding these challenges, response teams have not yet been able to identify the index case, also known as patient zero, that sparked the current outbreak. As of last week, more than 35,000 people who have had documented exposure to infected individuals are still awaiting contact tracing and monitoring.

  • DR Congo reports 956 confirmed Ebola cases, 247 deaths

    DR Congo reports 956 confirmed Ebola cases, 247 deaths

    KINSHASA – A public health emergency in the eastern Democratic Republic of the Congo (DRC) continues to escalate, with official data releasing Saturday showing confirmed Ebola infections have climbed to 956, and the cumulative death toll from the outbreak has reached 247. The update comes from the country’s national health authorities in their latest epidemiological situation report.

    On Friday alone, 23 new positive Ebola diagnoses and two additional fatalities were recorded across two high-risk eastern provinces: Ituri and North Kivu. Ituri, the current epicenter of the outbreak, bears the overwhelming majority of the national caseload, with 874 confirmed infections and 201 deaths accounting for over 91 percent of all confirmed cases nationwide.

    Per the report, 92 patients have successfully recovered from the virus and been discharged from care, while 361 confirmed patients are currently undergoing isolation or inpatient treatment at designated health facilities. An additional 162 people are under investigation as suspected cases as of Friday. One key gap in the national outbreak response has been identified: the contact-tracing rate, which currently sits at just 69.3 percent, far below the 95 percent target health officials set to effectively interrupt chains of virus transmission.

    During a press briefing held Friday evening, DRC Health Minister Roger Kamba confirmed that the outbreak is still in an expansionary phase. Kamba noted that as response teams scale up active case searching operations and extend their reach into more remote, heavily affected communities, further increases in confirmed case counts are expected in the coming weeks.

    The health minister added that public health officials will not be able to declare the outbreak has reached its peak, plateaued, or entered a decline until weekly case counts show consistent stabilization or a sustained downward trend. Until that point, Kamba emphasized, all core response efforts including aggressive case detection, immediate patient isolation and treatment, and deeper community engagement must be sustained and expanded.

    This current outbreak, caused by the rare Bundibugyo strain of the Ebola virus, was first officially declared by DRC public health authorities on May 15 this year.

  • Australia confirms first case of H5N1 bird flu as virus reaches every continent

    Australia confirms first case of H5N1 bird flu as virus reaches every continent

    In a landmark development that marks the global reach of one of the world’s most persistent avian viral threats, Australia’s Ministry of Agriculture has formally confirmed the first detection of the highly pathogenic H5N1 bird flu strain on the country’s mainland. This detection closes the final geographic gap in the virus’s global spread, meaning the contagious variant has now been identified on every continent on Earth.

    Agriculture Minister Julie Collins announced Saturday that the virus was isolated from a brown skua, a migratory seabird discovered on a beach in Western Australia’s remote Cape Le Grand National Park. The park lies roughly 700 kilometers southeast of Perth, near the coastal town of Esperance. A second suspected case is also under investigation: a southern petrel found weakened on the same Esperance coastline, though officials stressed that no evidence of large-scale wildlife mortality has been recorded to date.

    Australia was long the final continent without confirmed H5N1 detection on its mainland, though the virus was previously identified on Australia’s remote southern Indian Ocean territories of Heard Island and McDonald Islands back in October 2024. A new study released earlier this week revealed the devastating impact of that outbreak: it estimates that more than 75% of the baby seal population on Heard Island – around 13,000 out of a total 17,000 pups – have died from H5N1 infection since last August. Researchers also recorded abnormally high mortality rates among local penguin populations on the territory.

    Scientific analysis points to migratory wild birds from the French-administered Crozet Islands, located roughly 1,800 kilometers from Heard Island, as the likely source that introduced the virus to the remote territory last August. That same pattern of migratory spread is what Australian officials believe led to the new detection on the mainland.

    H5N1 first emerged in southern China in the late 1990s, and has since become the dominant strain of bird flu circulating in wild bird populations globally. The virus spreads rapidly through both wild avian populations and domestic poultry flocks, and in rare cases has expanded to infect other mammal species including seals, otters, and foxes. While human infections are extremely uncommon – almost all tied to direct close contact with infected animals – global public health authorities have long monitored the strain’s spread closely for its potential to mutate into a form more transmissible to humans.

    Australian authorities have emphasized that they were prepared for this detection. National Chief Veterinary Officer Beth Cookson noted that emergency planning for an H5N1 incursion has been underway for years, and the national emergency animal disease committee convened immediately on Saturday to coordinate response efforts. Threatened Species Commissioner Fiona Fraser told ABC that initial testing results to confirm whether the virus has spread to other local animal populations are expected within the next few days. “We all knew we couldn’t remain bird flu-free forever,” Collins told reporters at Saturday’s press conference, framing the detection as an expected event that the country was equipped to manage.

  • Africa CDC chief says the continent needs to invest its own funds in Ebola response, vaccine

    Africa CDC chief says the continent needs to invest its own funds in Ebola response, vaccine

    ADDIS ABABA, Ethiopia – The African continent’s leading public health body has issued an urgent call for African governments to ramp up domestic financing to contain the ongoing Ebola outbreak spreading across the Democratic Republic of the Congo (DRC) and Uganda, while stressing the critical need to end the continent’s long-standing reliance on international partners for emergency health responses. Since the outbreak was first detected on May 15, the Africa Centers for Disease Control and Prevention (Africa CDC) confirms it has already killed more than 200 people among 894 confirmed cases, with more than 35,000 exposed contacts still to be fully traced. Public health experts warn the actual case count is likely higher, as the outbreak was only identified weeks after it first began spreading through local communities.

  • Mourners bury a 6-month-old Ebola victim in the Congo outbreak’s 3rd orphanage death

    Mourners bury a 6-month-old Ebola victim in the Congo outbreak’s 3rd orphanage death

    BUNIA, Democratic Republic of Congo – On a somber Friday morning in eastern Congo, hundreds of mourners gathered to lay to rest a six-month-old girl, the latest fatality from the country’s escalating Ebola outbreak and the third child from a local orphanage to lose their life to the virus in recent weeks. As the small pine coffin was carried to its final resting place, attendees held small wooden crosses and stood several meters apart to reduce infection risk, while only trained health workers clad in full personal protective equipment (PPE) – including face masks, thick gloves, and fluid-resistant gowns – were permitted to lower the casket. A Catholic priest led the brief funeral service, offering prayers for the infant and comfort to grieving community members.

    “It is a profound sadness to lose one of our own, a child of this congregation,” said Father Innocent Ndogo, opening the service. “As we have always believed, the Lord gives, and the Lord takes away.”

    The ongoing outbreak, caused by the rare Bundibugyo strain of Ebola, is centered in Congo’s Ituri region, which has recorded more than 90% of all confirmed cases to date. Efforts to contain the spread have been severely hampered by repeated community clashes with response teams, rooted in longstanding distrust of public health measures and anger over altered burial practices that are required to stop transmission. The outbreak response has also faced criticism for its occasional militarization, which has further alienated local populations.

    Unlike the more common Zaire strain of Ebola – which has driven 16 of Congo’s previous outbreaks and has an approved, effective vaccine – the Bundibugyo strain has no licensed treatment or preventative vaccine. For many frontline workers, even basic PPE remains in short supply, leaving them exposed to the virus as they carry out critical contact tracing and safe burial work. Early in the outbreak, diagnostic testing for Bundibugyo was not widely available, meaning cases were misidentified as the more common Zaire strain, allowing the virus to spread undetected for weeks – a gap that public health officials now cite as a key reason for the outbreak’s current scale.

    During an official visit to Bunia on the same day as the funeral, Congolese Health Minister Roger Kamba released the latest official case count, confirming 933 confirmed infections and 245 deaths across affected regions. To expand access to care, Kamba announced that all healthcare facilities in Ituri would offer free Ebola-related treatment moving forward, and that hazard pay bonuses for frontline healthcare workers would be doubled to retain critical staff during the crisis.

    Africa Centres for Disease Control (Africa CDC) updated their contact tracing data a day prior, reporting that more than 35,000 people who may have been exposed to the virus are currently being monitored, one of the largest contact tracing operations the continent has seen in recent years. While the current outbreak has caused hundreds of deaths, it remains far less severe than the 2014 West African Ebola epidemic that killed more than 11,000 people across multiple countries.

    Alex Lock, communications officer at the International Federation of Red Cross and Red Crescent Societies, which is supporting the outbreak response, warned against global indifference to the crisis, noting the human cost of each new case. “She was a baby. She had her whole life ahead of her. Unfortunately, she was taken by the disease, a disease that, as you know, is transmitted from one person to another,” Lock said, emphasizing the urgent need for additional global support.

    Though the outbreak is concentrated in Ituri, cases have now been recorded in neighboring North Kivu and South Kivu provinces, and the virus has crossed the international border into Uganda. Ugandan health authorities have confirmed 19 cases and two deaths linked to the Congo outbreak, prompting regional public health alerts. Donors and global health organizations have begun deploying additional resources, but many response teams warn that more support is urgently needed to stop the outbreak from spreading further across East Africa.

  • Six-year-old Ebola patient taken from DR Congo hospital found and ‘doing well’

    Six-year-old Ebola patient taken from DR Congo hospital found and ‘doing well’

    An ongoing Ebola outbreak in eastern Democratic Republic of the Congo (DRC) took an unexpected turn earlier this week, when a 6-year-old confirmed Ebola patient—abducted from her treatment ward by armed men alongside her mother—has been located and is reported to be in stable condition. Local health official Dr. Lubambo Maboko Gaston confirmed the update to the BBC on Friday, two days after he first announced the abduction that drew international attention to growing unrest around Ebola response efforts in the region.

    According to Dr. Gaston, the pair were taken by a group of armed, angry men from a hospital in Butembo, a major city in eastern DRC, on Monday. It remains unclear whether the abductors had prior personal connections to the child or her family, but the abduction fits a pattern of rising hostility toward Ebola treatment facilities that has hampered outbreak response for weeks. On Friday, the girl and her mother voluntarily arrived at an alternative Ebola treatment center located roughly 18 kilometers outside Butembo, where medical teams have since assessed the child’s condition as stable and improving. “Her condition is currently considered stable,” Dr. Gaston confirmed in a statement to reporters.

    Hostility toward outbreak response teams is not a new development during this outbreak. To date, the event has killed more than 230 people and recorded 890 confirmed cases across eastern DRC, with treatment centers facing repeated attacks from local communities driven by fear and misinformation. Just last month, police in Mongbwalu were forced to fire warning shots into the air to disperse angry crowds that attempted to seize the bodies of Ebola victims from a local health facility. Days prior, residents of Rwampara, a small town 85 kilometers southeast of Mongbwalu, set fire to hospital isolation tents after officials blocked them from retrieving the body of a man who had died from suspected Ebola.

    Public health experts stress that the bodies of Ebola victims carry extremely high viral loads, and unsanctioned burial preparations are a major driver of new transmission. Safe, regulated burial protocols are one of the most critical tools for containing spread, but deep-rooted misinformation has left many local residents distrustful of these measures. “People are not properly informed or sensitised about what is happening,” local politician Luc Malembe explained to the BBC last month. “For a certain segment of the population, especially in remote areas, Ebola is an invention by outsiders – it does not exist. They believe it is the NGOs and hospitals creating this to make money, and this is tragic.”

    The outbreak was officially declared by DRC authorities on May 15, though public health officials later confirmed that transmission had gone undetected in remote communities for weeks before the declaration. A complicating factor for response teams is that the outbreak is caused by Bundibugyo, a rare strain of Ebola that currently has no approved vaccine. The World Health Organization (WHO) has projected it could take months to develop and deploy an effective vaccine for this strain.

    The scale of the outbreak has already drawn grim projections from global health leaders. This week, the head of the Africa Centres for Disease Control and Prevention warned that the outbreak could become one of the largest Ebola events in recorded history, echoing an earlier assessment from the U.S. Centers for Disease Control and Prevention. Cross-border spread has already been recorded in neighboring Uganda, which has confirmed 19 cases and two deaths since the outbreak began. However, the WHO reported this week that Uganda has not recorded any new confirmed cases since June 5, a hopeful sign that containment measures there are working.

    In DRC, the national ministry of health has said it is ramping up core response measures, including expanding community surveillance, scaling up contact tracing, and building out dedicated treatment infrastructure across affected towns. The WHO has committed $3.9 million to response efforts, while Africa CDC has approved a $319 million budget to support coordinated action across the region.

    Nearly all confirmed cases are concentrated in three eastern DRC provinces: Ituri, South Kivu and North Kivu—the same region where the 6-year-old patient was abducted. Ituri remains the epicenter of transmission, accounting for more than 90% of all confirmed infections. Ongoing armed conflict in the region has created additional barriers to effective response, the WHO has warned. The M23 rebel group currently controls large swathes of both North and South Kivu, leaving response teams unable to access many remote communities where transmission may be spreading undetected.