分类: health

  • ‘Miracle on the Hudson’ pilot Captain Sully diagnosed with Alzheimer’s disease

    ‘Miracle on the Hudson’ pilot Captain Sully diagnosed with Alzheimer’s disease

    Seventeen years after he pulled off one of the most miraculous emergency landings in modern aviation history, retired Captain Chesley “Sully” Sullenberger III — the pilot who saved all 155 lives aboard US Airways Flight 1549 — has announced he is living with early-stage Alzheimer’s disease. The 75-year-old aviation icon shared the diagnosis in a heartfelt public post on his personal website Tuesday, opening up about his early symptoms and his decision to speak out to destigmatize the neurodegenerative condition.

    “For now, this means a name may not come easily to me, I forget a story I have recently told, or I don’t sleep as well, but I am in the beginning of this long journey,” Sullenberger wrote in his post.

    Sullenberger cemented his place as a national hero on January 15, 2009, just minutes after Flight 1549 departed New York’s LaGuardia Airport for Charlotte, North Carolina. The plane struck a flock of Canada geese shortly after takeoff, disabling both of its jet engines in an instant. With too little altitude to reach a nearby airport and a high risk of crashing into densely populated Manhattan neighborhoods, Sullenberger made a quick, life-saving decision to ditch the aircraft intact in the frigid waters of the Hudson River. Thanks to his calm expertise and split-second decision-making, every passenger and crew member on board survived the incident, which quickly became known across the globe as the “Miracle on the Hudson.”

    A former U.S. Air Force fighter pilot with 40 years of flying experience when the emergency landing occurred, Sullenberger retired from commercial aviation in 2010, one year after the incident. He never stepped back from public life, however, continuing a decades-long advocacy work to improve aviation safety standards across the industry. In 2016, his extraordinary feat was adapted into the Clint Eastwood-directed Hollywood feature film *Sully*, starring Tom Hanks as the quick-thinking captain.

    In his latest announcement, Sullenberger reflected that his Alzheimer’s diagnosis has forced him to reexamine what it means to live a life of service. His conclusion, he said, was to speak openly about his experience rather than stay private. Echoing the words he has shared for years about the 2009 emergency, he emphasized that courage is a contagious force that can bind communities together.

    “Over the years, when people would ask about the successful outcome of Flight 1549, I would say that ‘courage can be contagious,’ and on that day it helped everyone band together to get everyone off that airplane successfully,” he wrote. “Now we need that courage to battle this disease. I am now part of a larger community with many of you, and we will be courageous together.”

  • ‘Explosive diarrhoea’ outbreak remains a mystery as officials struggle to find sources

    ‘Explosive diarrhoea’ outbreak remains a mystery as officials struggle to find sources

    A summer outbreak of cyclosporiasis, a parasitic infection spread via contaminated food and water, has spread across 31 U.S. states and sickened more than 3,000 people, leaving public health experts scrambling to identify its source and slow transmission amid unique investigative challenges and strained public health resources.

    The illness, which is rarely fatal, is defined by its primary symptom: severe, watery diarrhea that strikes abruptly. As of current reports, Michigan has borne the brunt of the outbreak with more than 2,600 confirmed cases, followed by New York State with a smaller but still significant caseload. Despite weeks of investigation, health officials have not yet pinpointed the original contaminated source of the parasite, and have only issued general guidance to the public: thoroughly wash all produce, avoid certain high-risk fruits including raspberries, and cook vegetables thoroughly to destroy the pathogen.

    Public health investigators have described tracing the parasite as an extraordinarily difficult task, compounded by multiple biological and systemic barriers. “This isn’t like detecting a needle in a haystack. It’s like detecting a microscopic portion of a needle in a haystack,” explained Steven Manderach, executive director of the Association of Food and Drug Officials, who previously addressed cyclosporiasis outbreaks as a food safety official in Iowa.

    Biologically, the parasite’s long incubation period creates a major hurdle for investigators. Unlike most foodborne illnesses that cause symptoms within hours of consumption, cyclosporiasis takes one to two weeks to trigger illness in infected people, explained Jodie Guest, senior vice chair of epidemiology at Emory University’s Rollins School of Public Health. By the time most people seek care and report their illness, they often cannot recall every food they ate in the preceding two weeks, breaking a key link investigators rely on to trace contamination sources.

    Testing for the parasite in food supplies is also far more labor-intensive and complex than testing for other common pathogens. To isolate cyclospora, investigators must wash massive quantities of potentially contaminated produce to collect any parasite particles present, then concentrate the sample before testing can begin. “You’d have to have truckloads of lettuce to get to that point,” Manderach noted. The broad geographic spread of cases, spanning 31 states, also suggests multiple contamination points in the national food supply, a factor that further complicates coordinated investigations.

    Many public health experts point to recent federal budget and staffing cuts to U.S. Department of Health and Human Services (HHS) agencies as a critical additional barrier to solving the outbreak. As part of Elon Musk’s Department of Government Efficiency cost-cutting initiative, Health Secretary Robert F. Kennedy Jr has implemented widespread cuts that have reduced capacity for key foodborne illness surveillance programs. Most notably, the Foodborne Diseases Active Surveillance Network (FoodNet)—a federal program that previously tracked cyclospora, salmonella, listeria and other pathogens nationwide—scaled back monitoring last year to only track two pathogens, ending its systematic surveillance for cyclospora.

    In an internal memo to the state of Connecticut obtained by NBC News, the CDC acknowledged that “Funding has not kept pace” with the resources required to run the full FoodNet program. Guest, who previously worked on FoodNet operations, explained that the program previously collected patient data, tested food samples from state labs, and collated information at a national level to speed outbreak investigations. “When we see an outbreak or a cluster or something, we don’t have the data we normally expect to go back to use to help us, and this is one of those consequences,” she said. “You’re starting in the dark.”

    HHS officials have pushed back on criticism, telling the BBC that the CDC continues to collaborate with more than 3,000 local and state health departments to collect cyclospora data through alternative surveillance systems, and that overall health funding for foodborne illness work has “remained stable”. However, state health departments across the country report feeling the impact of reduced federal support. In Colorado, which has recorded 90 cases this year in line with typical annual totals, the state health department confirmed it has received less federal funding and operates with fewer staff assigned to case monitoring. “While our colleagues at the CDC are working hard to support state partners, we have had to adapt to federal changes,” said Hope Shuler, a spokesperson for Colorado’s public health department. The state has continued all core testing, monitoring and data reporting to the CDC despite the cuts, she added.

    Not all experts agree that the post-cut system is failing: Manderach noted that federal food safety agencies have largely maintained previous performance standards despite restructuring that began during the Trump administration, adding that “while yes, I do think there were challenges early on, most of those seem to have resolved.”

    Other public health leaders point to competing priorities that have stretched federal resources thin, including the ongoing deadly Ebola outbreak in the Democratic Republic of the Congo that has demanded significant attention and funding. This resource strain has shifted more responsibility for foodborne illness outbreak investigations to state governments, explained Nancy Glick of the National Consumers League. “States are doing that now, but they don’t have the resources that the CDC had,” she said.

    Currently, the core investigative work relies on time-consuming interviews with every person who tests positive for cyclospora, asking them to recount every food they consumed in the two weeks before they developed symptoms. Investigators hope to identify a common contaminated product or exposure point that can be pulled from the market to end the outbreak. But experts note that this work requires extensive staffing, a resource many small local health departments simply do not have available. “It is pretty straightforward, but it takes a lot of person power to do it,” said David Weber, a professor of medicine, pediatrics and epidemiology at University of North Carolina at Chapel Hill.

    For American consumers, the ongoing uncertainty has left them to rely on general prevention measures to avoid the uncomfortable illness. “At the moment, the list of things that you need to be concerned about is unfortunately quite long, making it feel really hard to control,” Guest said.


  • An experimental Alzheimer’s drug shows promise targeting a different brain protein, new study shows

    An experimental Alzheimer’s drug shows promise targeting a different brain protein, new study shows

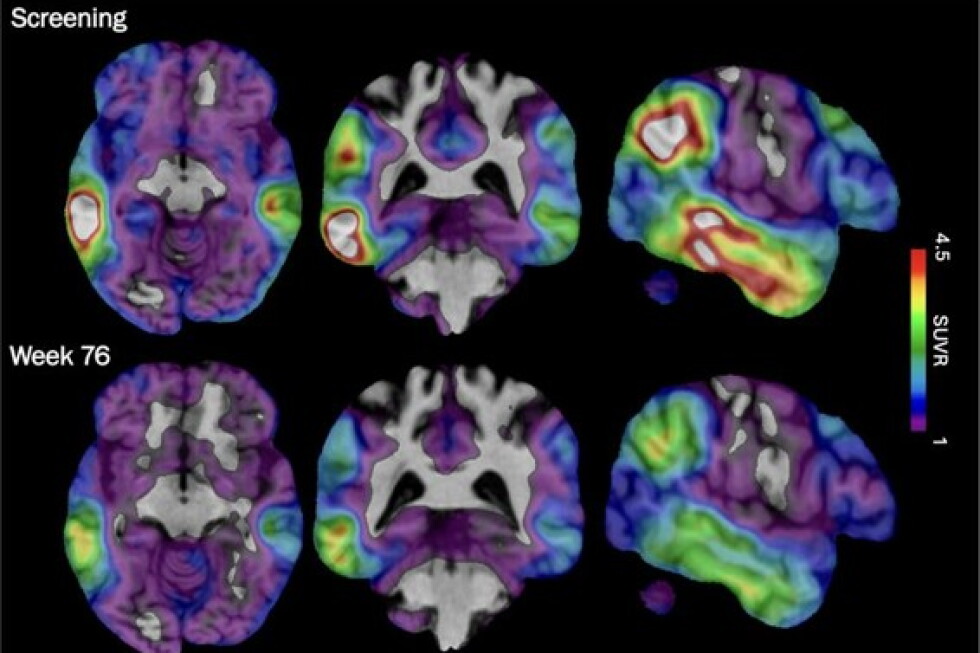
    LONDON – Researchers unveiled groundbreaking new findings Tuesday at the Alzheimer’s Association International Conference, revealing that an experimental drug from Biogen offers a novel path to slow early-stage Alzheimer’s disease by targeting a destructive brain protein long considered difficult to treat. Unlike today’s approved therapies that focus on clearing a different toxic protein linked to the condition, this new candidate works by reducing the production of tau, a protein that forms deadly tangles in neurons and drives cognitive decline.

    Alzheimer’s, the leading cause of dementia worldwide, impacts more than 7 million people in the United States alone and tens of millions globally. For years, the majority of approved treatments have centered on clearing amyloid, a sticky protein that forms plaques in the brain up to two decades before symptoms emerge. While the two currently approved drugs, lecanemab and donanemab, can modestly slow cognitive decline by removing amyloid buildup, scientists have long recognized that amyloid alone does not cause Alzheimer’s. The dominant scientific model holds that amyloid accumulation ultimately triggers abnormal tau to clump into tangles that kill brain cells, making tau a critical yet underexploited target for new therapies. Prior attempts to develop tau-targeting drugs have repeatedly failed, leaving a critical gap in treatment development.

    Biogen’s new candidate, diranersen, works through a fundamentally different mechanism than existing amyloid-focused drugs. Classified as an antisense oligonucleotide, the drug does not attack existing tau buildup; instead, it instructs the gene that produces tau to generate less of the protein. “If you lower tau production, you are lowering the amount of the abnormal tau that needs to be cleared by the microglia, by the clearance mechanism in the brain. And so you are enabling the normal clearance mechanism to have more capacity to clear the tau,” explained Dr. Cath Mummery of University College London, who led the phase 2 study of the drug. Unlike approved amyloid drugs that are delivered via intravenous infusions or injections into the bloodstream, diranersen is administered via injection into the fluid surrounding the spinal cord, providing a more direct route to brain tissue.

    The phase 2 trial enrolled roughly 400 patients with mild cognitive impairment or early-stage Alzheimer’s, who were randomly assigned to receive varying doses of diranersen or a placebo. In an unexpected finding announced earlier this year by Biogen and its development partner Ionis Pharmaceuticals, the lowest dose – given just twice per year – produced the strongest effect, meaning the study did not meet its pre-planned endpoint of demonstrating greater benefit from higher doses. Despite this miss, new data presented this week shows encouraging signs of cognitive benefit: five out of six cognitive tests showed that patients receiving diranersen still experienced cognitive decline, but at a markedly slower rate than patients given a placebo. For the lowest dose group, the decline rate slowed by 26% – a reduction comparable to the benefits seen in clinical trials of approved amyloid drugs.

    Notably, side effects reported in the trial were mild, including injection site pain and temporary confusion that resolved within roughly a week of treatment. Crucially, researchers observed no cases of brain swelling or inflammation, a common and potentially dangerous side effect linked to amyloid-targeting drugs.

    Independent researchers not involved with the Biogen study called the results a promising step forward for the field. “This is really quite promising if it were to hold up” in larger-scale confirmatory testing, said Jessica Langbaum of the Banner Alzheimer’s Institute in Phoenix. While Dr. Reisa Sperling of Mass General Brigham emphasized that the results are still early, she noted that the findings “will reinvigorate interest and investment in lots of tau mechanisms, and the field needs that.” Biogen has confirmed it plans to launch a large-scale phase 3 trial to confirm the drug’s clinical benefit.

    Diranersen is just one of multiple innovative new approaches to Alzheimer’s treatment presented at the conference, reflecting a growing shift in the field toward targeting tau and exploring combination therapies. Last week, the University of California, San Francisco launched the first-of-its-kind Alzheimer’s Tau Platform, a National Institutes of Health-funded study that will test multiple experimental anti-tau therapies, both alone and in combination with approved amyloid treatments. The first candidate to be tested through the platform is AADvac1, a tau vaccine designed to train the body’s immune system to recognize and attack abnormal tau. The platform will expand to sites across the U.S. and will even include patients who have tau and amyloid buildup but have not yet developed cognitive symptoms, allowing researchers to test the potential of early intervention.

    Other researchers are exploring repurposing existing drug candidates for Alzheimer’s prevention. Scientists reported that obicetrapib, an experimental cholesterol-lowering drug, may hold promise for reducing Alzheimer’s protein buildup in people with a genetic risk for the disease. The APOE4 gene, the strongest known genetic risk factor for late-onset Alzheimer’s, also impacts how the body processes cholesterol, leading researchers to hypothesize that cholesterol-lowering drugs could mitigate this elevated risk. NewAmsterdam Pharma, the developer of obicetrapib, plans to launch a clinical trial soon to test this hypothesis in carriers of one or two copies of the APOE4 gene.

    Companies are also advancing new technologies to overcome one of the biggest barriers to Alzheimer’s drug development: penetrating the blood-brain barrier, a protective lining that blocks most large molecules from entering brain tissue. Denali Therapeutics is developing technology that “hitches a ride” on iron, a molecule that naturally crosses the blood-brain barrier, to deliver both anti-tau and anti-amyloid drugs to the brain in higher concentrations.

    The new wave of tau-focused research comes as the field continues to search for more effective treatments for a disease that is projected to see a sharp rise in cases globally as populations age. While diranersen still requires years of additional testing before it could win regulatory approval, researchers say its early success has already re-energized work on a long-overlooked target that could be key to slowing or stopping Alzheimer’s progression.

    This reporting was supported by the Howard Hughes Medical Institute’s Department of Science Education and the Robert Wood Johnson Foundation, with the Associated Press taking sole responsibility for all content.

  • Majority of new Ebola cases are ‘from unknown chains of transmission,’ WHO official says

    Majority of new Ebola cases are ‘from unknown chains of transmission,’ WHO official says

    GENEVA — The World Health Organization’s top emergencies official issued a stark warning Tuesday, stating that the ongoing Ebola outbreak in the eastern region of the Democratic Republic of the Congo is still moving faster than international and local response teams can contain, following a firsthand assessment trip to one of the crisis’s hardest-hit areas. Chikwe Ihekweazu, WHO’s emergencies chief, returned this week from Bunia, located in Ituri province, the epicenter of the current outbreak, where he uncovered deeply troubling trends driving the virus’s spread.

    According to Ihekweazu, the most worrying observation from his visit is that a large share of newly reported fatalities are people who never accessed formal medical care, passing away in their home communities before they could reach a treatment facility. As of this week, he added, roughly 80 percent of all new confirmed cases are not linked to existing contact tracing lists, meaning they originate from unknown transmission chains that response teams have not been able to track or pre-empt.

    The DRC has been fighting this outbreak of the rare Bundibugyo Ebola variant since undetected community transmission began in early May, with no approved vaccine or specific antiviral treatment currently available for this strain. The Africa Centres for Disease Control and Prevention labeled the event the fastest-expanding Ebola outbreak the African continent has ever seen last week.

    Congolese health authorities released updated figures Monday showing at least 1,926 confirmed and probable infections across three affected provinces, with a total of 702 recorded deaths. The outbreak has already spilled across national borders, with confirmed cases detected in neighboring Uganda, raising concerns of a wider regional spread. Last week, the U.S. Centers for Disease Control and Prevention announced that a U.S. citizen working for a humanitarian organization in the DRC had tested positive for the virus, though no additional details about the patient’s condition or location were released.

    Ihekweazu noted that his trip to Bunia revealed mixed progress: while response capacity has expanded significantly in recent weeks, systemic barriers continue to prevent teams from getting ahead of the virus. Local treatment capacity now stands at nearly 800 beds, with new spaces added every week, and laboratory testing capacity has jumped dramatically from just one operational lab at the start of the outbreak to 14 fully functional facilities. Other core response operations have also seen incremental improvements.

    Still, Ihekweazu emphasized that even with these gains, response teams have not managed to overtake the virus’s spread. “Despite our best efforts … we have not caught up in the race,” he told reporters in Geneva.

    The response effort has been held back by a range of interconnected challenges, including a critical shortfall in funding, repeated violent attacks on health facilities operating in the region, ongoing armed conflict that makes large parts of eastern DRC inaccessible to response teams, and widespread mistrust of medical authorities among local communities. These barriers compounded this week, when dozens of staff members at an Ebola treatment center in northeastern DRC launched a strike Monday over months of unpaid salaries and performance bonuses, further disrupting care delivery.

    The Congolese government only officially declared the outbreak on May 15, after the virus had been spreading undetected through local communities for multiple weeks, the WHO confirmed. Last week, researchers finally launched long-awaited clinical trials for experimental treatments, marking the first formal effort to test targeted interventions against the current circulating strain.

  • Hours each day in an iron lung kept her breathing, her will to live kept her alive

    Hours each day in an iron lung kept her breathing, her will to live kept her alive

    Martha Lillard, the United States’ last remaining person who relied on an iron lung to breathe after contracting polio, died at her home in Oklahoma at the age of 78 on June 26. For nearly three-quarters of her life, the large metal breathing device defined her daily routine — but it never defined her spirit, her family says.

    Lillard was just 5 years old when she was diagnosed with paralytic polio in the mid-1950s, one year before the first widespread polio vaccine rolled out across the U.S. Waking up one morning unable to lift her head from her pillow, she already understood what her symptoms meant: widespread public fear of the incurable disease dominated conversations at the time, and the young girl immediately recognized the signs of the infection that had already left so many children dead or disabled.

    After her diagnosis, Lillard spent decades dependent on the iron lung, a negative-pressure respiratory device that works by adjusting air pressure inside a sealed metal cylinder to force the lungs to expand and contract, doing the work of weakened respiratory muscles automatically. While many children who relied on the machine feared it, Lillard never shared that anxiety, according to her younger sister Cindy McVey. Instead, the device felt like a recharge, leaving her feeling refreshed after daily sessions inside it.

    Against all odds, Lillard and her family refused to let her condition limit the life she built. Determined to let her live as independently as possible, her uncle and grandfather engineered a custom modification to the iron lung that let Lillard open and close the device on her own, granting her the ability to live alone that most other iron lung users never had. Loved ones also retrofitted a car to match her limited mobility: the steering wheel was repositioned to rest in her lap, and turn signals were moved to the floor, letting Lillard drive herself wherever she wanted to go.

    Over her decades of life, Lillard cultivated a rich set of passions. She became a skilled painter, creating detailed landscape works, and was an avid learner who constantly asked questions of her smart speaker to expand her knowledge. She also shared more than 20 years with her partner Baha Salh, who moved to the U.S. from Egypt after securing a visa earlier this year. The pair married in February, just four months before Lillard’s death.

    While her official cause of death is listed as post-polio syndrome and chronic pulmonary failure, McVey says long COVID-19 ultimately contributed to her sister’s passing. Even so, McVey says her sister remained resilient and resourceful throughout her entire life: “She was resilient, she would find a way, or make do.”

    Lillard’s story comes amid a renewed reckoning over polio and vaccine access in the U.S. After the polio vaccine was introduced in 1955, a nationwide mass vaccination campaign eliminated endemic polio in the U.S. by 1979, a major public health victory that ended the regular outbreaks that killed and paralyzed thousands of children annually. According to the World Health Organization, roughly 1 in 200 polio infections result in permanent paralysis, and 5 to 10 percent of paralyzed patients die when their breathing muscles become immobilized.

    Today, however, growing vaccine hesitancy across the U.S. has put that progress at risk. Earlier this year, Kirk Milhoan, chair of the Centers for Disease Control and Prevention’s Advisory Committee on Immunization Practices, drew controversy after suggesting that polio vaccination should be made optional, arguing that improved sanitation and lower current risk mean the tradeoff between vaccine risk and disease risk has shifted.

    That rhetoric and the trend of declining childhood vaccination leave McVey deeply worried. Speaking through tears, she warned that fading cultural memory of polio’s devastation has led generations to underestimate the danger of the disease. “Polio is terrible. The disease disfigures, disables and leaves people trapped. We had it under control here and now we have all these people who aren’t vaccinating their children,” she said. “They may think there’s problems with the vaccine, but there’s a whole lot more problems if they don’t vaccinate.”

    McVey also noted just how narrow the gap was between her sister’s fate and a polio-free life: Lillard was infected the year before the vaccine became widely available, and McVey had friends who participated in the vaccine trials that same year. “It was that close,” she said.

  • Why the fastest-growing Ebola outbreak in history is becoming more challenging

    Why the fastest-growing Ebola outbreak in history is becoming more challenging

    What is already the fastest-expanding Ebola outbreak in recorded history is pushing response teams to their breaking point in eastern Democratic Republic of the Congo, where overlapping security, logistical and social crises have collided just as researchers launch the first clinical trial for life-saving treatments targeting this rare, untreatable strain of the virus.

    The outbreak, driven by the little-studied Bundibugyo Ebola virus, a subtype with no licensed vaccines or proven treatments, has already reached a grim milestone: the DRC Ministry of Health has confirmed nearly 2,000 cases and 702 deaths to date. Worse, suspected cases have now been detected in two additional provinces, including Kisangani, one of the country’s largest urban centers, leaving responders scrambling to map the full scope of the outbreak. Experts now confirm the initial spread went undetected for weeks, as health teams initially tested for more common Ebola subtypes, and the outbreak’s zoonotic origin remains a mystery.

    Unlike better-documented Ebola strains, Bundibugyo is a rare variant that spreads through direct contact with infected bodily fluids—including blood, vomit, and semen—or contact with contaminated materials such as bedding and clothing. Like other Ebola variants, it causes severe, often fatal symptoms ranging from high fever, muscle pain, vomiting and diarrhea to internal and external bleeding. Outbreaks of this strain have historically been limited to remote Central African villages near tropical rainforests, and public health guidance has restricted traditional local funeral practices that involve close contact with deceased loved ones—a measure that has sparked significant anger among local communities.

    Compounding every challenge of this outbreak is the volatile, conflict-ravaged landscape where it is unfolding. Decades of violence by armed rebel groups have left local populations traumatized and deeply distrustful of outside authorities, leading to widespread misinformation that claims the Ebola outbreak is a hoax. Community outreach workers have faced threats and abuse while trying to spread prevention information, and attacks on health facilities have repeatedly disrupted response work. A portion of the outbreak is centered in Goma, a major humanitarian hub and key city that was seized by Rwanda-backed rebel forces more than a year ago, creating further barriers to coordinated relief efforts.

    The latest and most urgent threat to containment efforts came this week, when unpaid frontline workers at the outbreak’s epicenter Ituri province walked off the job. The strike shuttered a core treatment center, with workers blocking access to the facility and burning tires to protest weeks of unfulfilled pay from the Congolese government, after weeks of high-risk work. Striking staff include epidemiologists, contact tracers, drivers, and gravediggers—all critical roles in stopping transmission. Congolese health officials have confirmed they are currently negotiating with workers to resolve the dispute, but public health experts warn that if the strike spreads to other overstretched, underfunded facilities across the region, it could deliver a catastrophic blow to already strained containment efforts. Infrastructure across the affected area is already extremely limited, leaving even fully staffed facilities struggling to operate.

    This unrest has erupted at an exceptionally vulnerable moment for the response. Just weeks before the strike, researchers officially launched the first clinical trial for two promising experimental treatments targeting Bundibugyo Ebola, and have already begun enrolling the first participants.

    The two candidate therapies are remdesivir, a broad-spectrum antiviral developed by Gilead Sciences that is already approved for COVID-19 treatment and has shown preliminary antiviral activity against Bundibugyo in laboratory testing, and MBP134, an experimental monoclonal antibody therapy developed by Mapp Biopharmaceutical that is specifically engineered to target multiple Ebola strains, including Bundibugyo.

    Under the trial protocol overseen by the World Health Organization, patients will be randomly assigned to receive either the current standard of care alone, standard care plus remdesivir, standard care plus MBP134, or standard care plus both investigational treatments. The WHO has cautioned that it could take months of data collection and up to 1,000 trial participants before researchers can confirm whether either treatment is effective. Currently, the trial is only being run at one Ituri province treatment center—an unaffected facility separate from the strike site—and officials plan to expand the trial to additional sites only once security and staffing conditions allow.

  • Dozens at an Ebola treatment center in northeast Congo strike over unpaid salaries and bonuses

    Dozens at an Ebola treatment center in northeast Congo strike over unpaid salaries and bonuses

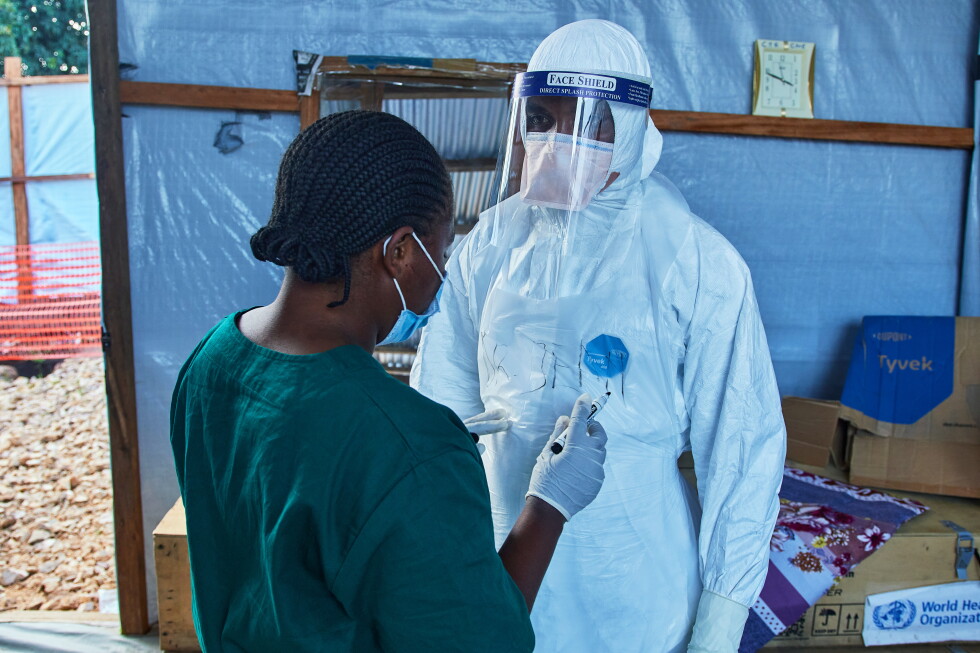
    In the northeastern Democratic Republic of the Congo, a critical Ebola response effort has been thrown into chaos by industrial action, as dozens of frontline workers walked off the job Monday to demand months of unpaid salaries and performance bonuses. The walkout, which has closed the Rwampara General Hospital’s Ebola treatment center in Ituri Province, includes every tier of outbreak response staff: epidemiologists tracking virus spread, contact tracers investigating new cases, ambulance drivers, and gravediggers tasked with safe burials, all of whom confirm Congolese government authorities have failed to disburse their pay.

    Protesting staff not only shut down the treatment facility but also blocked the main access road leading to the site, amplifying their demands. Discontent has been building for days, with a small group of workers launching an initial strike last week, claiming wages have been withheld since the outbreak was officially declared in mid-May.

    Bahati Claude, a frontline health worker assigned to the Rwampara health zone, shared his team’s frustration in an interview with the Associated Press. “We cannot understand how we have gone two full months without pay,” he said, adding that the striking staff remain committed to their public health mission: “We do not want to abandon our posts.”

    The current Ebola outbreak in the DRC, caused by the rare Bundibugyo virus strain, carries uniquely high risks: no licensed vaccine or targeted antiviral treatment exists for this variant. Congolese authorities only declared the outbreak on May 15, after the virus had spread undetected through local communities for several weeks, World Health Organization officials confirmed. As of the latest official update, the outbreak has recorded 1,926 confirmed cases and 702 deaths across the country. Last week, the Africa Centres for Disease Control and Prevention labeled this outbreak the fastest-growing Ebola event ever documented on the African continent.

    During an official visit to Ituri last week, Congolese Health Minister Roger Kamba acknowledged the payment delays, blaming inaccurate payrolls that have included names of people not working on the outbreak response. “We must guarantee that these funds reach the people who are actually doing the work,” Kamba said. “We have encountered several hurdles, particularly constant revisions to staff lists, which have left legitimate workers out of pay cycles and sparking these complaints. We have the resources to resolve this issue.”

    Parallel to the strike, international updates on the outbreak emerged Monday: WHO Director-General Tedros Adhanom Ghebreyesus announced via social media platform X that a second U.S. citizen, a humanitarian worker based in eastern Congo who contracted Ebola, has been evacuated to Germany for specialized care. The first American infected during this outbreak was a physician working in the DRC in the early weeks of virus spread.

  • Powerful pharmacy lobby using secret deals to inflate medicine prices, report claims

    Powerful pharmacy lobby using secret deals to inflate medicine prices, report claims

    A new analysis from one of Australia’s leading independent think tanks has ignited fierce debate over pharmaceutical pricing, claiming that closed-door negotiations between the federal government and a powerful industry lobby have forced taxpayers and patients to overpay billions of dollars annually for prescription medications. The Grattan Institute’s new report pulls back the curtain on decades of opaque policy making, arguing that the Pharmacy Guild of Australia — the national body representing the majority of Australian community pharmacy owners — has leveraged its significant political influence to lock out patient representatives and hide critical cost data from public scrutiny during funding and policy negotiations.

    Lead researcher and Grattan’s Health Program Director Peter Breadon argues that this closed negotiating model is a global outlier. “Unlike almost every other developed nation, Australia’s negotiations for pharmacy funding exclude all stakeholders outside the Guild and the government, and proceed almost entirely without public, evidence-based cost data,” Breadon explained in the report. “This poor governance structure has only delivered bad outcomes for everyone except pharmacy owners themselves.”

    The report’s economic modelling estimates that Australian pharmacies collect nearly $3 billion annually in excessive dispensing fees, driven by a lack of market competition and restrictive industry rules that block widespread discounts for consumers. Under Australia’s Pharmaceutical Benefits Scheme (PBS), which subsidises most prescription medications for the public, the nation’s 6,000 community pharmacies fill 335 million prescriptions each year at a total taxpayer cost of $3.8 billion. Breadon’s analysis found the average dispensing fee — charged to cover the cost of verifying prescriptions, preparing medications, and providing patient counselling — currently sits at $9.24 per script, a figure that cannot be justified because the Guild has repeatedly blocked efforts to measure the actual cost of dispensing services.

    “No one knows the real cost of filling a prescription in an Australian community pharmacy, and that is no accident,” Breadon said. “Fees should be set independently, tied to actual operational costs, not the outcome of closed-door bargaining. Unjustified inflated fees need to be scrapped entirely.”

    The report also takes aim at the existing Community Pharmacy Agreements, which the institute says include overly generous funding terms that shield pharmacy owners from revenue declines while inflating profits at the expense of taxpayers and consumers. Breadon added that while regulatory rules already allow pharmacies to discount medications priced below the PBS maximum co-payment — a policy that has delivered $319 million in annual savings for patients in 2025 — a web of complex industry regulations prevents pharmacies from passing additional savings on to consumers for other prescription drugs. Simplifying these discount rules alone could deliver an extra $48 million in annual savings for Australian patients, the modelling found.

    To fix the systemic flaws, the Grattan Institute is calling for a full overhaul of the negotiating framework: the federal government should open negotiations to independent, evidence-based fee-setting, the same model used for other Australian health care sectors. If wholesale reform is not pursued, Breadon said, patient representatives should at minimum be included at the negotiating table, with all cost data released to the public to justify final funding decisions. “The Australian government spends billions of dollars on community pharmacy services every year,” Breadon said. “Fairer fee structures and stronger competition will ensure the system works for patients, not just pharmacy owners.”

    The Pharmacy Guild of Australia has pushed back forcefully against the report’s claims, with National Vice President Simon Blacker arguing the organisation has a long track record of advancing affordable access to medications for Australians. Blacker highlighted the Guild’s recent collaboration with the federal government to cut the PBS general co-payment to $25 starting in January 2026, a reduction that will bring the co-payment to its lowest level since 2004 — only the second cut to the co-payment in the PBS’s entire history.

    Blacker also reaffirmed the critical public health role that community pharmacies play across Australia, noting that increasingly, specially trained pharmacists are able to diagnose, treat, and prescribe for a wide range of common acute and chronic health conditions — a expanded scope of practice that Blacker says should be supported by a national consistent prescribing framework. Both the Grattan Institute and the Pharmacy Guild have acknowledged the essential role community pharmacies play in guaranteeing access to medicines, health advice, and frontline care for Australian communities, leaving the debate focused on governance and pricing rather than the core value of local pharmacy services.

  • Zoos closing exhibits in bid to protect their animals

    Zoos closing exhibits in bid to protect their animals

    After the deadly H5 strain of avian influenza was confirmed on Australian territory, zoos and wildlife parks across the country have rolled out sweeping emergency biosecurity measures and temporary operational changes to safeguard their captive animal populations, as the outbreak expands into three states.

    The first confirmed case of H5 bird flu in Australia was recorded on June 20, when an infected migratory seabird was discovered on Western Australia’s south coast. In the weeks since, the virus has spread: five cases have now been confirmed in WA, two in South Australia, and one in New South Wales where an infected giant petrel was found at Hawks Nest. Just this week, South Australian health authorities confirmed the virus reached a native Australian bird species, marking a worrying escalation of the outbreak.

    Unlike many other regions that faced sudden, unplanned outbreaks, Australia benefited from months of advance warning as the virus spread globally over recent years, allowing the nation’s major zoos to prepare contingency plans well before the first local case was detected.

    At Adelaide Zoo, one of the country’s most high-profile wildlife attractions and the only Australian zoo that hosts giant pandas, management has taken the difficult step of temporarily closing multiple key attractions. The zoo’s popular walk-through aviaries are currently shut to visitors, the daily interactive little penguin experience has been suspended, and all free-flight bird shows featuring owls, macaws and other avian species have been called off indefinitely.

    Phil Ainsley, chief executive of Zoos SA, which operates both Adelaide Zoo and the Monarto Safari Park, said that planning for the arrival of H5 bird flu has been underway for years. “Our core priority will always be the health and welfare of the animals under our care,” Ainsley explained. “We have comprehensive, tested response plans in place, and we stand ready to roll out additional biosecurity controls if the situation worsens. We are in constant close coordination with national and state government agencies, and all our actions follow the latest guidance from wildlife disease experts.”

    Over at Perth Zoo, management has implemented a suite of layered precautionary measures designed to cut the risk of transmission between wild birds and captive species, particularly for some of the nation’s most at-risk endemic animals. Extra physical barriers, public hand sanitisation stations, and informational signs have been installed across the site — measures that echo the widespread public health protocols adopted during the COVID-19 pandemic. Enclosure modifications now include covering the habitats of critically endangered species such as western ground parrots, numbats and black cockatoos with protective roofing barriers to prevent contact with wild birds.

    Perth Zoo is also currently evaluating a policy that would require staff and visitors to wear personal protective equipment, including disposable foot coverings, when entering certain high-risk animal enclosures. While walk-through aviaries at the zoo remain open for now, management says full closure remains an active option if the outbreak spreads further. David van Ooran, Perth Zoo’s executive director, noted that the facility drew on years of insight from international zoo colleagues to build its response plan. “The biggest benefit we had was advance awareness of this threat, which let us learn from facilities overseas that have already navigated outbreaks and tailor our own response accordingly,” van Ooran said. “We believe our preparations put us in a strong position to manage this, and we are monitoring the changing situation closely every day.”

    Van Ooran emphasized that the main transmission risk comes from wild birds that are drawn to the zoo’s lush botanical landscapes and water features, noting that the threat is shared across the entire community. “Like most zoos, we have beautiful green spaces and water features that naturally attract wild birds, that’s unavoidable,” he explained. “That said, we have a very detailed biosecurity plan in place, and we are looking at adding specialized sanitation mats at the entrances to our walk-through aviaries. While we have not had to close these exhibits yet, we are prepared to take that step if needed.”

    Despite the new restrictions, van Ooran stressed that the zoo remains fully open to visitors, especially during the current busy school holiday period, and encouraged the public to visit as normal. “Our message to the community is clear: we are very much open for business, and the overall visitor experience will not change in any meaningful way,” he said. “We still encourage people to plan a trip and enjoy the zoo as they normally would.”

    Taronga Zoo, which operates two major wildlife veterinary hospitals in Sydney, has implemented strict new protocols for people seeking care for sick wild birds: the facility now requires the public to call ahead before bringing any birds to the hospital, to reduce the risk of introducing the virus onto zoo grounds. Nationwide, zoos are urging members of the public not to attempt to transport sick or dead wild birds to zoos for veterinary care, to avoid accidental virus transmission.

    Australia’s national health authorities have issued clear public guidance: any person who encounters a sick or dead wild bird is advised not to touch the animal, and to immediately report the sighting to the national Emergency Animal Disease Hotline at 1800 675 888.

  • US citizen tests positive for Ebola in Congo

    US citizen tests positive for Ebola in Congo

    KINSHASA, Democratic Republic of Congo – As Central Africa’s largest nation grapples with an expanding and increasingly dangerous Ebola outbreak, the U.S. Centers for Disease Control and Prevention confirmed Friday that an American citizen employed by an international humanitarian organization operating in the country has contracted the virus.

    The CDC announced in a public statement that it has launched a coordinated response alongside the infected worker’s employer, multiple U.S. federal agencies, Congolese national public health officials, and local in-country partners. The primary priorities of the collaboration are to stop secondary spread of the virus and trace every close contact the patient has had since testing positive. No additional personal or clinical details about the case have been released to protect privacy.

    The current outbreak has already carved a grim path across the continent, the Africa Centres for Disease Control and Prevention confirmed earlier this week. It is now the fastest-growing Ebola outbreak ever recorded in Africa, with 1,830 confirmed cases reported within Congo’s borders and 648 recorded deaths. The virus has also spilled across national borders, with confirmed cases detected in neighboring Uganda, raising alarms about a wider regional spread.

    This is not the first time an American has been infected during the current outbreak. In the opening week of the crisis, a U.S. doctor working in the country tested positive for Ebola and was evacuated to Germany for specialized medical care.

    Earlier in the response, the Trump administration had announced a policy to evacuate any U.S. citizens exposed to Ebola while working in the region to a new isolation and treatment facility in Kenya, rather than transporting them back to the United States. That plan has since been put on hold, however, after a Kenyan court issued an order suspending the project.

    According to the World Health Organization, Congolese authorities only formally declared the current outbreak on May 15, marking a weeks-long delay in official detection after the virus began spreading silently through communities.

    Adding to the complexity of the crisis, this outbreak is caused by the rare Bundibugyo Ebola virus, a strain for which no officially approved vaccine or targeted treatment currently exists. Containment efforts have been further undermined by a series of overlapping challenges: a critical gap in international funding for the response, repeated violent attacks on health facilities operating in the outbreak zone, and a long-running armed conflict in eastern Congo, where the outbreak is centered.

    Just last week, the first round of clinical therapeutic trials got underway, after researchers launched a long-awaited research study designed to test potential life-saving treatments for the strain.