分类: health

  • Inside India’s forest villages, where a dangerous mix of crises led to 32 child deaths

    Inside India’s forest villages, where a dangerous mix of crises led to 32 child deaths

    It is an unspeakable tragedy that has unfolded across the remote, forested tribal villages of Balaghat district in India’s Madhya Pradesh state. Since May, at least 32 children have lost their lives to a deadly combination of infectious disease, systemic neglect, and geographic isolation, leaving grieving families to grapple with preventable loss and shattered futures. The tragedy first came to light through the story of three-year-old Bamita Markam, whose short life ended at dawn one rainy May morning after days of agonizing illness.

    Bamita first developed a high fever and painful red sores across her body. Her mother Koushila initially brought her to a local doctor, who prescribed an ointment, and the toddler appeared to briefly recover before falling dangerously ill again. Desperate and trapped by impassable, muddy terrain, the family turned to a local faith healer, who administered homemade syrups and tablets that did nothing to slow the disease. By the time the sun rose, Bamita was dead after convulsing through the night and vomiting blood. Her small body was buried in the nearby jungle by midday. “If god took away our children, what can we do?” Koushila says, her grief unspoken but palpable.

    Almost all of the victims, who range in age from three-month-old infants to an 18-year-old young adult, belong to the Baiga people, one of India’s 75 classified Particularly Vulnerable Tribal Groups, communities that have long faced systemic exclusion and limited access to basic services. Local officials have attributed the majority of deaths to a combination of measles and malaria, with public health experts noting that pre-existing malnutrition and dangerous delays in accessing medical care drastically worsened outcomes.

    Current official data points to roughly 8 to 10 deaths linked to measles, another 10 tied to malaria, with many children suffering from multiple overlapping infections. The full scope of causes for each individual death remains unclear, but even seasoned local leaders say they have never seen a crisis of this scale. “I have never seen an outbreak like this. My father was a two-term lawmaker, and I have served three terms, but neither of us has seen so many children die in such a short time,” says Sanjay Uikey, who has represented the area as an elected official since 2013.

    Beyond the spread of infectious disease, the crisis exposes deep, long-running structural flaws in healthcare access for India’s most remote tribal communities. In these heavily forested parts of Balaghat, regions once troubled by Maoist insurgency, just reaching a functional health care facility is an often insurmountable challenge. The monsoon season turns narrow dirt tracks connecting scattered mud homes into slippery, impassable paths, cutting off entire hamlets from the outside world. The nearest 100-bed state hospital in Birsa sits roughly 70 kilometers from many of the affected villages. For families without private transportation, reaching the facility requires trekking for miles across mud, carrying sick children on makeshift bamboo stretchers or the back of motorcycles, and losing an entire day of wages that many already impoverished families cannot afford to forfeit.

    Poverty and geographic isolation are compounded by deeply held cultural beliefs that shape how many Baiga families respond to illness. For generations, many community members have viewed common illnesses like rashes and fevers as the arrival of Mata, the disease goddess, who must be appeased through traditional rituals rather than rushed to formal medical treatment. Families often perform seven to nine-day rituals involving bathing, offerings of cool water and neem leaves to the goddess, with a widespread belief that seeking modern medical care before the ritual is complete will bring death. For weeks after the first cases emerged, these beliefs led many families to delay seeking care, allowing otherwise treatable infections to become fatal.

    The scale of the crisis only began to emerge in late July, when local village council chief Parshuram Dhurwey learned of three child deaths in one small neighborhood of Bondari village within 24 hours. When he and local officials reached the area, they found a devastating scene: nearly every other child was sick, struggling with fever, rashes, and severe dehydration, most suffering from chronic undernutrition. When government medical officer Nimish Gautam first arrived to assess the outbreak, he encountered a teenage girl with several days of fever and a dangerous low blood sugar level, whose family refused to let medical teams examine her properly, convinced that transporting her to a hospital would kill her. “Police were brought in to persuade them to take her to a health centre. The family still refused. So we kept her under observation, and she recovered,” Gautam recalls. In one village, officials ultimately forcibly removed five seriously ill children to receive hospital care; every single one survived.

    By the time local authorities recognized the scope of the outbreak, children had already been dying for weeks. Across four villages in Dhurwey’s council alone, 10 children between 18 months and 14 years old lost their lives. The tragedy has repeated across hamlets: Sagnibai of Bondari lost two children within 24 hours, her 12-year-old daughter Lamnin and one-year-old son Sahil, after local healers attributed their illness to Mata and the family had no money or transport to reach a hospital. Mahasingh Parte of Matla village lost two children, a six-year-old girl and four-year-old boy, within two days of each other after a faith healer ordered the family not to seek hospital care. Parte, a landless farm laborer who earns just 200 rupees ($2) on a good day, with work even scarcer during the monsoon, lives just 5 kilometers from a small primary health center but had never visited it. Poverty and remoteness stacked all odds against his children.

    Investigations by the ICMR-National Institute for Tribal Health Research confirmed that six out of 10 tissue samples collected from affected villages in early August tested positive for measles, a highly contagious viral infection that is easily preventable with vaccination but can turn deadly for chronically undernourished children. Measles weakens the immune system, leaving young children vulnerable to life-threatening complications including pneumonia, severe dehydration, and brain swelling, and the risks rise drastically when paired with malaria, which is endemic to Balaghat district. Many sick children were also suffering from secondary infections including scabies, bacterial skin infections, and fungal disease, compounding their weakened health.

    Public health experts emphasize that no single factor is to blame for the mass deaths, but rather a deadly collision of multiple vulnerabilities. Chronic malnutrition is endemic across the Baiga community, with the tragic case of one five-year-old who died of measles weighing just 5 kilograms, less than the average weight of a one-year-old child. Gautam attributes widespread child malnutrition to a combination of early marriage and early motherhood, with many Baiga girls giving birth by age 16 or 17 when their own bodies are still developing, leading to closely spaced pregnancies, premature births, and low birth weights. Many young mothers lack the resources and support to properly breastfeed and nourish their children, and most families rely on a monotonous diet of rice and lentil soup with very little protein or dietary variety, leading to widespread nutritional deficiencies. Low uptake of public health and nutrition services further exacerbates these gaps.

    While the Baiga community is not entirely cut off from modern India — many families have solar electricity, bank accounts, and access to smartphones where children watch social media reels, and many adults migrate seasonally for work — the gap between government services on paper and delivery on the ground could not be starker. A 2024 audit by India’s Comptroller and Auditor General found “serious irregularities” in Madhya Pradesh’s distribution of government-issued take-home rations designed to supplement the diets of young children, pregnant women, and lactating mothers, with widespread failures in beneficiary identification, production, transport, and distribution that left the most vulnerable without critical support.

    Once the outbreak was finally recognized, state health authorities launched an emergency response, with health workers conducting door-to-door screening across affected villages and mobile medical units equipped with oxygen, diagnostic tests, and medications visiting more than 20 remote hamlets. At the peak of the response, medical teams treated more than 50 patients a day, half of them children, conducting more than 10 malaria tests daily. In total, more than 6,200 mostly child patients were treated at home, more than 630 were referred to district hospitals, and roughly 30 remain hospitalized as of late September.

    Emergency vaccination efforts also revealed gaps in official vaccination coverage: while official records claimed 90 to 95% coverage for measles, health teams found hundreds of unrecorded children and many families reluctant to accept vaccination. Authorities responded by offering the measles-rubella vaccine to all children under 15 regardless of prior vaccination status, and had vaccinated roughly 27,000 of 40,000 identified children in the Birsa block as of September.

    The outbreak has now subsided, with officials reporting no new child deaths for more than two weeks before their late September assessment, and medical camp caseloads have dropped dramatically from 120 children a day at the peak to fewer than 10. But for the grieving families who lost their children, the pain of the tragedy is permanent. Back in Matla village, Koushila Markam visits the rocky grave of her daughter Bamita, who loved to play with her older sister Ankita and was frightened of passing cars. “I had hope she’d study and make something of herself. I never regretted I didn’t have a boy,” Koushila says, looking at her surviving six-year-old daughter, who still cries constantly for her sister. “I want more kids. I feel alone. Ankita is alone. She keeps crying for her sister.”

  • What is kratom, the ‘gas station heroin’ alarming officials in the US?

    What is kratom, the ‘gas station heroin’ alarming officials in the US?

    For millions of Americans living with unmanaged chronic pain, the herbal product kratom has emerged as a controversial, unregulated lifeline — but a recent incident involving two deceased college students has reignited long-simmering debates over its safety and legal status across the country.

    Jeffrey Deaver, a 58-year-old retired timber cutter from Washington state, is one of many kratom users who swear by the plant’s pain-relieving effects. After years of severe, unrelenting hip and knee pain that failed to respond to conventional medical treatments, and while he waited for scheduled joint replacement surgeries, Deaver turned to kratom on a recommendation. Wary of its unknown effects at first, he began with small doses, gradually increasing his intake until his pain subsided. Describing the outcome as nothing short of a miracle, Deaver said the herb allowed him to sleep through the night and return to daily function, adding that he cannot imagine managing his condition without access to it.

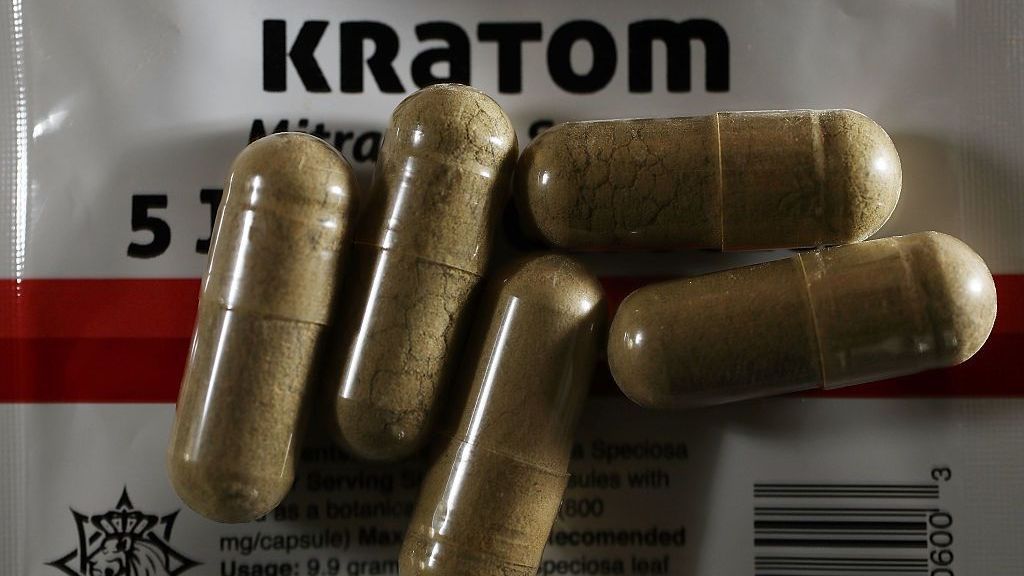
    Kratom, a tropical tree native to the rainforests of Southeast Asia including Thailand, Malaysia, and Indonesia, has a centuries-long history of traditional use as a natural stimulant, typically brewed as a tea for workers to combat fatigue. It was first introduced to the U.S. consumer market as a dietary supplement around 2016, and its popularity has skyrocketed over the past decade, with users purchasing over-the-counter kratom in pill, powder, or concentrated liquid form from convenience stores, gas stations, vape shops, and online retailers.

    This week, new public warnings have been issued after investigators found packaged kratom in the possession of two deceased University of Mississippi students. While authorities have not linked the herb directly to the students’ deaths, the discovery has drawn renewed attention to the risks of unregulated kratom consumption. Unlike pharmaceutical drugs, kratom is not overseen by the U.S. Food and Drug Administration (FDA), and its legal status varies widely across the country, with 11 states having enacted full bans, including Massachusetts, which issued a temporary emergency ban just last month.

    Medical experts warn that the unregulated nature of the U.S. kratom market poses the greatest threat to public health. Dr. Shane Speights, dean of the New York Institute of Technology College of Osteopathic Medicine at Arkansas State University, explained that unlike the low-concentration loose-leaf kratom used traditionally in Southeast Asia, most products sold in the U.S. are highly concentrated formulations. Because they are classified as dietary supplements rather than controlled substances, there is no federal oversight of ingredients, dosing, or manufacturing standards. “There’s no way to know exactly what you’re getting,” Speights said. “An unregulated producer could mix any compound into a product, market it as kratom, and no authority would check its contents before it reaches consumers.”

    Kratom’s active chemical compounds, such as 7-Hydroxymitragynine, interact with the brain’s dopamine system to produce effects similar to narcotic opioids. At low doses, it acts as a stimulant, producing a caffeine-like energy boost, which has led some users to turn to it to wean off of harder opioids like fentanyl. At higher doses, it produces intense euphoria and a sense of being high, and can also trigger hallucinations. The most serious risk, Speights noted, is central nervous system depression at high doses, which can lead to cardiovascular collapse and respiratory failure — the primary cause of kratom-related deaths.

    Addiction treatment specialists add that dependence and withdrawal are common side effects of regular kratom use. Jana Wu, director of clinical integration at Mountainside addiction treatment center, explained that users quickly develop a tolerance to kratom, requiring increasingly larger doses to achieve the same effect, leading some to consume up to 20 pills per day. “Kratom addiction destroys personal relationships and careers,” Wu said. “I’ve seen patients lose their jobs and spend thousands of dollars a month to support their habit.”

    Efforts to enact a federal ban have stalled for years. In 2016, the U.S. Drug Enforcement Agency (DEA) moved to classify kratom as a Schedule 1 controlled substance, the same category as heroin and LSD, citing “an imminent hazard to public safety.” But the agency abandoned the plan months later after the Department of Justice received tens of thousands of public comments opposing the ban from chronic pain patients and advocacy groups.

    Since the failed federal ban, regulatory action has been left to individual states. Recent efforts include a lawsuit filed by Arizona against a company selling kratom-infused beverages, and anti-kratom advocacy groups are pushing for more state-level bans, calling unregulated kratom a “gas-station drug that is poisoning American communities.” On the other side of the debate, pro-kratom groups such as the American Kratom Association support bans only on synthetic products mislabeled as natural kratom, rather than a full ban on the herb itself.

    Internationally, regulatory frameworks also vary: kratom is fully illegal in the United Kingdom, legal status differs across European Union member states, and even in its native Malaysia, sale and consumption have been banned under the country’s 1952 Poisons Act. For users like Deaver, however, the debate over regulation leaves their access to pain management in limbo, highlighting the deep divide over how to balance individual access to alternative pain treatment with public health safety.

  • In Amish country, nurses go door to door to stop deadly spread of measles

    In Amish country, nurses go door to door to stop deadly spread of measles

    Nearly five months after the United States’ deadliest measles outbreak in three decades began in rural Pennsylvania, public health workers are waging a targeted, on-the-ground campaign to curb transmission in one of the state’s most isolated populations: the Amish community.

    Home to roughly 90,000 Amish residents – the largest concentration of the devout Christian group in the country, who first settled in Pennsylvania’s Lancaster County in the early 1700s – the region has become the epicenter of a public health crisis that has already claimed four lives. Unlike most modern communities, the Amish broadly reject many trappings of 21st-century life, from widespread technology use to regular engagement with conventional Western medical systems, creating unique barriers to routine immunization.

    Local health officials estimate that only around one in four Amish residents in the Lancaster area have received the measles, mumps and rubella (MMR) vaccine, a gap that public health experts stress is not rooted in religious opposition. “A lot of people who haven’t gotten vaccinated, it’s not because they have a strong stance against getting vaccinated for measles. It’s just that they haven’t gotten around to it. It’s not convenient,” explained Braxton Mitchell, a genetic epidemiologist at the University of Maryland School of Medicine who has long studied Amish communities in the region. Without easy access to transportation or regular primary care, routine immunization often falls by the wayside, and the community’s tight-knit, highly social structure means the highly contagious measles virus spreads rapidly once introduced.

    To reach this under-served population, Chester County – which borders outbreak epicenter Lancaster – has adapted its response, drawing on door-to-door outreach strategies honed during the COVID-19 pandemic. Dale Weiser, a clinical supervisor and nurse with the Chester County Health Department, has spent months making daily house calls across the rural countryside, sometimes driving 30 miles or more each day to administer vaccines in private home settings, often at residents’ kitchen tables.

    Many Amish adults lack health insurance and have limited ongoing interaction with the formal healthcare system, Weiser explained, so building trust is the first critical step to increasing uptake. “When you start talking and you answer their questions, and build that trust, a lot of times they will make a different decision,” she said. To date, Weiser has personally vaccinated roughly 100 people, and the county has administered 538 total MMR vaccines, more than 60% of them in private, in-home settings to accommodate residents who cannot travel to clinics or prefer to keep their vaccination decision private.

    This boots-on-the-ground approach has also helped public health workers address persistent vaccine misinformation that has seeped even into this insulated, technology-limited community. Weiser says she regularly encounters common falsehoods spread by national anti-vaccine groups, from claims that vaccines contain heavy metals that cause magnetism to assertions that shots include microchips. While staunch anti-vaccine advocates remain largely unpersuaded, local officials note that many undecided Amish residents – especially new parents – have begun asking questions and seeking immunization after seeing neighbors and loved ones fall seriously ill.

    Statewide, the response has delivered measurable progress: since the outbreak began in late April, public health departments have administered nearly 4,300 MMR vaccines at pop-up clinics near the outbreak’s core. Even so, the outbreak has already become the deadliest the U.S. has experienced since 1992, with four confirmed deaths: two infants, one 18-year-old, and a 40-year-old woman. Experts warn that measles, which was declared eliminated in the U.S. in 2000, has established sustained community transmission, and the upcoming school year risks accelerating spread even further. Weiser predicts the outbreak will continue for another six to 12 months.

    Beyond public health challenges, the crisis has ignited sharp political tensions between state and federal health leaders, centered on vaccine policy and misinformation. Federal Health Secretary Robert F. Kennedy Jr., a longstanding vaccine skeptic, drew widespread condemnation after publicly disputing that one of the infant deaths was caused by measles complications. Democratic Pennsylvania Governor Josh Shapiro has publicly accused Kennedy of spreading harmful misinformation that worsens the outbreak. The county coroner, a Republican, initially stated one infant died from a ruptured spleen, but leading infectious disease experts note that measles causes spleen enlargement, directly increasing the risk of rupture, and contributed substantially to the child’s death.

    Public health experts also point to recent actions by the Trump administration that have amplified public doubt about MMR vaccine safety. Most recently, former President Trump issued an executive order calling for the combined MMR vaccine to be split into three separate doses – a change doctors universally agree is unnecessary, more costly, and does nothing to improve the shot’s proven safety record. “What he’s doing is casting doubt,” said Dr. William Moss, a pediatric infectious disease specialist at the Johns Hopkins Bloomberg School of Public Health. “He basically said the vaccine could be dangerous in its current combined form.” For frontline workers working to build trust and curb transmission, these political divisions only add another layer of complexity to an already difficult fight against a fast-spreading, preventable disease.

  • ‘Make women feel seen’: Why the Dutch have a new word for labia

    ‘Make women feel seen’: Why the Dutch have a new word for labia

    For decades, women across Europe have spoken of the quiet discomfort of encountering stigma woven into the very language used to describe their bodies — from outdated, shame-linked anatomical terms to judgmental phrasing in medical documentation. Now, a landmark decision from one of the Netherlands’ most authoritative dictionaries has put this long-running advocacy effort in the global spotlight, opening a new chapter in the fight for gender-inclusive, respectful terminology.

    Last month, Dikke van Dale, the Netherlands’ leading reference dictionary, announced it will add “vulvalippen” — a neutral, anatomically accurate term for labia that translates directly to “vulval lips” — to its upcoming online update. The new entry will appear alongside the long-standing traditional term “schaamlippen”, which literally translates to “shame lips”.

    Activists across the continent have spent years pushing to revise terminology tied to women’s bodies, sexuality and health, united by the core goal of moving away from words that carry implicit misogyny and judgment. Shari Klein, co-founder of the Dutch advocacy group Schaamteloos — which campaigns against terms incorporating the root “schaam”, meaning shame — spoke at a recent public march celebrating the dictionary’s decision, emphasizing the profound impact language has on self-perception.

    “Language shapes how we see ourselves,” Klein explained. “It’s crucial people have a more neutral, anatomically correct word – not a word that links to shame, whether consciously or subconsciously.”

    While calls to adopt “vulvalippen” are not new, campaigners say the dictionary’s decision marks a key cultural milestone, signaling that mainstream society may finally be ready to confront outdated linguistic norms. Esther Van der Valk, a member of prominent Dutch feminist organization Dolle Mina, noted that the shift is also tied to broader efforts to advance sex positivity and eliminate body shaming. Following the dictionary’s announcement, the movement’s next priority is to persuade medical providers and government officials to adopt the new term in patient consultations, public health leaflets and official documentation.

    Ton den Boon, editor of Dikke van Dale, defended the decision to add the new term, noting that “vulvalippen” has already gained widespread traction across Dutch public life: it appears regularly in media, biology textbooks, medical resources, and even veterinary medicine, making its formal inclusion long overdue.

    Still, the question of whether the term will achieve full mainstream adoption across all sectors remains open. The campaign also opens the door to broader re-evaluation of other Dutch anatomical terms that carry similar stigma, including “schaam haar” (shame hair, the traditional term for pubic hair), “schaam been” (shame bone, referring to the pubic bone) and “schaam lice” (shame lice, the common term for pubic lice).

    This Dutch push for linguistic reform is not an isolated effort. It mirrors parallel campaigns across Europe that have sought to rework harmful terminology for decades. In 2018, German journalists Gunda Windmüller and Mithu Sanyal launched a petition to swap the German equivalent of “shame lips” for “Vulvalippen”, after Windmüller learned from gynecologists that many women experience deep shame when discussing their bodies during medical appointments. When researching her reporting, Windmüller found she could not even reference basic female anatomy without including the word “shame”. While “Vulvalippen” has not yet been added to major German dictionaries, the term has already entered common use in textbooks, women’s magazines and everyday conversation, and Windmüller says she hopes the Dutch decision will reignite momentum for reform in Germany.

    Similar efforts have already yielded results in other parts of Europe. In Sweden, a successful 2009 campaign led to the addition of a new term for hymen to the country’s academic dictionary. The traditional term, “mödomshinna”, translates to “maidenhood membrane” or “virginity skin”, a phrasing that activists from the Swedish Association for Sexuality Education (RFSU) argued was both anatomically inaccurate and reinforced harmful myths about virginity and female sexuality. The new term, “slidkrans”, translates to “vaginal corona”, a name that accurately reflects the biological reality of the hymen: a natural ring of tissue folds, not an intact seal that breaks during first intercourse. “With a new word we can challenge the myths that seek to control women’s sexuality and freedom,” explained RFSU’s Sonja Ghaderi. While the term is now widely used by healthcare providers in youth clinics, Ghaderi noted that harmful misinformation persists, underscoring the ongoing need to challenge limiting social constructs embedded in language.

    Across the Channel, the movement has also gained traction in the UK, where feminist podcast host Nicola Denson-Elliott has launched a petition to replace the term “hysterectomy” — the medical name for surgical removal of the womb — with “uterectomy”. Denson-Elliott points out that “hysterectomy” has deep linguistic roots in the word “hysteria”, a historical term once used to label women’s emotional distress as a unique gendered disease. Advocates argue the new name would be more anatomically accurate and free of outdated, misogynistic baggage, framing the existing term as a form of medical misogyny. “Women deserve terminology that respects them,” the petition states.

    Not all experts oppose reform, but some caution that any changes to medical and anatomical language require careful consideration to avoid confusion. Dr. Beth Malory, a linguistics researcher who studies gendered language in healthcare, notes that new terms must be tested for clarity before widespread adoption. “Will people understand uterectomy? Is simply saying removal of the womb better?” she asked, adding that new terminology must not be ambiguous, and changes need to be considered within the broader context of existing medical language to prevent confusion.

    Malory’s own research on language used in pregnancy and obstetrics has highlighted just how much harm outdated, judgmental phrasing can cause. One common term she highlights is “incompetent cervix”, used to describe a cervix that shortens prematurely, increasing the risk of pregnancy loss and preterm birth. Malory says many women have told her the term makes them feel personally blamed for a medical condition they cannot control.

    “Why do we need judgmental words like failure or incompetency?” asked Dr. Brooke Vandermolen, an obstetrician who has stopped using several problematic terms in her own practice, including “failure to progress”, the traditional phrase used to describe labor that does not advance as expected. “Language is incredibly important and the words we choose can show recognition and make people feel validated and seen.”

    In 2022, the UK’s Royal College of Midwives released official guidance offering alternative, less stigmatizing phrasing for common obstetric terms. Even so, Vandermolen says many traditional terms remain in widespread use and continue to cause unnecessary emotional distress for patients. She says she hopes the Dutch decision to add “vulvalippen” to its national dictionary will spark broader conversations across the UK and beyond about how language shapes experiences of women’s health. “What we say can have a lasting impact,” she noted.

  • India’s hospital boom is improving access but pricing millions out of critical care

    India’s hospital boom is improving access but pricing millions out of critical care

    A walk down a 5-kilometer road in Miraj, a mid-sized regional town in India’s western state of Maharashtra, offers a clear snapshot of a seismic shift reshaping India’s healthcare landscape: more than 50 new multi-specialty hospitals, diagnostic hubs and private clinics line the route, almost all built in just the last five years. This proliferation of private care facilities is far from an isolated trend. It is the visible marker of an unprecedented boom that has swept India’s private healthcare industry over the past decade, transforming access to care while sparking urgent debate over systemic inequality and affordability.

    Across the country, private hospital groups are expanding at breakneck speed, adding thousands of new beds every quarter to meet rising demand. Diagnostic chains are rapidly extending their reach into tier-2 and tier-3 towns that were long underserved by formal healthcare, while leading medical institutions are tapping public markets to raise hundreds of millions of dollars for nationwide expansion. In early August 2026, Manipal Health, India’s largest multi-specialty hospital chain, pulled in nearly $1 billion through an initial public offering (IPO), marking the country’s second-biggest public market debut of the year.

    Global private equity investors have also flocked to the sector, lured by India’s growing demand for healthcare as incomes rise and chronic disease rates increase. Data from consulting firm Grant Thornton shows that between 2022 and 2024, Indian healthcare and pharmaceutical companies closed nearly 600 merger and acquisition (M&A) and private equity deals worth a combined $30 billion. Forty percent of that total investment went directly to hospital operators, and the BBC’s analysis of additional Grant Thornton data reveals the sector has raised a further $20 billion in just the past two years.

    While this wave of investment has dramatically expanded the overall availability of healthcare infrastructure across India, it has also pushed life-saving care out of reach for millions of low- and middle-income citizens, deepening a national affordability crisis that has sparked alarm among policymakers and public health experts. A new government advisory panel report has laid bare the stark inequality at the heart of India’s fast-growing private healthcare economy, warning that unregulated growth is leaving vulnerable households at severe financial risk.

    The panel’s analysis found that the cost of treatment at private hospitals is typically 5 to 10 times higher than at comparable public sector facilities. The gap grows even wider for patients battling high-cost chronic and critical illnesses including cancer, heart disease and kidney failure. The report also points out that unbridled expansion of small clinics, nursing homes and diagnostic centers, paired with inconsistent enforcement of national regulatory standards, has created huge disparities in both care quality and pricing across the private sector. This lack of oversight leaves patients exposed to arbitrary pricing and widespread substandard care practices.

    Rampant commercialization of private healthcare, the report adds, has driven a surge in patient complaints over excessive billing, unnecessary diagnostic testing, and exorbitant costs for routine procedures such as childbirth. These inflated costs are directly pushing vulnerable households into catastrophic, life-altering debt, forcing many to sell assets or deplete decades of savings to cover medical bills. The crisis of unregulated pricing was highlighted earlier this month when Maharashtra’s food and drug regulator discovered that private hospitals in the state were selling intravenous (IV) fluid sets with a staggering profit margin of 2,800%, a mark-up that regulators noted is almost entirely unmonitored under current rules.

    To address these systemic gaps, the government panel has put forward a sweeping set of policy recommendations, including several highly contentious proposals. Among the most debated ideas are a cap on private hospital room rates capped at the average rate of a local three-star hotel, mandatory price regulation for essential treatments, diagnostic services and routine procedures across all private facilities, and enforced standard treatment guidelines to cut down on unnecessary over-treatment. The panel also issued a red flag over foreign ownership exceeding 51% of large domestic hospital chains.

    India’s private healthcare industry has pushed back aggressively against many of these proposals, arguing that price caps will stifle future investment and slow the expansion of much-needed care capacity. In an official statement to the BBC, Siddhartha Bhattacharya, Secretary General of NATHEALTH, the leading industry association for India’s private healthcare sector, said policymakers should focus on cutting structural costs that drive up care prices including high taxes, expensive land, costly capital, strict regulatory compliance fees and high skilled labor costs, rather than imposing arbitrary rate caps.
    Bhattacharya noted that healthcare delivery is an extremely capital-intensive and investment-heavy sector, with return on capital employed hovering around just 10% — far lower than the 15-25% returns common in many other sectors of the Indian economy. He also rejected the comparison of hospital room pricing to three-star hotel rates, arguing that the analogy overlooks the costly mandatory compliance standards that hospitals must meet, including rigorous infection control protocols and patient safety requirements that add significantly to operating costs.

    Leaders of India’s largest hospital chains, including Max Healthcare and Fortis, have echoed these concerns, warning that arbitrary price caps will drive away domestic and foreign investors alike, who will exit the market if they cannot guarantee fair returns on the large upfront capital investments required to build and operate hospitals.

    Despite industry pushback, public health experts argue that price regulation is a necessary intervention, noting that India’s private healthcare market currently operates entirely as an unregulated seller’s market that gives providers near-total control over pricing. “With large amounts of foreign private equity flowing into the sector, especially for advanced tertiary care, pricing decisions are increasingly being made by stakeholders outside of India, and that is not a sustainable model,” Dr. Srinath Reddy, president of the Public Health Foundation of India, told the BBC.

    Vivek ND, a leading New Delhi-based health policy expert, added that government intervention is particularly critical given the super-sized profits many large hospital chains are currently earning from unregulated pricing. “The growing trend of hospitals pushing patients to undergo dozens of unnecessary tests and unneeded procedures needs urgent scrutiny,” he noted. Vivek welcomed some of the panel’s more moderate proposals, such as a restructuring of India’s goods and services tax regime to lower costs for healthcare providers and patients, but called for broad consultations with all stakeholders before any binding policy changes are implemented.

    Dr. Reddy echoed that view, noting that before any blanket price caps are imposed, policymakers need to conduct full nationwide surveys to calculate the actual cost of delivering private care across different regions. “Healthcare costs vary widely from state to state and between large cities and small towns, so a one-size-fits-all national cap simply will not work,” he explained.

    As the debate over regulation heats up, public health experts across the board agree that the long-term solution to India’s healthcare affordability crisis lies in drastically expanding public sector healthcare capacity to reduce citizen dependence on expensive private facilities. This is a core recommendation of the government panel’s report itself.

    Currently, India’s central government spends just 1.4% of its gross domestic product (GDP) on public healthcare, falling far short of the 2.5% target set out in the National Health Policy nearly a decade ago, and a fraction of the 5% of GDP the World Health Organization recommends as a minimum for strong public health systems. The government panel’s report notes that chronically underinvestment in public secondary and tertiary care has pushed millions of Indians to seek care from private facilities, leading to the catastrophic out-of-pocket health spending that pushes 6 million Indians into poverty every year, according to World Bank data.

    “The Indian government has to step up its investment in public healthcare dramatically to reduce the ordinary person’s dependence on private hospitals,” Vivek said. Yet policymakers face a difficult balancing act: estimates show India needs an additional $300 billion in healthcare investment over the next decade to meet growing demand for care, and the vast majority of that capital will have to come from private domestic and foreign investors.

    That leaves policymakers with the unenviable task of crafting regulation that protects ordinary patients from exploitative pricing without driving away the investment India needs to expand overall care capacity. The outcome of this debate will shape the health and financial security of hundreds of millions of Indians for decades to come.

  • More than 1,000 children killed in Bangladesh measles outbreak

    More than 1,000 children killed in Bangladesh measles outbreak

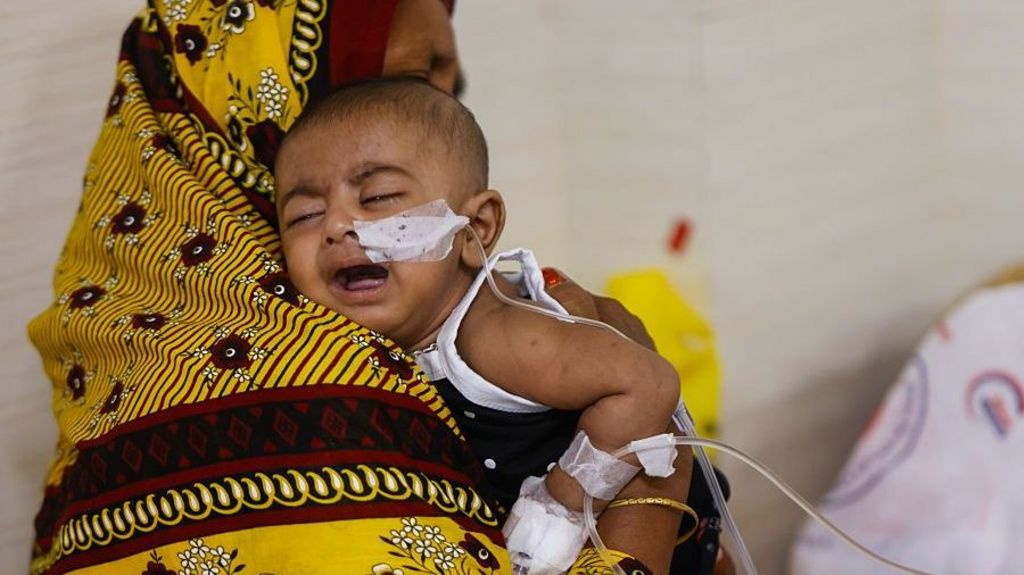
    Decades have passed since Bangladesh has faced a public health crisis of this scale: a rampant measles outbreak that has already claimed the lives of more than 1,000 children, with daily new suspected cases continuing to climb even after a nationwide emergency vaccination initiative. As of mid-September 2026, official data records more than 194,000 confirmed infections since the outbreak began accelerating in March, pushing the South Asian nation to the unenviable position of recording more measles cases than any other country worldwide this year. Up until March, both the World Health Organization (WHO) and global public health bodies had praised Bangladesh for making substantial progress toward full measles elimination, making the sudden resurgence all the more alarming.

    The unfolding crisis traces its roots to a perfect storm of overlapping systemic and public health challenges, according to UNICEF. Years of disruptions to routine childhood immunization caused by the COVID-19 pandemic left a large cohort of children unprotected against the highly contagious virus, which spreads easily through respiratory droplets from coughing, sneezing, and breathing. Bangladesh’s dense population of 178 million people further accelerated transmission, while widespread childhood malnutrition—an ongoing public health challenge in the country—has amplified the risk of severe complications and death for infected children. WHO data confirms the scope of the vaccination gap: 83% of all confirmed measles cases occur in unvaccinated children, with another 10% affecting infants under six months old, a group too young to receive routine measles vaccination and thus inherently vulnerable to the disease.

    Disputes over vaccine access and delayed public health action have added another layer of complexity to the crisis. UNICEF has alleged that the former interim government led by Muhammad Yunus delayed placing vaccine orders in 2024 while reviewing proposals from new vendors, despite repeated warnings about the growing risk of an outbreak. “We were worried about possible [vaccine] gaps increasing, and it’s unfolding into what we’re now seeing,” Miguel Mateos Muñoz, a UNICEF spokesperson, told the BBC in June. Senior health officials from Yunus’ administration have denied these claims, asserting that no vaccine shortage ever occurred. Political upheaval in the country over the past two years—including 2024 mass student-led protests that ousted long-time authoritarian prime minister Sheikh Hasina—has further disrupted public health planning and response efforts.

    More than 19.8 million children have been vaccinated through the initial emergency campaign, but public health experts agree the first phase of the response fell short of what was needed to curb transmission. Dr Mushtuq Husain, a leading Bangladeshi public health expert, told the BBC that the first campaign failed to reach enough unvaccinated children across all regions and age groups, leaving large pockets of vulnerability. “There are no shortcuts when it comes to a response,” Husain said. “The government made the right decision to jump into action. But the health workers needed to go door-to-door to make people aware of the urgency.” While the WHO has characterized the initial vaccination drive as broadly successful, it acknowledged that a significant share of target children were never reached, and transmission had already spread across every region of the country before large-scale immunization efforts could get underway. “The outbreak spread nationwide before vaccination activities were implemented, creating extensive transmission chains that take time to fully interrupt,” the WHO said in a statement.

    Starting September 26, the Bangladeshi government will launch an intensified second phase of its vaccination campaign, aimed at reaching the thousands of unvaccinated children who were missed in the first round. Right now, an average of 1,000 new suspected cases are reported every day, with eight new deaths recorded on a single Tuesday in September, and 300 additional child deaths recorded since the health ministry declared the outbreak under control in June. Hospitals across the country remain overwhelmed by the surge of patients: during a BBC visit to facilities in June, dozens of families were forced to wait and rest on blankets on hospital floors, with one major facility operating at more than twice its intended patient capacity. While the health ministry previously acknowledged the strain on the national health system, it argued that the pressure was unavoidable given Bangladesh’s large population and claimed the crisis had already been contained.

    Bangladesh is not an isolated case: measles outbreaks have reemerged across the globe in recent years, even in nations that had previously achieved elimination status. The United Kingdom lost its official measles elimination status earlier this year, and the United States has recorded consistent increases in cases since 2020. In both high-income nations, vaccination coverage for children under five years old falls short of the 95% herd immunity threshold required to stop sustained measles transmission, underscoring the global nature of the growing threat of vaccine-preventable disease resurgence.

  • Fiji declares HIV a national emergency as cases surge

    Fiji declares HIV a national emergency as cases surge

    In a significant response to a rapidly worsening public health crisis, the Pacific island nation of Fiji has officially declared a national emergency following a sharp surge in HIV infections that has stretched the country’s already fragile health services to breaking point. As national authorities move to scale up testing, treatment, and preventive care across the archipelago, new data reveals the alarming pace at which the epidemic has grown over the past five years.

    Today, roughly one out of every 60 adults in Fiji lives with the bloodborne virus, a marked jump from the 2020 figure of one in 167. Compounding the crisis, the country has recorded a steady rise in infant deaths linked to HIV-related complications, marking one of the most devastating outcomes of the unchecked spread. In 2025 alone, Fijian health authorities recorded 2,016 new HIV diagnoses, according to Health Minister Antonio Lalabalavu, who emphasized that a standard outbreak-level response is no longer adequate to contain the crisis.

    Health experts and non-governmental organizations have traced the rapid spread of the virus to a dangerous combination of rising intravenous drug use, unprotected sexual activity, needle sharing, and a high-risk practice known locally as “bluetoothing” or “hotspotting.” This practice, which has been tied to HIV surges across parts of Africa and the Pacific, sees multiple drug users inject the blood of an already intoxicated person to achieve a collective high. It has gained traction in Fiji for two key reasons: it allows users to split the cost of a single dose of drugs, making intoxication cheaper, and it requires only one syringe, a resource that is already difficult to access for many drug users in the country.

    To address the root drivers of transmission, the Fijian government is launching a targeted syringe and needle distribution program as a core component of its emergency response. Lalabalavu confirmed that the country already holds adequate stockpiles of sterile syringes and needles, and legislative amendments will soon be introduced to parliament to clear the way for the program’s full nationwide rollout. The minister has also issued a public call for at-risk community members to access voluntary testing, stressing that stigma around HIV status remains a major barrier to care.

    “No one should be ashamed, threatened, or excluded because of their HIV status,” Lalabalavu said. “Stigma drives people away from the very services that can help them.”

    Alarmingly, UNAIDS data from 2025 shows that among the estimated 9,100 Fijians living with HIV, only 39% are aware of their status, and just 22% are accessing life-saving antiretroviral treatment. This falls drastically short of the global average, where 78% of people living with HIV have access to consistent treatment.

    Jason Mitchell, head of Fiji’s national HIV response taskforce, warned that bringing the epidemic under control will be a years-long process, far different from the rapid two-year turnaround seen during the COVID-19 pandemic. “It will take upwards of five years for [Fiji] to get on top of the epidemic,” Mitchell told ABC News in an interview. “It’s a long-term programme, it’s not something like Covid that’s turned around in two years. HIV is very different.”

    Mitchell added that the surge has placed unprecedented pressure on Fiji’s under-resourced health system. “For a health system that’s already struggling, to have people who should really be well because there’s treatment available taking up beds in hospitals and sitting in outpatient… Our clinical services has really been under a lot of pressure,” he said.

    The United Nations programme on HIV and AIDS (UNAIDS) has expressed support for Fiji’s emergency declaration, noting that the move signals the urgent whole-of-society response needed to reverse the epidemic’s trajectory. Winnie Byanyima, executive director of UNAIDS, said the crisis in Fiji serves as a critical wake-up call for the global community.

    “It is also a stark reminder to the world that Aids is not over,” Byanyima said. “HIV epidemics can change quickly, and countries need health and community systems that are ready to respond urgently.”

  • Pennsylvania officials report fourth measles-associated death in ‘surge’ of cases

    Pennsylvania officials report fourth measles-associated death in ‘surge’ of cases

    The United States is facing its most severe measles outbreak in decades, with a fourth death now confirmed in Pennsylvania, according to state public health officials. The latest fatality, an 18-year-old from Mifflin County, died from acute encephalomyelitis, a rare and life-threatening neurological complication triggered by the highly contagious measles virus, local coroner officials confirmed.

    So far in 2025, Pennsylvania has recorded more than 600 confirmed measles cases, with the vast majority concentrated in Lancaster County. All four recent deaths in the state are tied to the ongoing outbreak: two unvaccinated adults — the 18-year-old and a 40-year-old woman who died of measles-induced respiratory failure last week — and two infants. Public health protocols recommend children receive their first dose of the combined measles, mumps, and rubella (MMR) vaccine at 12 months of age, meaning young infants are not yet eligible for protection. Local coroners and state health officials have verified that both infant deaths were directly linked to measles complications: one six-week-old child, born with the rare genetic condition Amish lethal microcephaly, died from measles infection in mid-August, while a second infant died after a measles-caused enlarged spleen ruptured, leading to fatal internal bleeding.

    Once declared eliminated in the U.S. in 2000 through widespread successful vaccination programs, measles has made a devastating comeback in recent years. This year alone, the country has seen the highest number of measles deaths since the 1990s. In 2024, an outbreak centered in Texas’ Mennonite community claimed three lives, including two children. Public health experts universally attribute this resurgence to rising vaccine hesitancy across the country, which has driven immunization rates below the 95% threshold required to maintain herd immunity — the level of vaccination needed to stop sustained community spread of the virus.

    The rising death toll has sparked open political tension between Pennsylvania’s Democratic Governor Josh Shapiro and U.S. Health Secretary Robert F. Kennedy Jr., a prominent vaccine skeptic. Shapiro has publicly accused Kennedy of spreading dangerous misinformation about MMR vaccines, and confirmed he would withhold personal details about the deceased from the top federal health official to protect victim families’ privacy. Kennedy has cast doubt on official findings that the two infant deaths were caused by measles, claiming the deaths were due to unrelated preexisting conditions and accusing Shapiro of political grandstanding.

    Following the public dispute, Pennsylvania’s Department of Health released a statement defending its death investigations, noting that it had conducted rigorous joint reviews with local coroner offices to confirm each death was measles-related. “These investigations included confirming clinical evidence of a measles infection, a positive laboratory test, and that the death was not due to an unrelated cause,” the department said. The U.S. Centers for Disease Control and Prevention has so far declined to update its national death count pending completion of formal reviews, a position Kennedy has cited to back his questioning of the state’s findings.

    A November review by global health bodies will decide whether the U.S. will officially lose its measles elimination status, a designation Canada lost in 2024. Kennedy, who has led a major overhaul of U.S. vaccine policy since taking office, has faced widespread condemnation from public health experts who argue his ambiguous and often critical messaging around the safe, effective MMR vaccine has undermined national efforts to contain the growing outbreak. While Kennedy has acknowledged that the worsening measles crisis is a global issue, telling a Senate committee last month that “the whole world had their worst measles year,” critics say his policy changes and anti-vaccine rhetoric have accelerated the outbreak in the U.S.

  • Zambians warned not to eat dead wildlife after anthrax kills dozens of animals

    Zambians warned not to eat dead wildlife after anthrax kills dozens of animals

    A new anthrax outbreak in a northern Zambian wildlife management area has killed dozens of wild animals and infected a dozen local residents, prompting emergency public health warnings from Zambian authorities. The outbreak, first detected in July in the Munyamadzi Game Management Area of Muchinga Province, has already claimed the lives of 46 hippos, 8 elephants, 5 buffalo, and one crocodile, according to the country’s Disaster Management and Mitigation Unit. Norman Chipakupaku, the unit’s national coordinator, explained that local communities often rely on the meat of naturally deceased wild animals for sustenance, leaving residents exposed to the deadly bacteria. To date, 12 people have been confirmed to have contracted anthrax after eating meat from the infected carcasses. All 12 patients are currently receiving medical care, and no human fatalities have been recorded from this latest outbreak. In response to the developing situation, Zambian officials have issued urgent guidance for residents across the affected region: people are banned from consuming, selling, distributing, or handling meat from animals that died suddenly or from unexplained causes. The public has also been instructed to report any unusual wildlife deaths to local authorities immediately, and all hunting activities in the affected zone have been suspended until officials can map the full spread of the outbreak and assess associated public safety risks. As of the latest update, field surveillance teams and laboratory researchers are still working to determine the full geographic scope of the outbreak. Anthrax, an infectious disease caused by the spore-forming bacterium Bacillus anthracis, is endemic to Zambia, where the bacteria can remain dormant as spores in soil for decades. The pathogen primarily targets grazing animals, often causing rapid sudden death, and can jump to humans through contact with contaminated animal products or infected tissue. While anthrax is endemic in the country, human fatalities from outbreaks remain rare. However, Zambia has faced several large-scale outbreaks in recent years. In 2023, the country recorded what public health officials described as an “unprecedented” outbreak that spread across nine of Zambia’s 10 provinces and killed four people. The deadliest recorded event in recent history dates back to 2011, when a major outbreak linked to infected hippo meat caused more than 500 human cases and five deaths. Public health teams continue to monitor the situation closely as work to contain the current outbreak progresses.

  • Largest US outbreak of explosive diarrhoea parasite is over, officials say

    Largest US outbreak of explosive diarrhoea parasite is over, officials say

    After months of widespread transmission that impacted dozens of U.S. states and left thousands of people ill, the largest recorded cyclospora outbreak in modern U.S. history has officially come to an end, U.S. Centers for Disease Control and Prevention (CDC) officials announced Friday.

    The parasitic intestinal infection, which causes severe, explosive diarrhea, has been linked to two deaths in Michigan and hospitalized 570 people since the outbreak began earlier this year. Both of the deceased individuals had serious pre-existing underlying health conditions that left them more vulnerable to complications from the infection and related dehydration, Michigan health authorities confirmed. While cyclospora infections are rarely fatal for otherwise healthy people, the outbreak’s scale and impact have drawn widespread public attention and public health intervention.

    Investigators have traced the majority of confirmed cases to contaminated lettuce imported from central Mexico by produce supplier Taylor Farms, which distributes fresh leafy greens to countless food retailers and restaurant chains across the United States. Following the link being established, Taylor Farms issued a voluntary nationwide recall of all lettuce sourced from its central Mexican growing operations, and major fast-food chain Taco Bell moved quickly to remove the supplier’s lettuce from all menu items to limit further exposure.

    CDC data shows that as of early September, nearly 20,000 confirmed cyclospora cases have been reported across all 49 U.S. states and the District of Columbia since May 1, with total hospitalizations topping 1,000. Of that total, more than 12,000 cases were tied to the multi-state outbreak linked to the Mexican lettuce. Public health experts emphasize that the true number of infections is almost certainly far higher than the confirmed count, as many mild cases go unreported by patients who do not seek medical care. It is also important to note that while the majority of cases were connected to the contaminated lettuce, thousands of reported illnesses have not yet been linked to that source.

    In its official advisory declaring the outbreak over, the CDC stated that new case counts have dropped significantly after the recall and menu changes. However, agency officials added that investigations into the full origin and spread of the parasite will continue to help prevent similar large-scale outbreaks in the future.

    This outbreak marks a stark increase in cyclospora cases compared to previous years. Prior to 2025, the worst year for cyclospora infections in the U.S. was 2019, when just 4,700 cases were recorded nationwide. Beyond U.S. borders, public health officials in the United Kingdom have also issued warnings to travelers after multiple returning UK residents contracted the parasite during trips to the U.S. this year.

    Cyclospora is a microscopic parasite that spreads exclusively through contaminated food or water. Infection, called cyclosporiasis, most commonly causes severe intestinal distress including the explosive diarrhea that has become synonymous with this outbreak, and can lead to dehydration if left untreated.