分类: health

  • Transplanted pig kidney works in US man’s body for record 271 days

    Transplanted pig kidney works in US man’s body for record 271 days

    A groundbreaking development in organ transplantation has set a new record: a kidney harvested from a genetically modified pig has functioned normally in a human patient for 271 days, the longest successful duration ever recorded for this experimental procedure, according to medical teams at Mass General Brigham in the United States. The case, recently published in the *Lancet* medical journal, offers a glimmer of hope amid a persistent global crisis of organ donor shortages that leaves thousands of patients waiting for life-saving treatment every year.

    The recipient of the experimental transplant was 66-year-old Tim Andrews, who was living with end-stage kidney disease caused by type 2 diabetes. Like thousands of patients across the United States and the United Kingdom, Andrews faced a years-long wait for a human donor kidney. He was told it could take up to seven years to reach the top of the transplant waiting list, while the average life expectancy for a patient on long-term dialysis is just five years. “I had a little bit of a shortage of time… it becomes very depressing,” Andrews recalled of his ordeal before the procedure. When offered the option of a pig kidney xenotransplant—an organ sourced from another species—he described the opportunity as “hope” and the “light at the end of the tunnel.”

    The transplant was performed on January 25, 2025. From the moment surgeons connected the pig kidney to Andrews’ blood vessels, the organ began working to filter his blood, eliminating the immediate need for regular, time-consuming dialysis appointments that had upended his daily life. The pig kidney continued to function without critical failure for 271 days, a new global benchmark for the field of xenotransplantation. Although early signs of immune rejection were detected, clinicians successfully managed the reaction by adjusting Andrews’ immunosuppressant medication. Eventually, after approximately six months, the pig kidney began to fail as inflammation developed and damage accumulated in its blood vessels. It was removed in October 2025, after which Andrews returned to short-term dialysis for 82 days. In January 2026, he received a donor human kidney, which has continued to function well as of the latest clinical updates.

    Notably, clinicians report that the pig kidney’s failure was not triggered by the acute antibody-mediated immune rejection that has doomed early xenotransplant attempts. The exact cause of the organ’s decline remains under investigation, marking a key area for future research.

    Pigs have long been identified as the most promising candidate species for human xenotransplantation: their organs are roughly the same size as human organs, and controlled farming of pigs for medical use has been refined over decades of research. However, using unmodified pig organs in humans triggers an immediate, devastating immune response, where the body identifies the foreign tissue and launches an attack that destroys the organ within minutes. To overcome this barrier, researchers developed genetically modified Yucatan miniature pigs, with 69 genomic edits designed to “humanize” their organs:
    – These edits remove molecular markers on pig cells that the human immune system recognizes as foreign
    – They add human genetic material that acts as biological camouflage, hiding the pig tissue from immune detection
    – Additional modifications disable endogenous retroviruses embedded in pig DNA, eliminating the risk of cross-species viral infection

    Mass General Brigham’s transplant team emphasizes that their successful 271-day outcome proves that genetically modified pig kidneys can act as a life-saving “bridge” for patients waiting for a human donor organ. For patients like Andrews, this bridge means freedom from the relentless cycle of dialysis while they wait, and a far higher chance of surviving long enough to receive a permanent human transplant.

    Dr. Leonardo Riella, from the center for transplantation sciences at Mass General Brigham, framed the ongoing organ shortage as a public health crisis. “We are working really hard to bring hope and we truly feel that xenotransplantation can be an alternative for patients who don’t have a living donor where we could potentially bypass dialysis and get them to a transplant,” he said.

    g the milestone, the research team’s published analysis acknowledges that the case highlights both the enormous promise of xenotransplantation and the critical challenges that remain to be solved before the procedure can become widely available to patients in need. Across the globe, 100,000 people are currently waiting for a kidney transplant in the U.S. alone, with only around 25,000 transplants performed annually. More than 7,000 patients are on the UK’s kidney waiting list, making the search for alternative organ sources a pressing public health priority.


  • 5 challenges Congo faces in containing its fast-moving Ebola outbreak

    5 challenges Congo faces in containing its fast-moving Ebola outbreak

    In a sobering update on the escalating Ebola crisis ravaging eastern Democratic Republic of the Congo, the Africa Centers for Disease Control and Prevention (Africa CDC) announced Thursday that local health authorities are pivoting to a new village-centered strategy to curb transmission, after the virus outpaced existing containment and tracking efforts.

    According to the continental public health agency, the current outbreak has not yet reached its peak, marking a far more severe public health emergency than the devastating 2014–2016 West African Ebola epidemic, which remains the deadliest on record with more than 11,000 fatalities. Africa CDC data confirms the current outbreak has already recorded six times as many confirmed cases and five times as many deaths as that prior crisis.

    Since the outbreak was declared in mid-May, the virus has jumped from just three initial health zones to 60 across the country, with 6,250 total confirmed cases and 3,039 deaths as of the latest government count. Ongoing insecurity, mass population displacement, and frequent large-scale population movements have been the primary drivers of the virus’s rapid spread. The outbreak is concentrated in Ituri province, which is also the epicenter of a persistent rebel conflict in eastern Congo – a dual crisis that has complicated nearly every aspect of outbreak response.

    A new analysis this week from the U.S. Centers for Disease Control and Prevention (U.S. CDC) identifies five critical gaps that continue to undermine Congo’s Ebola response, even as authorities adjust their strategy.

    First, community-based surveillance systems remain drastically underdeveloped. Rapid investigation of potential cases, early detection, contact tracking, and transmission slowdown are all hampered by this gap. Delayed case detection, widespread community reluctance to report suspected infections, and insufficient engagement with local populations have all led to entirely preventable deaths. Recent Africa CDC data underscores this failure: at least 63% of all fatalities recorded in the past week occurred outside of dedicated Ebola treatment centers, meaning most infected people never accessed life-saving care.

    To address this foundational gap, authorities are now rolling out the new village-centered approach, which centers on partnering directly with local community leaders to build trust and improve collaborative work with residents. But Yap Boum, head of emergency preparedness and response at Africa CDC, noted that trust-building in the middle of an active conflict and outbreak is far from simple. “Building that trust in the middle of an outbreak is quite complex,” Boum explained, referencing the ongoing insecurity that leaves residents deeply suspicious of outside actors.

    The second critical gap is persistent failure to scale up effective contact tracing, an essential tool for stopping Ebola chains of transmission. While response teams have followed up with 81% of *officially listed* contacts of confirmed cases, this statistic hides a stark reality: thousands of unrecorded contacts have never been reached for monitoring. Africa CDC estimates that confirmed cases recorded in the three weeks prior to the update should have generated approximately 97,600 total contacts, based on an average of 60 contacts per confirmed case. To date, only 19% of these total expected contacts have successfully been traced, leaving hundreds of potential transmission chains unmonitored.

    Third, experts warn that existing treatment and isolation capacity remains insufficient to meet projected need. By late August, treatment centers had expanded their total capacity to more than 1,300 beds, with a current occupancy rate of 67% (holding 869 patients). However, public health teams are calling for additional treatment and isolation centers and beds across affected health zones to prepare for the wave of undetected cases that experts expect to emerge. Many high-risk health zones are located in areas inaccessible to response teams, while widespread community distrust of health authorities leads to many cases going unreported for weeks.

    Fourth, limited laboratory testing capacity continues to delay case confirmation and timely treatment. The World Health Organization reported last month that many treatment and transit centers in Ituri, the outbreak’s epicenter, are already operating at full saturation, while North Kivu – the second-most affected province – lacks enough specialized referral facilities for severe cases. Frontline health workers at existing treatment centers are also suffering from extreme burnout. Jeannot Krikeija, who works at an Ebola treatment center in Bunia, Ituri’s capital, described the relentless toll of the crisis: “Ebola is tiring us all the more because we don’t know when this scourge will end. This ordeal is unbearable for me.”

    The fifth and final gap identified by the U.S. CDC lies in safe burial practices, a critical intervention given that Ebola spreads through direct contact with bodily fluids, and the bodies of deceased victims remain highly infectious. While authorities have deployed safe burial teams to respond to the more than 3,000 Ebola deaths to date, major gaps remain in execution across affected health zones. In Ituri and other high-risk areas, burial teams have been attacked multiple times, often by grieving family members who wish to carry out traditional burial customs for their loved ones. It remains common for community members to gather within meters of Ebola victim coffins during burials, putting hundreds of people at risk of new infections.

    As the new village-centered strategy rolls out, public health agencies across the continent continue to warn that the outbreak’s trajectory remains unpredictable, with sustained transmission expected for the foreseeable future without targeted investment to close the remaining response gaps.

    AP writers Constant Same Bagalwa in Bunia, Congo and Mike Stobbe in New York contributed reporting to this article.

  • Congo’s Ebola outbreak shows no signs of slowing as deaths top 3,000

    Congo’s Ebola outbreak shows no signs of slowing as deaths top 3,000

    BUNIA, Democratic Republic of Congo – A rapidly expanding Ebola outbreak in eastern Congo has outpaced international and local containment efforts, crossing a grim milestone this week with more than 3,000 fatalities recorded across over 6,100 confirmed cases, new government data released Wednesday confirms.

    According to figures from Congo’s Ministry of Health, the outbreak has reached 6,186 confirmed infections since the World Health Organization declared it a global public health emergency in mid-May, with 3,007 confirmed deaths to date. Health officials confirm this is now the fastest-growing Ebola outbreak in recorded history, with transmission accelerating far more quickly than contact tracing and public health teams can respond.

    The crisis has upended daily life for communities across affected regions, forcing many residents to flee high-transmission zones to seek safety. Jean-Claude Angwanzia, a Bunia resident who relocated from Mambassa in the Ituri province epicenter, described widespread insecurity and a lack of visible public health support. “I had to flee the area because of the danger looming over us,” he said, noting infected bodies were often mishandled and health workers were rarely seen in the hardest-hit communities.

    Local economic and daily activity has slowed dramatically as fear of transmission spreads. Papy Baraka, a public transportation driver based in Bunia, told reporters he has been forced to reduce the number of passengers he carries per trip to lower exposure risk. “The disease puts everyone at risk, and daily life has slowed to a crawl. We are afraid,” he said.

    In recent weeks, the virus has expanded its reach at an alarming rate: just last week, two additional health zones in North Kivu province reported their first cases, pushing the total number of affected jurisdictions to 60 across six Congo provinces. The fatality rate in North Kivu is significantly higher than in other impacted regions.

    A new assessment released Tuesday by the U.S. Centers for Disease Control and Prevention (CDC) echoed on-the-ground accounts of failing containment, concluding current response efforts “remained below established response targets.” The report warned that the virus’s spread across dozens of health zones signals “uncontrolled expansion of the outbreak.” CDC data shows only 15% to 20% of new confirmed cases stem from known transmission chains, meaning the vast majority of new infections are occurring through unknown, untraced contacts.

    Multiple interconnected factors have fueled the outbreak’s unrelenting spread. The eastern Congo region where the virus is concentrated has long grappled with ongoing armed conflict, which disrupts access to impacted communities. Health care workers responding to the crisis have also faced repeated targeted attacks, and have staged multiple strikes over delayed pay and inadequate working conditions. A highly mobile population of artisanal miners moving across regional borders, combined with long-underfunded and underdeveloped local health infrastructure, has further hampered response efforts. Even the recent reopening of schools in the outbreak’s epicenter has sparked widespread concern about rapid transmission among crowded student populations.

    The World Health Organization warns the outbreak is on track to surpass the deadliest Ebola event in history: the 2014-2016 West African regional outbreak that killed more than 11,000 people across three countries. The Africa CDC added that official case counts are likely a significant undercount, estimating the actual number of infections could be three times higher than reported due to weak surveillance and contact tracing systems. Even at the current confirmed count, this is already the deadliest Ebola outbreak in Congo’s history.

    Unlike previous Ebola outbreaks that have been effectively contained with existing vaccines, the current outbreak is caused by the rare Bundibugyo Ebola virus, for which no fully approved vaccine or targeted treatment currently exists. A small number of vaccine candidates are in late-stage development, however, and last week the Congolese government launched distribution of the Ervebo vaccine – which successfully controlled previous Ebola outbreaks – to front-line health workers in Kisangani, the capital of northeastern Tshopo province. WHO officials note Ervebo may provide at least partial protection against the current variant.

  • Congo authorities report more than 6,000 confirmed Ebola cases and nearly 3,000 deaths

    Congo authorities report more than 6,000 confirmed Ebola cases and nearly 3,000 deaths

    In a grim update released Monday, Democratic Republic of Congo health authorities confirmed that the nation’s unprecedented fast-spreading Ebola outbreak has crossed a devastating threshold, with more than 6,000 confirmed cases and 2,911 fatalities recorded to date. Amid the rising death toll, authorities did highlight one small positive development: over 1,360 patients have successfully recovered from the virus, a trend officials described as encouraging for frontline response teams.

    The outbreak, which is centered in eastern Congo, is expanding against a backdrop of extraordinary operational challenges. Chronic regional insecurity, mass population displacement, a recent strike by frontline health workers, and constant large-scale population movements have all combined to accelerate transmission. Displacement camps, where residents already live in overcrowded, unsanitary and precarious conditions, are emerging as particularly high-risk sites for widespread infection. Just last week, health officials confirmed the virus has reached two more previously unaffected health zones, bringing the total number of impacted areas across the region to nearly 60.

    The World Health Organization (WHO) has repeatedly warned that the outbreak remains completely out of control, and current projection models indicate it could soon overtake the 2014–2016 West Africa Ebola epidemic as the deadliest outbreak on record. That earlier outbreak killed more than 11,000 people across Guinea, Liberia and Sierra Leone.

    Complicating response efforts further, violent attacks against response teams have become increasingly common. On Saturday, an Ebola response team deployed to the outskirts of Mambasa, a town in Ituri province, came under attack while working to safely recover an Ebola-related death. A group of young men armed with machetes stormed the funeral site where the team was operating, forcing all responders to evacuate the area and leaving one team member injured. Floribert Magene, a member of the response team, told the Associated Press that frontline workers are urgently calling for improved protection. “We demand greater security so we can operate in the field and do our work without endangering our lives,” Magene said.

    Unlike many previous Ebola outbreaks, this current event is caused by the Bundibugyo strain, a rare variant of the virus for which no officially licensed vaccine or specific treatment currently exists. In a proactive step last week, Congolese health authorities launched a vaccination campaign for health care workers and other frontline response staff using Ervebo, a vaccine that proved effective against Zaire Ebola — the more common strain that caused previous major outbreaks. Clinical trials for a Bundibugyo-specific vaccine are currently ongoing to develop a targeted tool for fighting this outbreak.

    Health officials retroactively determined that while the outbreak was formally declared in mid-May, the virus had begun spreading quietly through communities as early as February. It has since expanded from just 3 initial health zones to 60, with data showing that the majority of new cases and deaths are occurring outside of monitored contact tracing networks, spreading undetected within local communities.

    Public health control measures, including limits on large public gatherings, social distancing guidelines, and airport closures, have upended daily life across six affected Congolese provinces. Ituri province, which is also grappling with persistent rebel violence that has displaced thousands of residents, has been hit particularly hard by these disruptions. While the Congolese government has rolled out limited interventions, including installing sanitary and medical screening equipment at high-traffic sites, public health advocacy groups emphasize that far more work is needed to build trust with local communities and expand access to care.

    Although neighboring Uganda declared itself officially Ebola-free last month after containing a small cross-border outbreak, the WHO warned last week that the risk of future cross-border spread remains elevated, as long as the large-scale outbreak continues to rage in eastern Congo.

  • Africa’s male midwives are rare but increasing in the fight against pregnancy deaths

    Africa’s male midwives are rare but increasing in the fight against pregnancy deaths

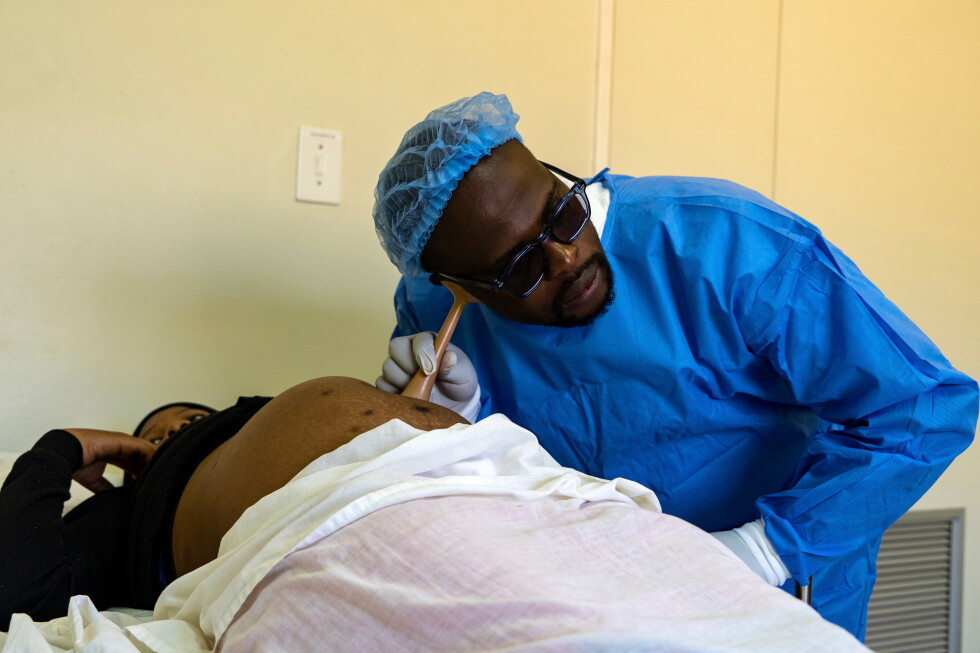
    On a crisp, cold morning in the mountainous Southern African kingdom of Lesotho, Ntlhane Sehloho slung his backpack stuffed with critical medical gear over his shoulders and set off on a three-hour trek along winding, unpaved gravel roads. His destination: Mpharane Health Center, a small clinic tucked into a remote valley that serves scattered rural communities with limited access to advanced care.

    Sehloho occupies a role once almost unheard of in this part of the world: he is a male midwife. When he stepped through the clinic’s doors on this particular morning, a group of waiting women exhaled in relief — some expecting their first child, others balancing fussy infants on their backs, all seeking the routine prenatal and postnatal care Sehloho has provided for 20 years.

    For generations, midwifery has been strictly regarded as women’s work in Lesotho’s largely conservative society. But facing one of the world’s worst maternal mortality crises, the country has launched an urgent push to recruit more men into the profession, upending long-held cultural norms to save lives. According to United Nations data, Lesotho records roughly 530 maternal deaths for every 100,000 live births — a rate more than two and a half times the global average of 200.

    This crisis is not unique to Lesotho. Sub-Saharan Africa, the world’s fastest-growing region, accounts for 70% of all global maternal deaths, with roughly 180,000 pregnancy-related fatalities recorded across the continent each year. Severe staffing shortages in remote rural clinics, where most of Lesotho’s population lives, have only worsened the crisis. With just over 2 million people nationwide, the country’s rural health posts are chronically understaffed, leaving thousands of pregnant women without access to skilled care during childbirth.

    Global health bodies have sounded the alarm for years over this shortage. World Health Organization data estimates that men make up less than 1% of the global midwifery workforce. Both the WHO and UNICEF have called for expanding recruitment to all qualified candidates, regardless of gender, to close gaping gaps in emergency obstetric care.

    Sehloho is one of an estimated 300 male midwives now practicing across Lesotho — a milestone that would have been unthinkable a generation ago. The Lesotho government does not track midwifery data by gender, so an exact count is not available, but recruitment efforts over the past two decades have steadily grown the share of men in the field. Sehloho never set out to become a midwife: as a high-achieving student, he originally planned to work as a nurse, driven by childhood memories of preventable tragedy in his rural home village.

    “Our village was far away from the health facility, so most pregnant women delivered at home. We were still young, we were not supposed to see that, as some were dying,” he recalled. “I didn’t understand how far they had to travel just to get care.”

    After he finished his nursing training, Lesotho’s health authorities encouraged Sehloho and other male nursing graduates to pursue additional midwifery training, part of a targeted strategy to expand care access to underserved rural areas. The strategy has already delivered measurable results: UNICEF data shows that 92% of births in Lesotho now are attended by a trained health provider, up from a far lower share just two decades ago.

    Lesotho’s government says the core goal is saving lives, and that gender should never stand in the way of that mission. “I think the system and the community is starting to slowly accept that gender should not matter when it comes to this issue of delivery,” explained Dr. Llang Maama, acting director of health services at Lesotho’s Ministry of Health. She acknowledged that a small number of patients still report discomfort with male midwives, and the health system formally accommodates those requests when possible. “But in the urgency of childbirth, there isn’t always time to choose,” Maama added.

    For Sehloho, acceptance comes down to building trust, one patient at a time. A talkative, quick-witted provider, he makes a point of putting pregnant women at ease from their very first prenatal visit, often sharing his own background growing up in a rural Lesotho community and highlighting his 20 years of experience delivering babies. “We are a very cultural and traditional African society,” he said.

    Blandina Motaung, a representative for the United Nations Population Fund, which partners closely with Lesotho’s midwifery community, said public reactions to male midwives remain mixed, but many patients are surprised by the unique strengths men bring to the role. Many patients report that male midwives tend to be more gentle and less strict than their female counterparts during consultations, she said. During prenatal checks, Sehloho routinely pauses after taking blood pressure or measuring fetal progress to ask patients if they are comfortable, a small habit that has won him loyalty among the community he serves.

    Motaung noted that while most female midwives have personal experience with childbirth, men’s lack of that firsthand experience often makes them more attentive to small changes and warning signs that can signal complications. “For the men, because they have not been through the process, they become more vigilant and more attentive to the nitty gritties, and that in itself improves the quality of care that they provide,” she explained.

    Patients across the country are slowly adapting to the new norm. Mpolokeng Mafereka, a 21-year-old patient at Mpharane Health Center, said she still prefers care from a female provider, but has grown accustomed to seeing Sehloho when he is the only clinician available. “I’m used to being treated by women,” she said.

    But 21-year-old Bonolo Tebello, another patient at the clinic, said she has never had concerns about seeing a male midwife. “I’m happy to be treated by a male because they still provide the same level of care,” she said. “Even when one arrives late for a check-up, they just treat you like any other person who arrived on time.”

    This reporting is part of AP News’ Africa Pulse series, supported by a grant from the Gates Foundation. The Associated Press maintains full editorial control over all funded content.

  • Dutch institute issues ‘red alert’ over Trump-shaped ecstasy pills

    Dutch institute issues ‘red alert’ over Trump-shaped ecstasy pills

    A leading Dutch research institute focused on drug addiction and mental health has sounded an urgent nationwide warning over a dangerous batch of counterfeit ecstasy pills molded into the shape of former U.S. President Donald Trump’s head, which carry potentially fatal health risks for users.

    The Trimbos Institute, headquartered in Utrecht, confirmed that multiple units of the illicit pills were submitted to official drug testing facilities across the Netherlands throughout August 2026. Laboratory analysis confirmed that the tablets contain an extremely high concentration of PMMA, short for para-methoxymethamfetamine, a synthetic stimulant chemically similar to MDMA—the primary active compound in recreational ecstasy.

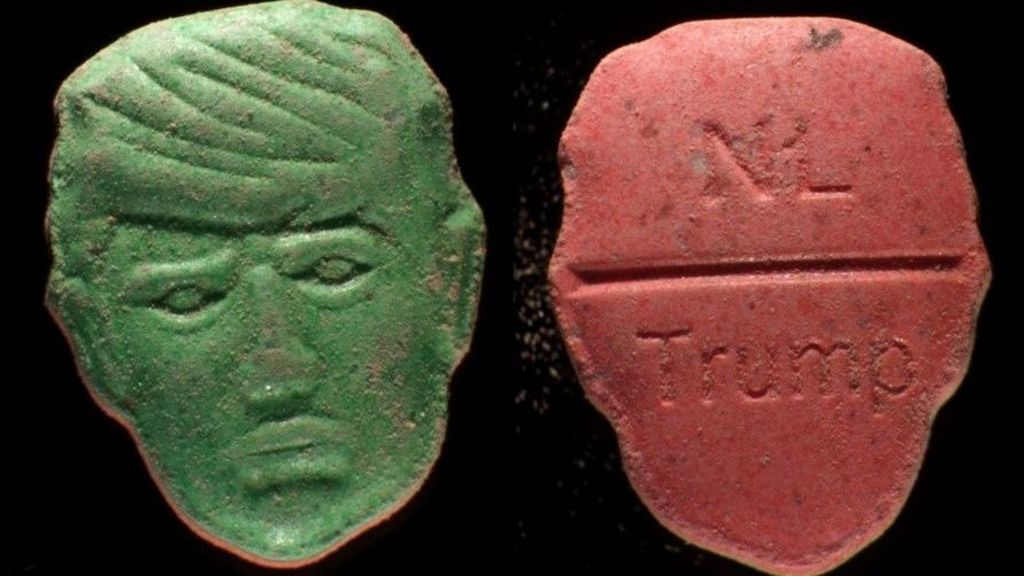
    In an unambiguous public safety advisory, the institute stressed that the pills must never be consumed, warning that ingestion can lead to rapid, life-threatening overheating of the body that often results in fatal outcomes. Officials have released public images of the contraband to help users identify the dangerous tablets: one side bears a sculpted likeness of Trump’s face, while the reverse is stamped with the words “Trump” and “NL” to mark its presumed origin in the Netherlands. Two variant designs have been identified so far: one with yellow and blue coloring, and a second featuring red and green detailing.

    Unlike standard MDMA, which produces almost immediate psychoactive and stimulating effects, PMMA acts much more slowly on the body and often lacks the characteristic energizing high users expect from ecstasy. This delayed reaction creates a critical risk of overdose, the institute explained, as users frequently take additional doses believing the first pill did not work, resulting in a toxic buildup of the chemical in the system. Symptoms of PMMA poisoning include severe nausea, elevated heart rate, and uncontrollable convulsions, which can set in several hours after consumption.

    Anniek Groothuis, a spokesperson for the Trimbos Institute, told the Associated Press that as of the advisory’s release, the institute has not received reports of deaths or life-threatening illness linked to this specific batch of pills. Even so, public health officials have emphasized the urgent need for awareness to prevent preventable fatalities.

    While the production, distribution, and possession of ecstasy remain illegal under Dutch law, a 2024 official government report highlights the drug’s persistent popularity as a common party substance across the country. The report noted that in 2022 alone, a record 550,000 Dutch residents reported using ecstasy at least once that year, underscoring the ongoing public health risk posed by adulterated illicit drugs.

    This is not the first incident of Trump’s likeness being used to brand illegal ecstasy pills. Back in 2017, German law enforcement seized roughly 5,000 carrot-colored Trump-shaped ecstasy tablets that investigators believe were marketed online under the provocative slogan “Trump makes partying great again.”

  • Ingham’s boss gives stark chicken price warning as H5 bird flu crisis spreads

    Ingham’s boss gives stark chicken price warning as H5 bird flu crisis spreads

    As the H5 avian influenza outbreak continues its spread across Australian wildlife, the head of the nation’s largest poultry producer has issued a clear warning that consumers will soon face higher retail prices for chicken, driven by rising industry costs tied to the growing public and animal health crisis.

    Edward Alexander, chief executive and managing director of Ingham’s Group, which supplies approximately 40% of all chicken meat consumed in Australia, outlined the mounting cost pressures facing the domestic poultry industry during a recent investor meeting. Alexander told shareholders that even without a single confirmed outbreak of the virus among the country’s commercial poultry flocks to date, the industry is already shouldering an extra $130 million in additional costs. These costs stem from a confluence of factors: enhanced biosecurity measures to prevent the virus, soaring feed prices driven by global inflation and geopolitical instability in the Middle East, and ongoing surveillance protocols.

    According to Alexander, these expanded costs will inevitably pass through to end consumers. “Retail pricing moves more with changes to the cost base … so we will see that take effect,” he stated.

    The spreading virus represents an unprecedented and serious threat to Australia’s commercial poultry sector, Alexander emphasized. In response to the growing risk, Ingham’s has already dispatched a team of senior executives to Europe, where nations have spent years navigating widespread H5 bird flu outbreaks, to gather critical insights and best practices for biosecurity management. “We take this risk extremely seriously,” Alexander said, noting that predicting the exact timing and location of a commercial outbreak remains impossible.

    Despite the grave risk, Alexander expressed confidence in Ingham’s preparedness, positioning the company as better resourced to handle an outbreak than any other competitor in the Australian market. Over the past months, the firm has poured significant resources into prevention protocols, widespread surveillance, contingency scenario planning, and rapid response frameworks to mitigate the risk of the virus reaching its operations. Its geographically diverse national production network, Alexander explained, adds an extra layer of resilience: “An outbreak in one location does not automatically translate into disruption across our broad network. We have the ability to isolate affected areas, protect other parts of the network and redirect production and supply.”

    Alexander also confirmed that so far, the spread of bird flu in Australian wildlife has not dented consumer demand for chicken products. He credited clear public communication around the fact that properly handled poultry remains safe for human consumption for the steady demand, noting “we’re not seeing any impact on demand at the moment.”

    Alexander’s warning comes on the heels of a series of alarming new developments in the spread of the H5 strain across Australia. The virus was first detected in the country in migratory wild birds, but it has quickly jumped to native bird species, including giant petrels. In recent days, it has begun spreading to wild mammals, triggering growing concern among conservation and health officials about the risk to vulnerable native species including the iconic Tasmanian devil.

    This week, a dead red fox found in the Adelaide metropolitan area tested positive for H5 avian influenza, marking the first confirmed case of an infected mammal in an Australian urban center. On the heels of that discovery, South Australian authorities confirmed that a dolphin that washed ashore on Goolwa Beach is also suspected to have died from the virus. Dr Skye Fruean, the state’s chief veterinarian, noted that authorities are still investigating how the marine mammal contracted the virus, but the most likely pathway is interaction with or consumption of an infected wild bird.

    The cross-species jump of the virus has amplified existing concerns about the threat it poses to scavenging native Australian species, particularly the endangered Tasmanian devil, which regularly feeds on carrion that may include infected bird or animal carcasses.

  • A summer of foodborne illness is already testing Trump’s pick for top regulator

    A summer of foodborne illness is already testing Trump’s pick for top regulator

    A historic wave of foodborne illnesses across the United States this summer has thrown the future of the U.S. Food and Drug Administration into sharp relief, as former President Donald Trump’s nomination of White House insider and physician Heidi Overton to lead the agency faces growing scrutiny from lawmakers, public health experts, and even some administration allies. The nomination arrives at a moment of deep crisis for the FDA, which has been gutted by widespread staffing cuts, a mass exodus of senior leadership, and widespread public anger over a delayed, disjointed response to outbreaks that have sickened thousands of Americans.

    This summer’s outbreak season has been one of the worst on record. More than 17,000 confirmed cases of cyclospora, a parasite that causes severe persistent diarrhea, have been reported, a massive jump from just 1,180 cases during the same period last year. Most cases have been linked to contaminated iceberg lettuce produced by Taylor Farms, with infections recorded across nine states. Alongside the cyclospora surge, outbreaks of E. coli and salmonella have been traced to alfalfa sprouts, eggs, jalapeños, frozen blueberries, and multiple other common food products, leaving consumers confused and anxious about which foods are safe to eat.

    Public health experts and food safety advocates trace the slow, ineffective response to these outbreaks directly to years of staffing cuts and institutional disruption at the FDA. Current and former agency observers warn that years of underfunding was pushed to a breaking point last year, when Health and Human Services Secretary Robert F. Kennedy Jr. fired 20% of FDA employees as part of the Trump administration’s broader effort to downsize the federal civil service. The agency has also been without a permanent Senate-confirmed commissioner for nearly three and a half months, following the resignation of former head Marty Makary, who stepped down after a public clash with the White House over Trump’s plan to lift a ban on flavored vapes over concerns about youth addiction. Several senior agency leaders left shortly after Makary’s departure, leaving critical leadership posts vacant and agency morale at historic lows.

    “We’re already working with a system that was teetering on the edge, and last year’s cuts and upheaval have pushed it over the cliff,” explained Sarah Sorscher, food safety director at the non-profit Center for Science in the Public Interest. Jerold Mande, a former FDA and U.S. Department of Agriculture official and current nutrition professor at the Harvard T.H. Chan School of Public Health, noted that the CDC’s first public health alert for the cyclospora outbreak came 10 weeks after the first cases were detected in early May, a delay that left the public in the dark for months. “Poor communication has left people on edge and panicked about what they can eat,” Mande said.

    For many affected consumers, the frustration is deeply personal. David Hargrave, a 59-year-old Texas resident, has experienced daily diarrhea for a month and a half after contracting cyclospora over the Fourth of July holiday. “It scares you, not knowing what’s safe to eat anymore,” he said. Toby Davis, another person sickened by the parasite after eating at a Taco Bell that required an emergency room visit, blamed mass layoffs of veteran FDA experts for the slow response. “This is the consequence of careless mistakes,” said Davis, an independent voter. “Do I think more people will get sick because of their negligence? Absolutely.”

    Even some supporters of the administration’s health agenda have expressed caution. Jacqueline Capriotti, a supporter of the “Make America Healthy Again” (MAHA) movement founded by Kennedy, agreed that food safety must be the FDA’s top priority. “We tell people to eat real food, but we first have to guarantee that real food is safe to eat,” she said.

    Against this backdrop of crisis, Trump has tapped Overton, a former general surgery resident at Johns Hopkins University School of Medicine and chief policy officer at the conservative America First Policy Institute, to lead the agency. Trump has publicly praised Overton as a “rockstar” and a trusted ally who will advance his administration’s priorities. But public health experts worry that Overton, a long-time Trump insider, will prioritize loyalty to the president over evidence-based public health policy.

    John Swartzberg, professor emeritus of infectious diseases at the UC Berkeley School of Public Health, warned that Overton inherits an agency with shattered morale and a long list of unaddressed crises. “She’s stepping into an agency where morale is already rock bottom,” Swartzberg said. “Turning that around is going to be an enormous, incredibly difficult challenge.”

    Overton’s nomination also faces political headwinds. She must first win confirmation from the U.S. Senate, with no hearing date set yet. The Senate Health Committee, which will consider her nomination, is chaired by Republican Sen. Bill Cassidy, a physician who has already voiced “strong concerns” about Overton due to her support for Trump’s executive order to overhaul the childhood vaccine schedule. Even some members of the MAHA movement oppose her nomination over her reported role in a Trump executive order to expand domestic production of glyphosate, a weed killer that MAHA activists argue is carcinogenic. The White House has denied that Overton played any key role in drafting the order, but prominent MAHA influencer Alex Clark has publicly raised the accusation on social media. Still, Capriotti argues that critics are too quick to judge, saying “She’s a well-respected physician, and I think she deserves a chance to prove herself.”

    The Trump administration has pushed back against claims that staffing cuts and leadership turnover have hampered its outbreak response. A HHS spokesperson insisted that “the Trump Administration has mounted a robust response to each outbreak” and claimed that “FDA has the staff needed to continue investigating outbreaks, as no FDA investigators were affected by staffing changes or reductions in force.” White House spokesperson Kush Desai defended Overton’s qualifications in a statement to the BBC, saying she “has been integral to ensuring that the Administration’s policies are correct, consistent, and grounded in Gold Standard Science,” and adding that the White House “looks forward to her swift confirmation by the Senate.”

    The stakes of the confirmation fight extend far beyond food safety, as Overton would also oversee the FDA’s handling of other high-profile controversial policy priorities for the Trump administration, including vaccine regulation and access to abortion medication. For public health advocates and consumers still reeling from this summer’s outbreak wave, the confirmation will set the course for the agency that regulates 80% of the U.S. food supply at a moment of historic institutional instability.

  • Congo begins Ebola vaccinations to fight country’s worst outbreak on record, health minister says

    Congo begins Ebola vaccinations to fight country’s worst outbreak on record, health minister says

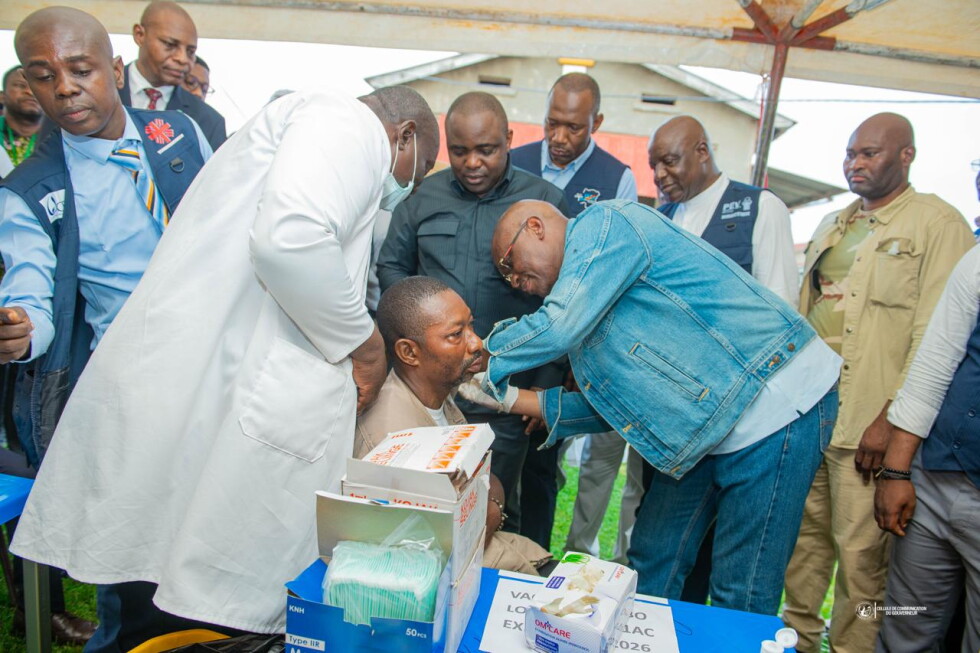
    KAMPALA, Democratic Republic of Congo – In a urgent, long-awaited step to curb the deadliest Ebola outbreak the nation has ever faced, Congolese health authorities officially launched a nationwide vaccination campaign on Thursday in the eastern provincial capital of Kisangani, Health Minister Roger Kamba announced.

    The campaign prioritizes high-risk groups first, with frontline health workers, response personnel and close contacts of confirmed Ebola patients topping the list of those to receive doses. Minister Kamba confirmed that the campaign will use the Ervebo vaccine, currently the only widely available Ebola vaccine authorized for emergency use. As of this week, government data puts the outbreak’s toll at 5,713 confirmed cases across six affected provinces – Ituri, North Kivu, South Kivu, Tshopo, Haut-Uele, and Bas-Uele – with 2,744 recorded deaths, translating to a 48% mortality rate among confirmed infections.

    This current outbreak, driven by the rarely-seen Bundibugyo Ebola variant, has spread rapidly against a backdrop of crippling systemic challenges: persistent regional insecurity, mass population displacement, a recent nationwide strike by health care workers, and unregulated cross-community population movements. The World Health Organization (WHO) has warned the outbreak remains fully out of control, and is on track to exceed the 2014-2016 West Africa Ebola epidemic – the previous global deadliest on record, which claimed more than 11,000 lives across Guinea, Liberia and Sierra Leone.

    To address the crisis, global health bodies have fast-tracked vaccine shipments to Congo. Congolese state media confirm the country has already received more than 50,000 doses of Ervebo, while the WHO approved a total of 70,000 doses for deployment in the outbreak response last week. Of the total approved doses, 50,000 are allocated to frontline and at-risk health workers, with the remaining 20,000 reserved for a clinical trial investigating Ervebo’s efficacy against the Bundibugyo variant.

    Crucially, Ervebo is only formally approved to protect against Zaire ebolavirus, a different strain of the virus, and no vaccine is yet specifically authorized for Bundibugyo Ebola. The rollout is proceeding under a compassionate use framework, which permits unapproved off-label use of medical products during public health emergencies when no targeted alternatives exist. Health officials note that the two Ebola strains are genetically related, leading experts to hypothesize Ervebo may offer partial cross-protection, though this hypothesis remains unconfirmed and is the subject of ongoing clinical investigation.

    Placide Mbala Kingebeni, director of research, clinical trials and innovation at the Africa Centers for Disease Control and Prevention (Africa CDC), confirmed that systematic efficacy data will be collected throughout the vaccination campaign to answer critical questions about Ervebo’s performance against Bundibugyo Ebola. The initial phase of the campaign will target 14 high-risk health zones across Tshopo, Bas-Uele, and Haut-Uele provinces, the three current hotspots of transmission.

    In his remarks launching the campaign, Kamba issued a strong call to action for all frontline health workers to accept vaccination, emphasizing that protecting care providers not only saves their lives, but also prevents secondary transmission of the virus from health settings into the broader community.

  • Jury deliberating in trial of Lindsay Clancy, US woman accused of killing her children

    Jury deliberating in trial of Lindsay Clancy, US woman accused of killing her children

    The high-stakes trial of Lindsay Clancy, a Massachusetts mother charged with murdering her three young children, has drawn national attention as closing arguments conclude and jury deliberations begin. Clancy, who does not deny killing her two sons and daughter aged between eight months and five years, faces a potential life sentence without parole if convicted of first-degree murder, the most severe charge in the case.

    The core controversy of the trial hinges on one critical question: was Clancy in the grips of postpartum psychosis, a severe and acute perinatal mental health emergency, when she committed the fatal acts in January 2022? Her legal team has spent five weeks arguing that the rare mental health condition stripped her of the ability to understand or control her actions, making her not legally responsible for the deaths. After killing the children with exercise bands at the family home, Clancy attempted suicide by jumping from a window, an injury that left her paralyzed; she has attended all trial proceedings in a wheelchair. In his closing argument, lead defense attorney Kevin Reddington reiterated that Clancy was suffering from a severe mental illness that drove her actions, telling jurors, “This young lady is not guilty of the killing of her children because she was suffering from a disease and defect.” Reddington also pressed back against prosecution claims that Clancy’s suicide attempt was not genuine, a moment of tension that led the judge to interrupt and order him to direct all comments to the jury.

    Prosecutors do not dispute that Clancy lives with mental illness, but they reject the defense’s insanity claim. Lead prosecutor Jennifer Sprague argued to the jury that Clancy was capable of distinguishing right from wrong at the time of the killings, framing the deaths as a calculated, premeditated act. Sprague also noted that the Diagnostic and Statistical Manual of Mental Disorders (DSM), the standard reference for mental health diagnoses in the U.S., does not formally recognize postpartum psychosis as an independent diagnosis. She added that Clancy had access to extensive medical care, but deliberately hid her harmful thoughts about her children from treating clinicians.

    Defined by the UK’s National Health Service as a rare, life-threatening mental health emergency that develops shortly after childbirth, postpartum psychosis has never before received this level of national public scrutiny in a U.S. criminal trial. As the jury weighs its verdict, it faces a range of possible outcomes: a first-degree murder conviction with a mandatory sentence of life in prison without parole, a conviction on lesser charges including second-degree murder or involuntary manslaughter that would still carry significant prison time, or a verdict of not guilty by reason of insanity. Contrary to common public misunderstanding, a verdict of not guilty by reason of insanity would not result in Clancy’s immediate release; instead, she would be committed to a state psychiatric facility, potentially for the rest of her life.

    This case includes distressing details of harm to children and attempted suicide. For anyone experiencing suicidal thoughts or perinatal mental health distress, support is available globally through Befrienders Worldwide at www.befrienders.org, and for people in the UK, additional resources are listed at bbc.co.uk/actionline.