分类: health

  • Fact-checking Trump’s claims as he rolls back some recommended vaccines

    Fact-checking Trump’s claims as he rolls back some recommended vaccines

    On Monday, former U.S. President Donald Trump signed an executive order in the Oval Office that alters the national recommended childhood vaccine schedule, cutting the number of vaccine-preventable diseases covered from 18 to 11 and recommending that the combined mumps, measles and rubella (MMR) vaccine be split into separate individual doses. However, during the signing ceremony, Trump made a series of misleading and outright false statements about childhood vaccinations that have been widely refuted by public health experts and leading federal health agencies.

    One of Trump’s most high-profile false claims was that federal policy required young children to receive as many as 72 vaccine doses. White House Press Secretary Karoline Leavitt amplified this claim after the announcement by sharing a graphic showing an infant surrounded by needles labeled “72 injections”. Fact-checkers quickly confirmed that this framing is deeply inaccurate on multiple counts. First, while federal vaccine guidance influences policies across the country, requirements for school entry are set individually by U.S. states, meaning the total number of doses administered to children varies by location. Second, the 72-dose count cited by the White House tallies every potential vaccine dose a person could receive between birth and age 18, including annual influenza shots and routine COVID-19 boosters — not doses given only to young children or infants.

    Trump also made a false claim about the volume of vaccine doses administered, stating that a single MMR shot contains an amount of liquid comparable to an entire bottle of soda. According to U.S. Food and Drug Administration (FDA) data, a standard single dose of MMR is just 0.5 milliliters, which equals a tiny fraction of a single teaspoon. Josh Michaud, associate director of the Global and Public Health Policy Program at the Kaiser Family Foundation (KFF), confirmed that even the combined total volume of all vaccines recommended for childhood is nowhere close to the volume of a bottle of soda, and is dramatically smaller than Trump’s description.

    When arguing for splitting the combined MMR vaccine into three separate doses, Trump claimed that combining the three vaccines into a single shot “could be a possibility they’re quite lethal”. This claim directly contradicts decades of public health data collected by the U.S. Centers for Disease Control and Prevention (CDC). The CDC confirms that the vast majority of people who receive the combined MMR vaccine experience no serious adverse reactions. Getting vaccinated against the three diseases is also far safer than contracting measles, mumps, or rubella, all of which can cause severe long-term illness and even death. The most serious potential side effects of MMR vaccination are febrile seizures and severe allergic reactions, both of which the CDC classifies as extremely rare; only one in 3,000 to 4,000 vaccinated children experience a febrile seizure after vaccination.

    Finally, Trump repeated the long-debunked claim that vaccines are linked to rising autism diagnosis rates, claiming that autism rates have grown in lockstep with expanded vaccine schedules and citing a wildly inaccurate historical rate of one case per 10,000 people 20 years prior. While autism diagnosis rates in the U.S. have indeed risen over the past two decades, the growth has not matched Trump’s claims: the CDC estimated a rate of one in 110 children in 2006, which rose to one in 88 just two years later. Leading public health experts overwhelmingly agree that rising diagnosis rates are explained by broader changes to diagnostic criteria, increased public awareness of autism, and expanded access to screening, not any change in vaccine schedules.

    Decades of large-scale peer-reviewed studies have found no causal link between vaccination and autism. Most recently, a comprehensive 2025 review conducted by the World Health Organization (WHO) analyzed data from dozens of independent studies covering millions of children across multiple countries, and formally concluded there is no causal connection between vaccination and autism. Experts explain that the false public perception of a link stems from a coincidental timeline: routine childhood vaccinations are primarily administered between birth and age five, which is also the age window when autism is most commonly diagnosed. This overlap creates a misleading correlation that is often misinterpreted as causation.

    In its 2025 report, the WHO noted that unsubstantiated claims about theoretical vaccine risks have fueled ongoing public controversy, particularly at a time when widespread misinformation and disinformation online has driven growing rates of vaccine hesitancy across much of the world.


  • NSW government promises 2300 more surgeries by mid-2027 amid winter hospital surge

    NSW government promises 2300 more surgeries by mid-2027 amid winter hospital surge

    As New South Wales (NSW) braces for what state leaders call the most challenging three weeks of the winter respiratory season, the Australian state government is moving aggressively to clear a years-long backlog of delayed elective procedures by expanding a specialized, high-efficiency surgical model across public hospitals.

    Launched in late 2025 with a AUD 30 million state investment, High Volume Short Stay (HVSS) units are dedicated hospital wings designed exclusively to handle low-complexity, same or short-day surgeries. Under the new expansion plan, these specialized units will deliver an additional 2,300 routine procedures over the coming 12 months, with the full capacity target expected to be met by July 1, 2027, according to projections from NSW Health.

    State Health Minister Ryan Park explained that the HVSS model is a core pillar of the current government’s pledge to eliminate the state’s long-delayed surgery waitlist, which swelled to a peak of more than 18,000 under the previous state administration. As of March 2026, government data shows the backlog has already been cut to roughly 4,000 cases, marking significant progress in clearing the backlog left by the prior government.

    “We are investing in surgery services across the state, expanding access to care, cutting wait times, and improving patient outcomes,” Park said in a press statement. “These high volume surgical programs are exactly the kind of innovative care we want to see, and I’m looking forward to seeing this model expanded across NSW.”

    The procedures handled by HVSS units cover 80 percent of all routine surgeries performed across NSW’s public health system, spanning common, low-risk procedures across ear, nose and throat care, general surgery, gynecology, urology, ophthalmology, and orthopedics. Currently, the units operate at five strategic locations: Campbelltown in outer western Sydney, Shellharbour, Wagga Wagga, Western NSW, and the Mid North Coast, bringing expanded care access to both metropolitan and regional communities.

    The expansion comes as NSW’s public hospital system grapples with an unprecedented winter surge in patient demand. Last week, Premier Chris Minns issued a public warning that emergency departments across the state were preparing for the “worst three weeks of the year”, urging patients with non-life-threatening conditions to seek care from alternative providers to ease pressure on overstretched emergency teams.

    “To the extent that you can go to an urgent care clinic or see your GP … if it’s not life-threatening, we genuinely suggest that you do that so the doctors can focus and nurses can focus their efforts and attention on people that are about to die,” Minns said.

    The scale of the surge already being felt was underscored by new data: Park confirmed that just under 10,000 patients presented to Sydney emergency departments on Monday, breaking the record for the busiest winter day on record. The state also recorded roughly 4,100 ambulance call-outs on the same day, pushing emergency response systems close to capacity.

    Beyond the seasonal surge, Park has repeated calls for the federal government to intervene to resolve the ongoing “bed block” crisis, which sees hundreds of aged care patients stranded in public hospital beds while waiting for commonwealth-funded aged care support packages. In June, state data showed the number of these so-called stranded patients had jumped to nearly 1,300, further reducing available capacity for acute and emergency care across the state.

  • Congo says 2,000 people have died in its Ebola outbreak, the fastest growing on record

    Congo says 2,000 people have died in its Ebola outbreak, the fastest growing on record

    In the eastern Democratic Republic of Congo, a rapidly spreading Ebola outbreak that has already become the fastest-growing in recorded history has crossed a devastating mortality threshold, with latest official government data confirming at least 2,000 fatalities among confirmed cases. The grim milestone comes as international and local health response teams face overlapping barriers that slow urgent care delivery to remote, conflict-affected communities, leaving the virus far outpacing containment efforts.

    Data released publicly overnight ahead of Tuesday puts the total cumulative confirmed cases at 4,381, with the death toll reaching 2,011. As of the latest update, 704 patients remain isolated and under care for the virus. The scale of the outbreak’s spread has alarmed global health experts: just under three months have passed since the Congolese government officially declared the outbreak on May 15, but the acceleration of deaths shows an alarming upward trajectory. It took nine weeks to record the first 1,000 fatalities, yet only three additional weeks to push the death toll to 2,000, a pace that responders have struggled to match.

    Already, this outbreak ranks as the second-largest Ebola event in global history. It is only surpassed by the 2014-2016 West African epidemic, which infected more than 28,000 people and killed over 11,000 across Guinea, Liberia and Sierra Leone. For the Democratic Republic of Congo, this is the 17th Ebola outbreak the country has confronted since the virus was first identified in 1976 near the Ebola River within the nation’s borders, and it is already the largest the country has ever faced.

    Multiple overlapping crises have undermined containment efforts, according to response officials and aid workers. Active rebel conflict in affected regions makes access to remote communities dangerous at best, while poorly maintained infrastructure leaves many affected areas cut off from rapid medical support. Compounding these issues, hundreds of frontline health workers have launched work stoppages to protest delayed and missing hazard pay promised when the outbreak was declared.

    Adding to the complexity of the response, this outbreak is caused by the rare Bundibugyo Ebola strain, for which no specific approved vaccines or targeted treatments currently exist. Early-stage clinical trials for candidate vaccines and therapies have been launched in Ituri province, the geographic epicenter of the outbreak, but regulatory and logistical delays mean widespread access to these tools remains months away.

    The World Health Organization revealed new findings on Monday that show the outbreak was circulating undetected far earlier than official detection. WHO officials confirmed the virus likely began spreading in February, three months before the formal declaration, in one of Congo’s most underserved and remote regions. Early cases were misdiagnosed as malaria or typhoid, and initial testing only screened for the more common Zaire strain of Ebola, allowing the virus to establish unmonitored transmission in local communities. Today, most new confirmed cases are found among people not already on contact tracing lists, a clear sign that community transmission remains widespread.

    Speaking at a press briefing, Dr. Mohamed Yakub Janabi, WHO’s Regional Director for Africa, summed up the ongoing challenge facing responders: “We are chasing the virus, and the virus is ahead of us.” Aid groups that have expanded response operations across the five affected provinces acknowledge that the outbreak continues to outpace the incremental growth of containment efforts, leaving global health authorities bracing for further increases in case counts and deaths in the coming weeks.

  • Trump order pushes for overhaul of childhood vaccine schedule

    Trump order pushes for overhaul of childhood vaccine schedule

    On a Monday afternoon in the Oval Office, U.S. President Donald Trump signed an executive order calling for a sweeping review of childhood vaccine mandates for K-12 schools, doubling down on a long-debunked call to split the combined measles, mumps, and rubella (MMR) vaccine into three separate single-disease shots. The signing ceremony was attended by Health and Human Services Secretary Robert F. Kennedy Jr., a longstanding anti-vaccine advocate who built his public profile around spreading false claims of a link between childhood immunization and autism, a claim that has been thoroughly disproven by decades of peer-reviewed clinical research.

    Critics across the medical and public health communities have quickly decried the order as scientifically unfounded and a direct threat to decades of successful public health progress. The policy push also faces immediate structural limitations: the federal government holds no direct authority over school vaccine requirements, which are set independently by individual U.S. states and territories. As outlined in the text of the order itself, the Trump administration can only advise state and local governments to revisit their existing immunization rules for school enrollment, making the measure largely symbolic rather than immediately enforceable.

    The order does include one actionable provision: it directs the Department of Health and Human Services to convene a new interagency task force to work with private pharmaceutical manufacturers and international partners to develop and approve separate MMR vaccines, while retaining the existing combined shot as an option. Even if the task force moves forward immediately, leading pediatric health experts warn that full regulatory approval and widespread distribution of separate shots would take more than a decade to complete.

    “This entire order is rooted in politics and conspiracy theories, not evidence-based public health,” Alister Martin, New York City’s Health Commissioner, said in a public statement following the signing. “Vaccination recommendations should not be set by the president, and thankfully, they are not. Cities and states retain authority to set their own rules, and here in New York City, we will continue to follow science-based guidance, not politically motivated misinformation.”

    Decades of large-scale clinical trials and population-level data consistently confirm that the combined MMR vaccine is safe for children. Public health experts note that the combined formulation delivers faster, broader protection against three dangerous contagious diseases, while also reducing logistical burdens for families who may face barriers to scheduling multiple doctor’s appointments for separate shots. Despite this overwhelming consensus, President Trump used the signing ceremony to repeat a series of inflammatory, unsubstantiated claims contradicting established medical guidance.

    Leading national medical organizations have uniformly rejected the administration’s proposals. Andrew Racine, president of the American Academy of Pediatrics (AAP), emphasized that the development process for separate MMR vaccines would take more than 10 years to complete under the best of circumstances. “We are advising all pediatric providers and parents to continue following the existing schedule, which uses a vaccine that has 70 years of proven safety data behind it,” added Aaron M. Milstone, a member of the AAP Committee on Infectious Diseases.

    Even some members of the president’s own party have publicly denounced the move. Senator Bill Cassidy, a physician whose decisive vote confirmed Kennedy’s controversial appointment as Health Secretary, posted to social media platform X that the order would only worsen existing vaccine hesitancy and put American children at greater risk of preventable disease. “This executive order is wrong,” Cassidy wrote. “The President does not have the medical expertise to make these changes. Vaccines are overwhelmingly safe. Vaccines are effective. Vaccines DO NOT cause autism.”

    The latest policy push comes as the Trump administration already saw a prior attempt to overhaul federal vaccine policy blocked by a federal court earlier this year, after major medical organizations successfully argued the administration’s actions violated federal law. A judge issued a stay on the changes pending ongoing legal proceedings.

    Monday’s order arrives at a critical moment: as children across the United States prepare to return to in-person schooling for the new academic year, the country is currently grappling with the worst measles outbreak it has seen in 35 years. Public health officials widely blame rising vaccine hesitancy, fueled in large part by anti-vaccine misinformation spread by Kennedy and other allies of the president, for the resurgence of the once-eliminated disease.

    Recent polling shows a majority of American voters support evidence-based childhood vaccination requirements, and both Kennedy and Trump had softened their anti-vaccine rhetoric in recent months amid fears that hardline anti-vaccine positions would hurt Republican candidates in the upcoming November midterm elections. Monday’s signing makes clear that rolling back existing vaccine policy and advancing anti-vaccine misinformation remains a core priority of the administration’s public health agenda, as both men continue to endorse the thoroughly debunked claim that immunization causes autism.

  • Trump signs order to limit childhood vaccines and limit MMR shots

    Trump signs order to limit childhood vaccines and limit MMR shots

    In a controversial move announced from the Oval Office on Monday, former President Donald Trump signed an executive order that mandates a rollback of recommended childhood vaccines and calls for splitting the combined mumps, measles, and rubella (MMR) vaccine into separate single-disease doses.

    During his remarks, Trump repeated a long-debunked claim that the modern expanded childhood vaccine schedule has driven declining public health and rising autism rates in the United States. “Decades ago, children received only a small fraction of the vaccines required today,” Trump argued. “In those times, people were much healthier and of course the high rates of autism now observed did not exist.”

    The Trump administration has a well-documented history of promoting the discredited conspiracy theory that the MMR vaccine is connected to autism diagnoses. Decades of peer-reviewed, large-scale scientific studies conducted by global public health institutions have consistently found no causal relationship between any childhood vaccine and autism.

    Under the terms of the new order, the administration would set a new “gold standard” recommendation of only 11 core vaccines for the most high-risk infectious diseases: measles, mumps, rubella, diphtheria, tetanus, pertussis, polio, Haemophilus influenzae type B, pneumococcal disease, human papillomavirus, and varicella (chicken pox). Beyond cutting the total number of recommended vaccines, the order also proposes spreading remaining doses across multiple separate doctor visits, rather than combining doses during routine check-ups.

    Critics have quickly pointed out a major legal barrier to the policy’s implementation: the U.S. federal government lacks the authority to set vaccine requirements for school attendance, a power that is exclusively reserved for individual U.S. states. Long-time vaccine skeptic Robert F. Kennedy Jr., who has been closely aligned with Trump on this issue, has been a prominent advocate for rolling back childhood vaccine recommendations in recent years. Public health experts warn that reduced vaccination rates and splits to combined vaccines like the MMR would increase the risk of deadly preventable disease outbreaks across the country.

  • We are chasing Ebola virus – it is ahead of us, WHO warns

    We are chasing Ebola virus – it is ahead of us, WHO warns

    The World Health Organization has issued a stark warning that the ongoing Ebola outbreak in the eastern Democratic Republic of the Congo (DRC) began circulating at least three months before it was formally announced by public health officials, leaving response teams struggling to contain a pathogen that has already outpaced containment efforts.

    As of the latest official update from DRC’s Ministry of Health, the outbreak has recorded 4,294 confirmed infections and 1,960 fatalities, making it the second deadliest Ebola outbreak in recorded history. Only the 2014–2016 West African outbreak, which claimed more than 11,000 lives, has had a higher death toll.

    This outbreak is caused by the Bundibugyo strain of Ebola, a variant for which no universally approved vaccine or proven therapeutic treatments currently exist, creating additional barriers for clinical care. Persistent insecurity in the eastern region, the epicenter of the outbreak, has further undermined response work: WHO Africa director Dr Mohamed Janabi told reporters during a press briefing in Bunia, the outbreak’s core hub, that persistent conflict and instability have left response teams only able to reach roughly 30 percent of confirmed cases. The remaining patients are unable to access care and die in their homes.

    New genomic and epidemiological research traces the first community transmission of the virus back to February 2025, months before the outbreak was officially declared on May 15. In those early months, infections were consistently misdiagnosed as more common febrile illnesses including malaria and typhoid, allowing the virus to spread undetected through local communities. Two additional cultural and trust barriers have complicated containment efforts: traditional burial customs that require close physical contact with deceased bodies, a major transmission route for Ebola, and widespread community suspicion of external health authorities have both slowed intervention work.

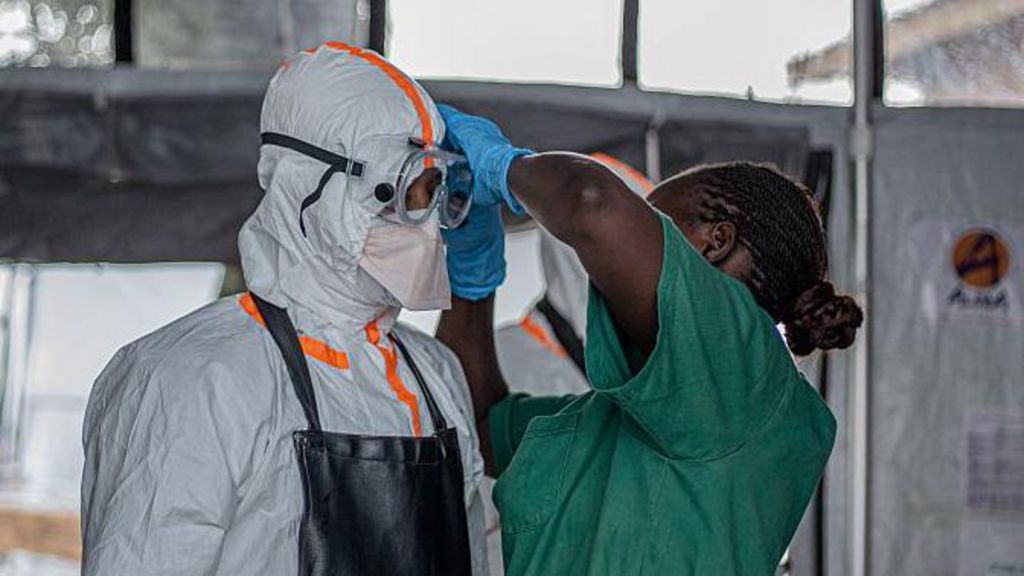
    Ebola spreads through direct contact with infected bodily fluids, meaning frontline health workers require full personal protective equipment to safely treat patients and conduct containment work. Despite the significant challenges, response officials have noted modest progress: several purpose-built Ebola treatment centers have now been established in eastern DRC, and diagnostic testing capacity has expanded sharply, cutting wait times for confirmatory results.

    Dr Janabi summed up the current state of the response in blunt terms: “We are chasing the virus, the virus is ahead of us.”

  • Taylor Farms recalls jalapeno products after salmonella outbreak

    Taylor Farms recalls jalapeno products after salmonella outbreak

    One of the United States’ largest fresh produce suppliers, Taylor Farms — a company that confirms it accounted for 40% of all salad kits sold across the U.S. in 2025 — has launched a second major product recall in weeks, this time pulling dozens of jalapeño-containing items from store shelves over confirmed salmonella contamination risks.

    The recall covers roughly 20 fresh products, ranging from pre-made sandwiches, dips, and salsa to pre-sliced jalapeños and prepared burritos, distributed to major national retail chains including Walmart, Target, and Whole Foods across 26 U.S. states. Company representatives emphasized that as of the announcement, no illnesses connected to the potentially contaminated jalapeño products have been reported, but the proactive withdrawal was launched after supplier Coast Citrus Distributors issued its own recall of the peppers over salmonella concerns.

    Investigators have traced the contaminated jalapeños back to a single grower based in Sinaloa, Mexico. In a public statement, Taylor Farms confirmed it has immediately cut ties with the farm and shifted all jalapeño sourcing to alternative approved suppliers. The company has issued clear guidance for consumers: anyone holding recalled products should discard the items immediately, and full refunds are available at the original point of purchase.

    According to the U.S. Food and Drug Administration (FDA), salmonella infection typically develops between 12 and 72 hours after consuming contaminated food, with common symptoms including diarrhea, abdominal cramping, and fever. Most cases resolve on their own, but vulnerable groups including young children, elderly people, and immunocompromised individuals can develop severe complications that require hospitalization.

    This recall marks the second high-profile food safety scare for Taylor Farms in less than a month. The company is already at the center of a large-scale cyclospora outbreak linked to its Mexican-grown iceberg lettuce, which has emerged as one of the most widespread foodborne illness events in recent U.S. history. As of an August 4 update from the U.S. Centers for Disease Control and Prevention (CDC), more than 22,000 people have fallen ill from cyclosporiasis linked to the outbreak across 45 U.S. states, and Michigan health officials confirmed the first two fatalities linked to the parasite outbreak last week.

    Cyclospora is a microscopic parasite that causes severe gastrointestinal illness, most commonly explosive diarrhea and prolonged abdominal discomfort. The outbreak has even drawn international attention: UK public health officials have issued warnings for travelers returning from the U.S. who may have consumed Taylor Farms lettuce, after reporting several imported cases among recent visitors.

    Headquartered in California, Taylor Farms is a cornerstone of the North American fresh food supply chain, supplying not only major retail grocers but also leading fast-food chains including McDonald’s and Taco Bell, with a workforce of more than 25,000 employees across its operations. The back-to-back outbreaks have renewed scrutiny of food safety protocols for imported fresh produce from Mexico, which supplies a large share of U.S. fresh fruits and vegetables year-round.

  • WHO says Congo’s fast-moving Ebola outbreak started months before it was declared

    WHO says Congo’s fast-moving Ebola outbreak started months before it was declared

    In a stark update on the spiraling public health crisis in eastern Democratic Republic of the Congo, the World Health Organization (WHO) confirmed Monday that the fastest-growing Ebola outbreak in recorded history emerged in February, three full months before it was officially declared to the public on May 15. Responders are now scrambling to contain a virus that has consistently outpaced containment efforts, against a backdrop of systemic and security challenges that make effective intervention nearly impossible.

    Dr. Mohamed Yakub Janabi, WHO’s Regional Director for Africa, told reporters that genetic sequencing of virus samples has traced the outbreak’s origin back to February. Early cases of the disease were misdiagnosed as malaria and typhoid, a critical error that allowed the virus to spread undetected through communities for months. Compounding this early delay, initial testing protocols only screened for the more common Zaire strain of Ebola, not the rare Bundibugyo variant driving this outbreak. The Bundibugyo strain has no approved vaccines or targeted treatments currently available, leaving frontline workers with limited tools to slow transmission or improve patient outcomes.

    As of the latest official government count, the outbreak has already recorded 4,200 confirmed cases, with more than 1,900 people dead. This current outbreak has killed people faster than any Ebola event in history, outpacing even the devastating 2014-2016 West Africa outbreak that was long considered the worst on record. That 2014-2016 crisis took eight months to reach 1,000 deaths; this outbreak hit that milestone in a fraction of the time.

    The crisis is unfolding in one of the most difficult operating environments for global health responders. The affected region, which sits near the borders of South Sudan, Uganda, and Rwanda, has been torn apart by decades of rebel conflict that gutted local healthcare infrastructure long before the first Ebola case emerged. Today, responders face multiple overlapping barriers: strikes by unpaid health workers have left critical facilities understaffed, rebel groups threaten aid teams, and long-traumatized communities often distrust intervention efforts, fueled by widespread misinformation that claims Ebola does not exist at all.

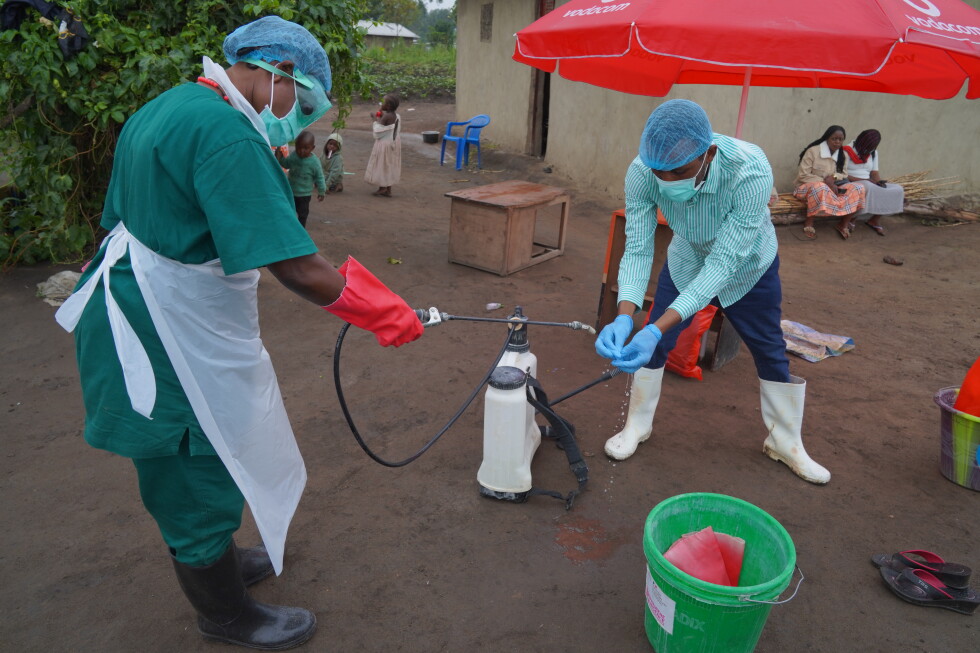
    Frontline teams must navigate remote, unpaved roads to reach affected communities and have repeatedly reported critical shortages of personal protective equipment. A large population of displaced people living in informal settlements also lack access to clean water for regular handwashing, one of the most basic measures to slow transmission of the virus, which spreads through contact with infected bodily fluids including blood, vomit, and semen, as well as contaminated surfaces like bedding and clothing. Ebola causes severe organ damage and is fatal in the majority of untreated cases.

    Last week, WHO Director-General Tedros Adhanom Ghebreyesus reiterated the urgency of the crisis during a visit to Congolese capital Kinshasa, noting that the virus is spreading faster than response teams can keep up. In some of the worst-affected hot spots, the number of new confirmed cases is doubling at an alarming rate. Health authorities estimate that between 60% and 70% of all new cases are occurring in people who were not on the contact tracing monitoring list, meaning transmission is happening through unrecognized community spread that is nearly impossible to track.

    Already fragile access to routine healthcare in the region has become even worse as the outbreak escalates. Pregnant women and people with other acute medical conditions are now avoiding health centers out of fear of contracting Ebola, putting their own lives at unnecessary risk from treatable conditions.

    Late declarations of Ebola outbreaks are not unprecedented. The 2014-2016 West Africa outbreak, which killed more than 11,000 people across at least 28,000 confirmed cases, was officially declared in March 2014, but retrospective investigation later found the first human infection occurred three months earlier, in December 2013.

  • Men aged 50-69 to test every two years for prostate cancer in massive reform

    Men aged 50-69 to test every two years for prostate cancer in massive reform

    Australia has introduced landmark, world-first updates to its national clinical guidelines for prostate cancer early detection, marking the first major overhaul of the framework in 10 years. Unveiled by the Albanese government this Thursday, the revised 2026 Clinical Guidelines for the Early Detection of Prostate Cancer expand access to routine Prostate-Specific Antigen (PSA) testing, with the dual goal of catching aggressive cases earlier and cutting harm from unnecessary overdiagnosis and overtreatment.

    Developed in partnership between the Prostate Cancer Foundation of Australia and Cancer Council Australia, the new testing framework expands eligibility to multiple at-risk groups. Under the reforms, all Australian men between 50 and 69 years old will now qualify for biennial PSA screening. Men aged 45 to 49 will be able to complete an initial baseline test, while high-risk groups — including those with a first-degree family history of prostate cancer, carriers of a BRCA2 gene mutation, and men of sub-Saharan African ancestry — can access biennial testing starting as early as age 45.

    Jeff Dunn AO, head of research at the Prostate Cancer Foundation Australia, described the updated guidelines as a watershed moment for Australia’s approach to managing the disease, noting the country is among the first in the world to adopt this modern, evidence-based structure. “These guidelines represent the culmination of years of scientific work, national collaboration, and rigorous evaluation of the evidence,” Dunn explained. “Much has changed over the past decade. The evidence has matured, diagnostic technologies have advanced, and clinical practice has evolved substantially. For the first time, Australia now has a contemporary national framework that better balances the benefits of detecting aggressive prostate cancer early with the need to minimise unnecessary harms.”

    Australian Health Minister Mark Butler emphasized that the policy reform is designed to ensure that at-risk men and their families can access targeted support at the earliest possible stage. Dan Repacholi, Labor Member of Parliament and the federal government’s special envoy for men’s health, who has long been a leading advocate for improved prostate cancer care, reaffirmed the government’s commitment to advancing detection and treatment outcomes.

    “As the most commonly diagnosed cancer in Australia, prostate cancer has significant impacts on men, their families and the wider community,” Repacholi said, urging men aged 45 and over to consult their general practitioner about their individual risk and whether screening is appropriate for them.

    Prostate cancer currently holds the title of Australia’s most frequently diagnosed cancer, with roughly 28,000 new cases recorded each year and approximately 4,000 annual deaths from the disease. To support rollout of the new guidelines, the federal government has allocated $320,000 in funding to the Royal Australian College of General Practitioners, which will develop and deliver targeted education and awareness training for frontline primary care providers. Since GPs serve as the first point of contact for most men seeking cancer screening, the training program is expected to smooth implementation and improve guideline adherence across the country.

  • One man works to slow the fastest-growing Ebola outbreak in history, and he’s doing it unpaid

    One man works to slow the fastest-growing Ebola outbreak in history, and he’s doing it unpaid

    In the conflict-scarred, remote heart of eastern Democratic Republic of the Congo’s Ituri province, the epicenter of the country’s surging Ebola outbreak, 29-year-old infection control specialist Wiza Bondele reports for duty every day. His mission is unwavering: slow the spread of the fastest-growing Ebola outbreak ever recorded. But since the outbreak was declared in mid-May, he has worked without pay, joining hundreds of other frontline responders from burial teams to ambulance drivers who put their lives on the line every day with no financial compensation.

    Bondele, a veteran of the 2018-2020 Congo Ebola response, volunteered to return to duty when the Bundibugyo strain of Ebola reemerged earlier this year. Ituri province accounts for nearly 90% of all confirmed cases in this current outbreak, and his years of experience on the frontlines made him a critical asset to the response. Today, his daily routine includes decontaminating high-risk treatment areas, screening visitors for fever, and enforcing mandatory handwashing protocols—work that brings him into regular contact with patients who are bleeding or vomiting, the bodily fluids that transmit the deadly virus. Even with this constant exposure, he and hundreds of fellow workers have yet to receive the $510 monthly salary they were promised when they signed on.

    While authorities have promised to resolve backlogged payments via mobile money transfers, only a small fraction of workers have received any compensation, and even those who were paid have not received their full wages. For Bondele, who supports his wife, child, and extended family, the financial strain has reached a breaking point. On one recent morning, he ran out of fuel for his motorcycle while commuting to work. With no cash to refill the tank, he left the bike with neighbors and walked the remaining 8 miles to the hospital, arriving with his shoes completely worn through.

    Latest government data puts this outbreak at more than 4,000 confirmed cases, with over 1,800 deaths recorded. This makes it the second-largest Ebola outbreak in recorded history, outpaced only by the 2014-2016 West Africa outbreak that killed more than 11,000 people, and deadlier than the 2018-2020 Congo outbreak that claimed at least 2,200 lives. Complicating the response further, the outbreak is caused by the Bundibugyo virus, for which no approved vaccines or targeted treatments currently exist.

    In recent weeks, hundreds of unpaid workers including Bondele have joined strikes and protests to demand back pay, at times abandoning treatment facilities and leaving critical response gaps as the virus continues to spread faster than responders can track it. Workers warn that months of unpaid wages have crushed morale and directly undermined patient care, with one treatment center’s staff announcing they would remain on strike until concrete solutions to the pay crisis were implemented. Government Ebola response officials have acknowledged the issue, blaming logistical delays for the backlog and stating they expect to clear all outstanding payments soon after switching from cash to mobile money disbursements. But for Bondele, these promises have done little to ease his anxiety over his and his family’s future.

    The pay crisis comes at a time when the Ebola response is already battling multiple overlapping challenges. Ituri province is gripped by ongoing armed conflict, and widespread misinformation has fueled deep public mistrust of health workers. Bondele says he has been threatened and even beaten while conducting community awareness outreach, as many residents reject basic prevention measures like regular handwashing. Restrictions on traditional burials, which require avoiding contact with highly contagious deceased patients, have stoked resentment, while persistent false rumors claim the outbreak is a hoax, that health workers are profiting from the crisis, or that hospitals withhold treatment from infected patients.

    This misinformation has repeatedly turned violent: crowds have burned down treatment centers, stormed hospitals to retrieve the bodies of deceased relatives, and attacked teams conducting safe burials. Public mistrust has also made contact tracing—one of the most critical tools for stopping Ebola spread—far more difficult, especially in remote communities already destabilized by rebel violence.

    Even with all these hardships, Bondele and hundreds of his colleagues continue to show up for work seven days a week, convinced their work is too important to abandon. “Working this job takes a lot of courage,” he said. “But today, I am discouraged.” He still holds out hope that authorities will follow through on their promises to pay workers what they are owed: “I hope their conscience tells them that I deserve to be paid.”

    This reporting was supported by the Gates Foundation, with The Associated Press retaining full editorial control over all content. Banchereau contributed reporting from Dakar, Senegal.