分类: health

  • Aged care program for 830,000 Australians to be extended

    Aged care program for 830,000 Australians to be extended

    After weeks of uncertainty over its future that threatened continuity of care for hundreds of thousands of older Australians, the Albanese federal government has confirmed it will extend the Commonwealth Home Support Program (CHSP) through June 2029, and will keep the program separate from the broader Support At Home initiative long-term. The announcement was made jointly Thursday by federal Health Minister Mark Butler and Aged Care Minister Sam Rae, bringing much-needed clarity to service providers and the 830,000 senior Australians who rely on the CHSP for daily living support.

    The CHSP is a subsidized, government-contracted service that caters to seniors who need partial assistance to remain living independently in their own homes. It covers essential daily support ranging from domestic cleaning and grocery shopping to medical transport and community social connection activities. Senator Rae emphasized that for most seniors beginning their journey into aged care support, the CHSP acts as a critical first entry point into the national aged care system.

    “Providers told us they needed certainty. And, importantly, all the people told us that they needed continuity of care,” Senator Rae said of the decision to extend funding and lock in the program’s independent status beyond 2029. Prior to the announcement, widespread uncertainty about a potential full merger into the Support At Home program had pushed a number of providers – including multiple local councils across the country – to begin withdrawing from the CHSP. Around 1,300 providers currently deliver CHSP services across Australia, with nearly 40 percent of program clients residing in regional and rural areas outside major metropolitan centers.

    The federal government plans to open a new round of public and sector consultation during the extended funding period to refine the CHSP’s long-term operating framework, following confirmation it will remain separate from Support At Home. Industry peak body Ageing Australia quickly welcomed the announcement, with chief executive Tom Symondson noting that the removal of uncertainty would prevent widespread service closures and cuts that many providers had already begun planning for.

    “Without it, many have been forced to consider closure or service reductions. I hope that much of that can be avoided with today’s announcement,” Symondson said. He added that the extension period must be used to address longstanding flaws in the program, including outdated contracts and insufficient funding levels that have left many communities without adequate support. “It’s critical that we use this time to look at existing contracts and make sure they’re sufficient to provide the support needed for local communities. Many are outdated with woefully inadequate funding to deliver for the needs of the community, which must be urgently addressed,” he said.

    Alongside the CHSP extension announcement, Senator Rae also defended the federal government’s controversial integrated assessment tool, an algorithm-driven decision-making system that has faced crossbench opposition and passed a disapproval motion in the Senate in recent months. Rae argued that the tool, which has been added to the national aged care assessment system, delivers more equitable and efficient assessment outcomes, and has successfully reduced wait times and improved accuracy for applicants. The government has since introduced reforms to give seniors the right to appeal algorithm-generated decisions to a human reviewer, and Rae acknowledged further improvements can be made to the prioritization process.

    While Rae noted that the broader single assessment system that includes the tool was a formal recommendation of the aged care royal commission, he confirmed the algorithmic tool itself was never explicitly recommended by the royal commission inquiry.


  • ‘Breakthrough’ mRNA cancer drug curbs melanoma in large trial

    ‘Breakthrough’ mRNA cancer drug curbs melanoma in large trial

    In a transformative development for cancer care, pharmaceutical firms Merck and Moderna announced Wednesday that their personalized messenger RNA (mRNA)-based cancer therapy delivered promising positive results in a large-scale late-stage clinical trial, successfully reducing the recurrence of melanoma. The breakthrough finding has sent shockwaves through the global medical and financial communities, pushing Moderna’s share price up 145% to $154 and lifting Merck’s stock by more than 12% to $152.

    The experimental treatment, named intismeran autogene, leverages the same foundational mRNA technology that powered the development of highly effective Covid-19 vaccines nearly a decade after the platform was first mainstreamed by the pandemic. While researchers have spent decades working to adapt mRNA technology for cancer treatment, this trial marks the first time an mRNA-based cancer drug has delivered positive outcomes in a large, phase-three level clinical study.

    “Today marks an extraordinary milestone for Moderna, for mRNA science and, most importantly, for patients with cancer,” Moderna Chief Executive Stephane Bancel emphasized in an official statement.

    The roughly one-year trial enrolled 1,137 participants who had undergone surgical removal of melanoma tumors. Patients were split randomly into two groups: two-thirds received the new personalized mRNA therapy in combination with pembrolizumab, the current gold-standard treatment for melanoma, while the remaining third received only pembrolizumab. The companies confirmed they will unveil full trial data at an upcoming international oncology conference and have already begun preparing regulatory submissions to seek formal approval for the treatment.

    Independent oncology experts have welcomed the results as a watershed moment for cancer immunotherapy. Lennard Lee, an oncologist and assistant professor at the University of Oxford who was not involved in the trial, called the outcome “very encouraging” and noted that the full dataset is now eagerly anticipated by the global research community.

    Marco Gerlinger, a professor of oncology at London’s Barts Cancer Institute, echoed the praise, pointing out that the results do more than benefit melanoma patients – they serve as long-awaited “proof of principle that personalised cancer vaccines work.” “I think it is fair to call it a breakthrough in the development of new cancer immunotherapies,” Gerlinger said, while adding that the initial press announcement lacked granular full-trial details that will be critical for further assessment.

    Unlike traditional one-size-fits-all cancer treatments, the personalized mRNA therapy works by first collecting a tissue sample from a patient’s tumor, mapping its unique genetic mutational “fingerprint,” then designing a custom mRNA treatment targeted to that specific signature. Similar to Covid-19 mRNA vaccines, the treatment delivers synthetic molecular instructions wrapped in microscopic lipid bubbles that enter the body’s cells and trigger them to produce specific targets that train the immune system to recognize and attack cancer cells.

    First conceptualized decades ago, mRNA technology rose to global prominence during the Covid-19 pandemic, when Moderna and Pfizer-BioNTech rolled out highly effective vaccines that dramatically reduced rates of severe illness and death from the virus. Since then, researchers have raced to adapt the platform to a wide range of other diseases, with cancer being the most high-priority area of research.

    Melanoma is among the most aggressive forms of skin cancer, with more than 330,000 new cases diagnosed across the globe in 2022 alone. Looking ahead, Bancel confirmed that the two companies will continue expanding research into intismeran autogene, testing it in combination with pembrolizumab and other existing anti-cancer therapies, as well as a standalone treatment, across a wide range of tumor types and disease stages. Upcoming trials will explore the therapy’s effectiveness for lung, bladder, and kidney cancers in addition to melanoma, opening the door for a potential revolution in personalized cancer care.

  • Trump nominates aide Heidi Overton to lead US Food and Drug Administration

    Trump nominates aide Heidi Overton to lead US Food and Drug Administration

    Former U.S. President Donald Trump has selected Dr. Heidi Overton, a senior domestic policy advisor serving in his White House, as his nominee to head the U.S. Food and Drug Administration (FDA). If the U.S. Senate votes to confirm her appointment, Overton will step into the role vacated by former FDA commissioner Marty Makary, who resigned from the post in May following public disagreements with the White House over the public safety risks of flavored vaping products.

    In a public post shared to his Truth Social platform on Wednesday, Trump lavished praise on his nominee, calling Overton a “rockstar” within his administration. He emphasized that she has built a reputation for tackling the nation’s most intractable policy challenges and delivering practical solutions aligned with the administration’s priorities for the country.

    Overton, who regularly briefs the president on domestic health policy matters, made headlines earlier this month during an Oval Office announcement focused on rolling back the number of mandatory childhood vaccinations. During that event, she delivered sharp criticism of so-called “blue states” led by Democratic governors and legislatures, urging these jurisdictions to adopt the White House’s new framework, which she described as the “gold standard” for vaccination policy.

    Should she secure confirmation, Overton will inherit a broad set of core responsibilities at the FDA, ranging from verifying the safety and effectiveness of all prescription medications sold in the U.S. to overseeing federal regulation of tobacco and nicotine products. Like most senior health officials in the second Trump administration, Overton is a staunch ally of the White House’s “Make America Healthy Again” policy movement.

    Before joining the administration, Overton served as chief policy officer at the America First Policy Institute, a conservative Washington D.C.-based think tank closely aligned with Trump’s policy agenda. A well-known opponent of abortion rights, she has previously labeled abortion “corrosive” to women’s health and has repeatedly called on the FDA to tighten restrictions and crack down on medication abortion access.

    Continuing his endorsement on Truth Social, Trump argued that Overton’s leadership is urgently needed at the agency to maintain the United States’ global position as a leader in scientific discovery and medical innovation. He added that Overton is “smart and respected by all” and that her tenure at the FDA would continue the administration’s commitment to putting “America First” and building a healthier nation.

    Industry and political sources familiar with the selection process have confirmed that Overton is Trump’s third pick for the FDA commissioner role, after the president’s first two choices — acting FDA head Kyle Diamantas and former Republican Congressman Brad Wenstrup — withdrew from consideration. Her nomination comes at a fraught moment for federal public health policy: the administration is already facing widespread criticism over its slow response to a national cyclospora parasite outbreak, and conservative activists are ramping up pressure on the FDA to restrict access to abortion medications.

    A native of the southwest, Overton earned her medical degree from the University of New Mexico School of Medicine and went on to complete postgraduate public health training at the Johns Hopkins University Bloomberg School of Public Health.

  • Lindsay Clancy’s trial put postpartum psychosis in the spotlight. Experts want progress to follow

    Lindsay Clancy’s trial put postpartum psychosis in the spotlight. Experts want progress to follow

    As the high-profile trial of Massachusetts mother Lindsay Clancy enters its fourth week, the horrific tragedy at the center of the case has dragged a little-discussed, life-threatening maternal mental health condition into the national spotlight: postpartum psychosis. The case, which has sparked urgent conversations about gaps in maternal mental health care, is renewing calls to formally classify the condition as a distinct disorder in American psychiatry’s official diagnostic handbook.

    Clancy, who admitted to killing her three young children — 5-year-old Cora, 3-year-old Dawson, and 8-month-old Callan — in January 2023, has pleaded not guilty to three counts of murder. Her legal team argues that she was incapacitated by severe postpartum psychosis triggered after the birth of her third child, a condition that left her grappling with debilitating hallucinations and delusions. One month before the killings, Clancy explicitly told her mother Paula Musgrove and then-husband Patrick Clancy that she was experiencing intrusive thoughts of harming her children. Musgrove testified this week that her daughter repeatedly insisted the disturbing thoughts were not her own, saying “This isn’t me, I’ve never been like this before” — a claim Musgrove confirmed aligned with Clancy’s prior behavior.

    Clinical and forensic psychologist Paul Zeizel testified Wednesday that Clancy’s condition left her unable to recognize the wrongfulness of her actions or adjust her behavior to comply with the law. Prosecutors, however, argue the killings were a premeditated, intentional act. What is not debated by medical experts is the dangerous nature of postpartum psychosis, which is classified as an urgent medical emergency. Symptoms of the condition include rapid-onset mania, depression, hallucinations, and fixed false delusions that pull patients completely out of touch with reality. Experts note the condition has a distinct “waxing and waning” pattern that can lull loved ones into a false sense of security: Patrick Clancy testified that on the day of the killings, his ex-wife appeared to be having one of her best days, playing outside with the children to build a snowman. Hours later, when he returned home from picking up dinner, he found his children dead and Clancy gravely injured from a suicide attempt.

    That seemingly sudden shift is a classic hallmark of the condition, explained Jennifer Payne, a reproductive psychiatry expert at the University of Virginia. “A woman can appear fine one minute and be really ill a little bit later,” Payne said. While the exact causes of postpartum psychosis remain under-researched, experts have linked it to dramatic hormonal shifts after childbirth and a history of prior mental health conditions. In rare severe cases, between 1% and 4% of experiences with the condition result in harm or death to children or the mother, according to existing research.

    The biggest barrier to better awareness, screening, and treatment, patients and providers agree, is that postpartum psychosis is not formally recognized as a distinct disorder in the American Psychiatric Association’s *Diagnostic and Statistical Manual of Mental Disorders (DSM-5)* — the definitive reference guide used by clinicians, medical schools, and insurance providers across the U.S. Advocates like Veerle Bergink, professor of psychiatry and director of the Mount Sinai Women’s Mental Health Center, have spent years pushing for the condition’s inclusion, arguing that formal classification is the foundational step to advancing care.

    “You can only investigate and talk about the disease if you give the disease a name, and if it has criteria,” Bergink explained. Without formal listing in the DSM-5, the condition is often omitted from medical school curricula, fails to attract research funding, lacks a standard insurance billing code, and leaves patients without a clear pathway to care. For Meghan Cliffel, a postpartum psychosis survivor who experienced rapid-onset hallucinations and delusions eight months after giving birth to her second daughter in 2015, this lack of recognition feels like deliberate erasure.

    Clifel recalled that within 24 hours of her first symptoms, she was handcuffed to a gurney and admitted to a psychiatric hospital, where she spent 12 days receiving treatment. She recovered with a multi-pronged care plan including therapy and lithium, and later safely had a third child by starting prophylactic lithium treatment immediately after birth. Even so, her road to recovery was marked by uncertainty: unlike common conditions such as breast cancer, which offer clear, step-by-step care pathways, postpartum psychosis leaves patients fumbling for support in the dark, she said.

    Calling the lack of DSM-5 classification “bananas”, Cliffel said the Clancy trial is a critical turning point for the maternal mental health community. “We cannot be surprised when tragedy happens, and instead, we can proactively build to care for mothers and families,” she said. Experts stress that postpartum psychosis is a highly treatable condition: common interventions include mood stabilizers like lithium, antipsychotic medications, electroconvulsive therapy, and inpatient psychiatric care, and most patients fully recover with timely, appropriate intervention. Advocates now hope the attention from the Clancy trial will accelerate efforts to formalize the condition’s recognition, building a standardized care system that catches symptoms early and prevents future tragedies.

  • What to know about the outbreak of a rare kind of Ebola

    What to know about the outbreak of a rare kind of Ebola

    ABUJA, NIGERIA – A deadly Ebola outbreak driven by a little-understood virus strain in the Democratic Republic of the Congo has crossed a grim threshold, exceeding 5,000 confirmed cases to rank among the worst Ebola epidemics ever documented. What makes this outbreak particularly alarming for global health authorities is its origin: the Bundibugyo virus, a rare Ebola variant for which no licensed vaccine or targeted treatment currently exists. As of Sunday, Congo’s Ministry of Health has logged 5,021 total cases, with a death toll reaching 2,378, marking this not only the deadliest outbreak of Bundibugyo Ebola on record but also the deadliest Ebola outbreak in the country’s modern history. The World Health Organization (WHO) has issued a stark warning that if unbroken transmission continues, the outbreak could eventually overtake the devastating 2014–2016 West Africa epidemic that killed more than 11,000 people.

  • Congo’s Ebola outbreak reaches 5,000 cases as it outpaces response efforts at unprecedented speed

    Congo’s Ebola outbreak reaches 5,000 cases as it outpaces response efforts at unprecedented speed

    BUNIA, Democratic Republic of Congo – New government health data released this Wednesday has marked a grim milestone in the country’s ongoing Ebola crisis: total confirmed and suspected cases have surpassed the 5,000 threshold, with response teams warning the virus is spreading at an unmatched rate that is outrunning containment efforts in one of Central Africa’s most isolated, volatile regions. As of Sunday, the Ministry of Health’s official tally stood at 5,021 total cases, including 2,378 fatalities, with the outbreak intensifying amid a perfect storm of unfavorable conditions: widespread insecurity, mass population displacement, and constant cross-community movement that has made tracking and isolating cases extremely difficult. This outbreak has already outpaced every previous Ebola event in both the speed of transmission and the scale of infection and death. Since the first case was detected, it has spread roughly three times faster than the 2014-2016 West African Ebola epidemic, which held the previous record as the deadliest outbreak on record, claiming more than 11,000 lives across the region. During a special coordination meeting convened by the World Health Organization this Tuesday, WHO Director-General Tedros Adhanom Ghebreyesus issued a stark warning about the trajectory of the crisis. “The outbreak has spread rapidly and the risk of further national and international spread remains high,” Tedros stated. “We must be frank: the epidemic is far from being under control.” Ongoing safety risks have severely constrained containment operations, as frontline health workers have repeatedly become targets of violence, particularly in Ituri province – the region currently bearing the brunt of the outbreak. Just this week, new details emerged of an attack on a public health team that underscored the dangers responders face. On Monday, local residents attacked a health deployment in Aru territory after authorities announced a suspected Ebola case in the area. A rioting mob set fire to an ambulance and caused significant damage to two additional vehicles, according to Michael Wani, president of the Union of Cultural Associations for the Development of Ituri. The attack is the latest in a series of incidents that have hampered response work, alongside additional complicating factors including the presence of mobile gold mining populations across eastern Congo that are hard to reach and monitor. Exhausted response teams have already reported struggling to keep up with contact tracing demands, as new infections emerge faster than workers can identify and quarantine potential exposures, pushing the crisis further beyond the capacity of existing public health efforts.

  • Mobile gold miners in eastern Congo complicate health workers’ efforts to contain Ebola

    Mobile gold miners in eastern Congo complicate health workers’ efforts to contain Ebola

    Nestled in the conflict-wracked Ituri Province of eastern Democratic Republic of the Congo, hundreds of artisanal gold miners — including children like 11-year-old Isaac Batisa — crowd into narrow, hand-dug pits and deep underground shafts every day, panning and digging for small traces of the precious metal to earn meager wages that feed their families. For Batisa, who lost his parents and two brothers in a rebel attack and now supports five younger siblings while living with his aunt, Ebola, the deadly viral outbreak that has already claimed more than 2,300 lives across the country, is not his immediate priority. “We don’t know about Ebola here,” he says, noting he often earns as little as $2 a day for his backbreaking labor.

    This remote, hard-to-reach mining site in Iga-Barrière offers a rare, unfiltered look at one of the most intractable barriers to containing the fastest-growing Ebola outbreak in recorded history. While no confirmed Ebola cases have yet been documented at Congo’s artisanal mining sites, public health officials warn that the true spread of the virus in these isolated areas remains nearly impossible to track. The vast majority of new cases and deaths are currently recorded among unmonitored populations, a category that perfectly describes the transient workforce that moves between small mining claims, rural villages and urban population centers on a constant basis.

    Unlike formal industrial mining operations, most small-scale artisanal mines in eastern Congo are unregulated and often illegal, with miners actively evading local authorities to access gold deposits. Workers dig with nothing more than basic hand tools like shovels and hand-held pans, crowding shoulder-to-shoulder in pits and tunnels with no structural reinforcement to prevent collapses. Crucial public health measures to slow Ebola transmission — including regular handwashing stations and physical distancing protocols — are entirely absent from these work sites. This creates a perfect storm for rapid spread of the virus, which spreads through direct contact with infected bodily fluids and contaminated surfaces.

    Complicating response efforts even further, the strain behind the current outbreak — the Bundibugyo virus — is one of the less common variants of Ebola, meaning no proven targeted treatments or vaccines are currently available for widespread use. As of 2024, the outbreak has spread to six Congolese provinces, with nearly 5,000 confirmed cases and 2,325 recorded deaths, 90% of which are concentrated in Ituri. Public health experts now warn the outbreak could surpass the 2014–2016 West Africa Ebola crisis, which killed more than 11,000 people, to become the deadliest Ebola outbreak in history.

    The transient nature of artisanal mining work is the single biggest obstacle to effective contact tracing, according to frontline Ebola response workers. Miners regularly cross village and provincial boundaries in search of new gold deposits, while small-scale mineral traders move between remote mining camps and densely populated urban centers to sell extracted gold. This constant movement makes it nearly impossible to track potential contacts once an infection is identified.

    “Artisanal miners may come into contact with several communities as they move from one place to another, which can facilitate the transmission of the virus if a person is infected,” explained Mari Ndika, an Ebola response coordinator leading local monitoring efforts. Community health worker Anna Ndroy Kansime recently experienced this gap firsthand: two miners identified as close contacts of a confirmed Ebola case vanished after moving to an unregistered mining site, their current location still unknown. There is also no formal system to register mining workers or record their travel, leaving response teams blind to potential new transmission chains, Kansime added. “People can become infected in one place and travel elsewhere before monitoring teams know they have been exposed, potentially creating new chains of transmission that are difficult to trace.”

    For the miners and their families, there is often no other option but to keep digging. Decades of conflict in eastern Congo, where more than 100 armed militant groups operate including the ADF and CODECO militias that terrorize Ituri, have displaced millions of people and pushed countless families into extreme poverty. A 2024 OECD report estimates that roughly 2 million Congolese work in artisanal and small-scale mining, which produces not just gold but also coltan, tin and tungsten that power global electronics supply chains. UNICEF estimates that 15% of Congolese children between the ages of 5 and 17 are engaged in child labor, with no reliable recent count of how many of those children work in mines. At the Iga-Barrière site, children work alongside adults, and even pregnant women work in open pits late into their third trimesters, Kansime confirmed.

    “In Ituri province, where conflict has uprooted families and where jobs are scarce, the mines offer the only possibility of cash income, however dangerous the work,” said Singoma Aimé, a 36-year-old miner at the site. He added that miners have repeatedly called for basic public health infrastructure to protect themselves from Ebola: “We especially need hand-washing facilities because everyone comes from home to work at the site, and we lack any kind of adequate protection.”

    International humanitarian organizations warn the outbreak’s continued spread is an urgent global crisis. Last week, Mercy Corps warned that confirmed cases have now been recorded along a major travel route just 22 miles from the South Sudanese border, raising fears of cross-border spread that could expand the crisis exponentially. Trish Newport, emergency coordinator for Doctors Without Borders (MSF), called the outbreak’s unrelenting speed “extremely concerning” in an interview with the Associated Press, noting it continues to outpace all containment and contact tracing efforts.

    “We see family members that come in who have had 15 people in their family die,” Newport said. “We rapidly need to scale up to be able to prevent more deaths from happening, more families and communities from being impacted.”

    Response teams say the path forward requires targeted outreach to mining communities, working with local authorities, mine managers and community leaders to educate miners on Ebola prevention and establish systems to track suspected cases. But deep structural barriers remain: impassable rural roads, the constant presence of armed groups that block access to remote areas, and the simple reality that mining is the only source of food and income for millions of Congolese. “For many families, gold is what pays for food,” Kansime said — a reality that leaves few with the option to stop working, even in the face of a deadly pandemic.

  • Doctors remove 3.1kg stone from man’s bladder and claim record

    Doctors remove 3.1kg stone from man’s bladder and claim record

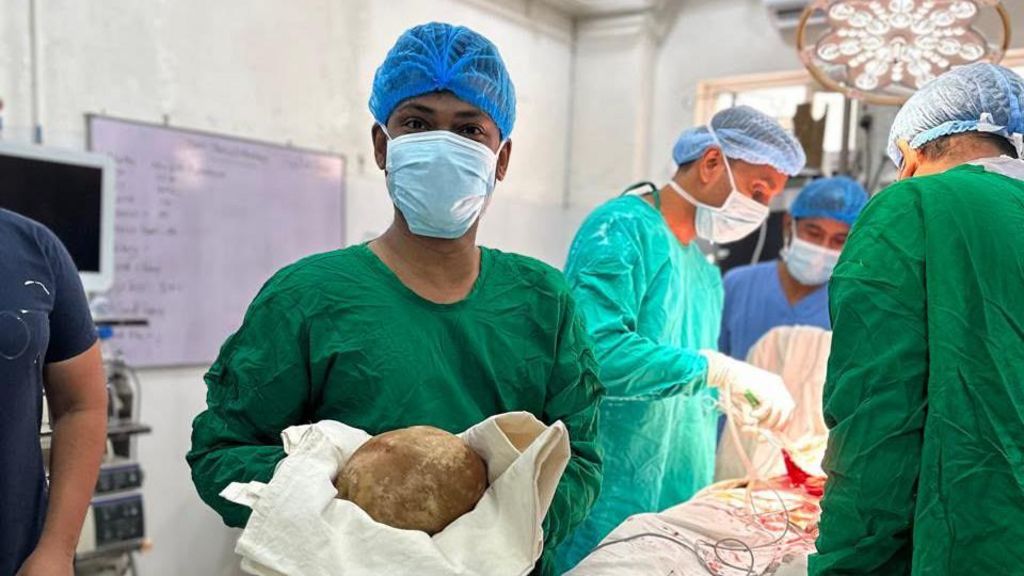
    A medical team at Sri Lanka’s Trincomalee General Hospital has made global medical history after successfully extracting an extraordinarily large bladder stone weighing 3.1 kilograms (6.8 pounds) — a mass roughly equal to the weight of a full-term newborn baby and matching the dimensions of an ostrich egg.

    The unprecedented procedure was performed last week on a 55-year-old male patient who had initially been admitted to the eastern Sri Lankan hospital for care following a stroke. While managing his post-stroke treatment, clinicians noticed the patient was experiencing persistent difficulty urinating, which prompted further diagnostic testing. That evaluation uncovered the massive solid mineral mass growing in his urinary bladder.

    Speaking to BBC Sinhala following the successful surgery, lead surgeon Dr Prahalahan Balakrishnan confirmed that based on all available global medical documentation, this is the largest surgically removed bladder stone ever recorded. Measuring approximately 17 centimeters wide, the mass is only slightly shorter than the previous record-holding bladder stone removed in Brazil in 2003, which was recognized by Guinness World Records at 17.9 centimeters long but weighed just 1.9 kilograms — more than a kilogram less than the specimen extracted in Sri Lanka.

    Dr Balakrishnan added that the newly removed stone had likely been developing gradually in the patient’s bladder for anywhere between five and 10 years before its detection. Despite the stone’s extraordinary size, the surgeon confirmed the patient is now in very good health following the procedure. He remains hospitalized to continue receiving ongoing care for the stroke that led to his initial admission.

    Bladder stones form when concentrated minerals in urine crystallize and clump together into solid masses. They most often develop when the bladder does not fully empty during urination, leaving behind stagnant, concentrated urine that promotes crystal formation. Small bladder stones, often no larger than grains of sand, can pass out of the body without medical intervention, but any stone larger than 1 centimeter can block urinary flow and require surgical removal. Any mass larger than 4 centimeters is already classified as a giant bladder stone, making the 17-centimeter Sri Lankan specimen far outside the range of typical cases.

  • Congo’s fast-moving Ebola outbreak becomes the country’s worst with over 2,300 dead

    Congo’s fast-moving Ebola outbreak becomes the country’s worst with over 2,300 dead

    In the conflict-ravaged eastern region of the Democratic Republic of Congo, a rapidly spreading Ebola outbreak fueled by the rare Bundibugyo virus has become the deadliest Ebola event recorded in the Central African nation, new government data confirms. As of early Monday, the outbreak has hit a grim milestone: 4,945 confirmed and probable cases, with 2,325 recorded deaths — a toll that has already outstripped the 2,299 fatalities from Congo’s 2018-2020 Ebola outbreak, the previous deadliest event in the country’s history. This marks the 17th Ebola outbreak the country has faced, and by far the most geographically extensive and fast-moving.

    The latest 24-hour reporting period saw 101 new cases and 33 additional deaths, underscoring the relentless spread of the virus. To date, more than 1,000 patients have recovered from infection, while 730 people remain under care in hospitals or isolation facilities. Unlike previous major Ebola outbreaks, there are currently no approved vaccines or specific antiviral treatments for the Bundibugyo variant driving this surge. Clinical trials for experimental vaccines and therapies are currently ongoing in Ituri province, the epicenter of the outbreak that has now spread to six total provinces.

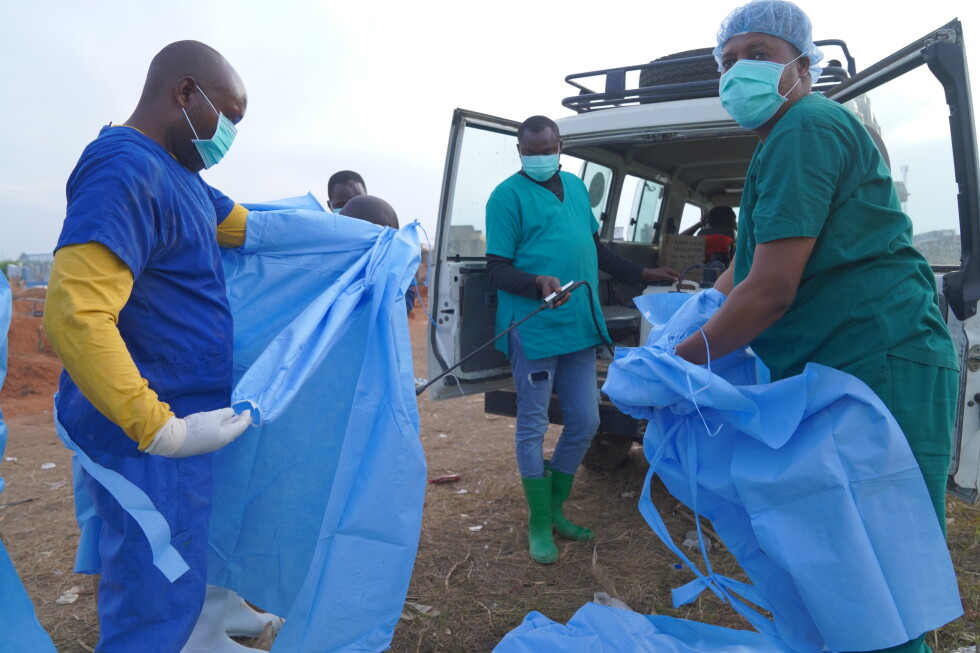
    Responders face a cascading series of obstacles that have allowed the virus to outpace containment efforts. A large share of new infections and fatalities are being detected in community members who were not already under active monitoring, a gap that allows silent transmission to continue. Additional challenges include work stoppages by unpaid frontline health workers, persistent security threats from active rebel groups in the region, deep-seated distrust among communities that have endured decades of conflict and trauma, impassable terrain hampered by poorly maintained roads, and widespread misinformation that denies the existence of Ebola entirely.

    Over the weekend, the World Health Organization (WHO) warned that the outbreak continues to expand at an “exceptional pace” that outstrips current contact tracing and containment work. Last week alone, the outbreak hit a new weekly record with 579 new cases and 304 deaths. Global health officials have warned that if current trends continue, this outbreak could surpass the 2014-2016 West African Ebola epidemic, the global deadliest on record which killed more than 11,000 people across three countries.

    In response to the worsening crisis, international actors have begun ramping up support. The WHO confirmed that a major expansion of response activities is currently underway to reverse the outbreak’s momentum. On Friday, United Nations Under-Secretary-General for Humanitarian Affairs Tom Fletcher announced an additional $30.5 million in emergency funding for the response, alongside the deployment of 20 extra specialized personnel to support frontline efforts. Fletcher framed the escalating crisis as a critical warning to the international community, saying, “We need speed, scale and solidarity before this virus gets even further ahead of us.”

  • Ebola outbreak now DR Congo’s deadliest ever

    Ebola outbreak now DR Congo’s deadliest ever

    A rapidly accelerating Ebola epidemic sweeping through the Democratic Republic of the Congo (DRC) has officially become the deadliest outbreak the country has ever experienced, new official government data released Monday confirms. With 2,325 fatalities recorded among 4,945 confirmed cases, the current 17th documented Ebola outbreak in the DRC has now surpassed the 2018–2020 epidemic, which killed 2,299 people according to World Health Organization (WHO) statistics.

    The United Nations has warned that this outbreak is “the fastest growing on record,” with one person dying from the virus every half an hour across affected regions. Unlike previous outbreaks, the current surge is driven by the Bundibugyo strain of Ebola, for which no specifically approved vaccine or targeted treatment currently exists. Like all Ebola variants, it spreads through direct contact with infected bodily fluids and causes life-threatening hemorrhagic fever.

    First publicly declared on May 15, health experts confirm the virus had already been circulating undetected in communities for several weeks before the official announcement. The outbreak has taken root in the country’s remote northern and eastern regions, where central government authority is limited, public health infrastructure is chronically underfunded and sparse, and armed rebel groups have operated freely for decades. It first emerged in the conflict-ravaged northeastern province of Ituri, and has since spread to five additional provinces across the DRC, a large central African nation with a population of more than 100 million people.

    Global public health officials note response efforts are grappling with a critical barrier: deep-rooted community mistrust of official health interventions. In Bunia, the provincial capital of Ituri where the majority of cases have been confirmed, protective measures are barely enforced. An Agence France-Presse correspondent on the ground observed that while local officials ordered traders to install hand-washing stations at market entrances, crowds of shoppers continue to gather with little adherence to safety protocols.

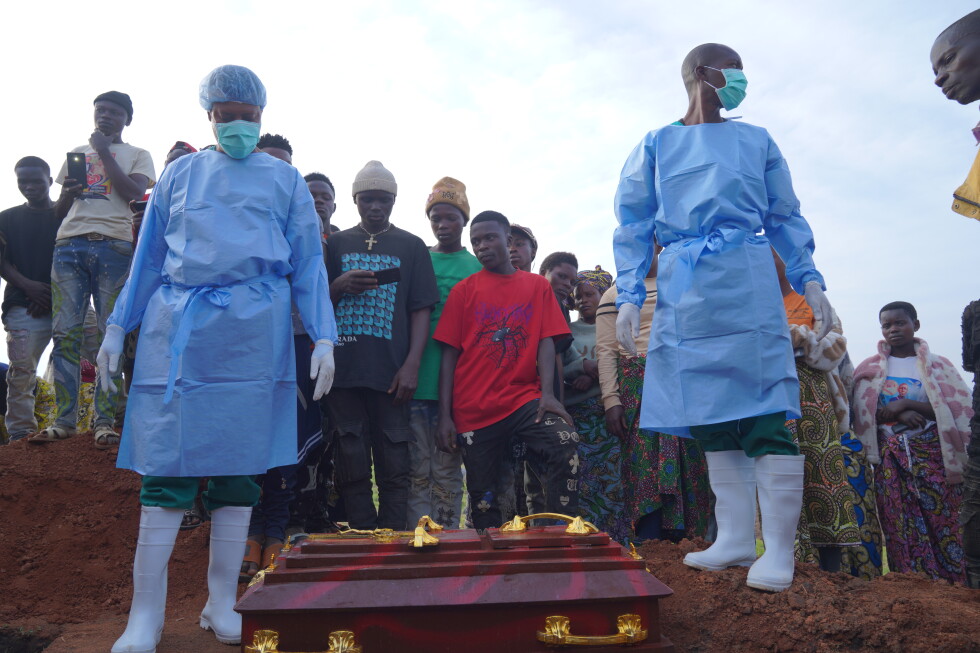
    “Community engagement in the response is still far too weak,” explained Mohamed Janabi, WHO’s Regional Director for Africa. He added that over 70% of Ebola deaths occur in community settings rather than in designated treatment centers, as many families opt to care for sick relatives at home instead of seeking formal care. Jean-Paul Malo Lotsima, a civil society representative in Ituri’s Djugu territory, explained that many local residents misattribute early Ebola symptoms to poisoning or other common illnesses, delaying medical intervention. “It’s often at the last minute, when the family realizes that the situation is getting worse, that patients are taken to hospital. And sometimes, they die on the way,” he said.

    Flavier Ngurima, a resident of Nizi, one of the outbreak’s hardest-hit hotspots, shared that his own brother died before he could reach a treatment center. “We had called on a nurse from the family to treat him at home because the patient and the family members were afraid to go to the ETC (treatment centre),” he said. “They said that over there, a lot of people die.”

    Beyond community mistrust, access to affected areas is severely complicated by ongoing armed conflict in many impacted regions. North Kivu and South Kivu provinces, which have recorded cases, are split by active front lines between the Congolese national army and the Rwandan-backed anti-government M23 rebel group, which controls large swathes of territory.

    The international public health response has also faced widespread criticism for being slow, under-resourced and uncoordinated. In recent weeks, local health workers including nurses and safe burial teams have held strikes and protests across multiple Ituri hospitals to demand long-overdue bonus payments that have not been disbursed. On Friday, the International Council of Nurses issued a formal statement urging DRC government authorities to deliver fair compensation and adequate protective equipment to frontline workers fighting the outbreak.

    Currently, several experimental vaccines are undergoing clinical trials to test their effectiveness against the Bundibugyo strain. Last week, the WHO announced it was targeting a reversal of outbreak spread within three months. To date, the deadliest Ebola epidemic in global history remains the 2013–2016 West African outbreak, which killed more than 11,300 people, primarily in Liberia, Sierra Leone and Guinea.