分类: health

  • Africa’s Ebola outbreak public health emergency of int’l concern: WHO

    Africa’s Ebola outbreak public health emergency of int’l concern: WHO

    GENEVA – In an official announcement posted to its website Sunday, the World Health Organization (WHO) has formally designated the ongoing Ebola outbreak driven by the Bundibugyo virus across the Democratic Republic of the Congo (DRC) and Uganda as a Public Health Emergency of International Concern (PHEIC), stopping short of classifying the event as a full pandemic emergency.

    The latest epidemiological data published by the WHO, updated through May 16, 2026, paints a preliminary but concerning picture of the outbreak’s spread. In the DRC’s northeastern Ituri Province, health authorities have recorded eight confirmed Ebola cases, 246 suspected cases, and 80 reported deaths among suspected patients. One additional confirmed case has been detected in Kinshasa, the DRC’s capital, marking the virus’s reach into a major urban center far from the original outbreak zone. Neighboring Uganda has also confirmed two cases of Ebola traced back to importation from the DRC, both detected in the Ugandan capital Kampala. To date, researchers have found no clear epidemiological connection between the two Ugandan cases, adding to uncertainties around transmission dynamics.

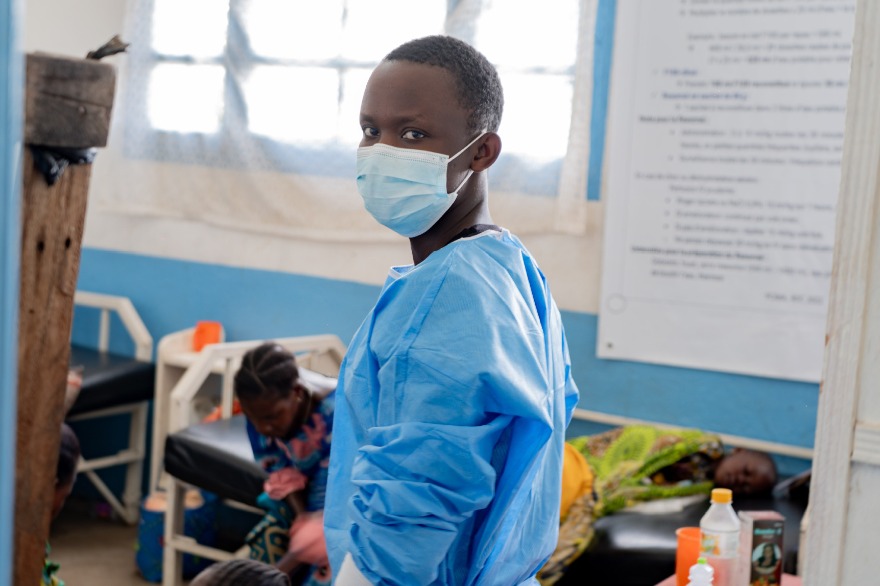
    Among the most alarming early developments is the death of at least four frontline healthcare workers who treated Ebola patients in affected regions. These fatalities have amplified experts’ concerns about ongoing nosocomial, or hospital-based, transmission of the virus, a risk that can quickly overwhelm under-resourced local health systems.

    The WHO emphasized that large gaps remain in understanding the full scope of the outbreak. Significant uncertainty surrounds the actual total number of infections, the full geographic range of virus circulation, and the transmission links connecting confirmed and suspected cases. Compounding these challenges is the absence of any globally approved, targeted therapeutics or vaccines specifically designed to protect against or treat infection with the Bundibugyo strain of Ebola.

    To coordinate a unified global response, the WHO announced it will convene an independent Emergency Committee in the near term to develop evidence-based guidance for response measures for affected nations and the international public health community.

    WHO officials warn that early indicators suggest the outbreak is far larger than current detected and reported case counts indicate. Key red flags include a high positivity rate among initial patient samples, the confirmation of cases in two capital cities (Kinshasa and Kampala), and a steady upward trend in both suspected cases and deaths across Ituri Province. Multiple structural factors are amplifying the risk of widespread spread: persistent insecurity in affected regions that disrupts outbreak surveillance and response, an ongoing humanitarian crisis that has left millions of vulnerable people without access to adequate health care, high cross-border and internal population mobility, the location of current outbreak hotspots in urban and semi-urban areas, and an extensive network of unregulated informal health care facilities that lack infection control infrastructure.

  • WHO declares international emergency as Ebola outbreak kills more than 80 in DR Congo

    WHO declares international emergency as Ebola outbreak kills more than 80 in DR Congo

    The World Health Organization (WHO) has officially declared a Public Health Emergency of International Concern (PHEIC) in response to a fast-spreading Ebola outbreak caused by the rare Bundibugyo strain in the Democratic Republic of the Congo (DRC), which has already claimed more than 80 lives across two countries. This marks the 17th Ebola outbreak the Central African nation has faced, with public health experts warning of extreme risks of regional and cross-border spread amid a lack of targeted medical countermeasures.

    The first confirmed case in Goma, a major population hub in eastern DRC currently held by the Rwanda-backed M23 militia, was verified by national laboratory testing on Sunday, amplifying global alarm over the outbreak’s trajectory. According to the Africa Centres for Disease Control and Prevention (Africa CDC), as of Saturday, the outbreak has been linked to 88 confirmed deaths and 336 suspected cases of the highly contagious haemorrhagic fever.

    Professor Jean-Jacques Muyembe, director of the Congolese National Institute for Biomedical Research (INRB), detailed that the Goma patient is the widow of an Ebola victim who died in the northeastern city of Bunia. The woman, already infected when she traveled to Goma after her husband’s death, represents the first confirmed case in a major urban center, raising fears of wider community transmission.

    WHO Director-General Tedros Adhanom Ghebreyesus announced the emergency declaration via the social platform X, noting that while the outbreak qualifies as a PHEIC— the global body’s second-highest alert level under the International Health Regulations (IHR), with a pandemic classified as the highest— it does not yet meet the formal criteria for a pandemic. The WHO emphasized that critical gaps remain in understanding the outbreak’s full scale, writing, “There are significant uncertainties to the true number of infected persons and geographic spread.”

    A core challenge facing response teams is the nature of the strain itself. Unlike the more common Zaire Ebola strain, for which effective vaccines are widely available, the Bundibugyo strain— first identified in 2007— has no licensed vaccine or specific antiviral treatment. DRC Health Minister Samuel-Roger Kamba highlighted the strain’s extreme virulence, noting that its fatality rate can reach 50 percent. By comparison, the Zaire strain has a recorded fatality rate of 60 to 90 percent, but the availability of vaccines and treatments has drastically reduced mortality in recent outbreaks.

    The current outbreak was first confirmed in Ituri Province, a northeastern region bordering Uganda and South Sudan, on August 15. Local civil society representative Isaac Nyakulinda told Agence France-Presse (AFP) that communities in the affected area have been struggling to cope for weeks. “We’ve been seeing people die for the past two weeks,” Nyakulinda said. “There is nowhere to isolate the sick. They are dying at home and their bodies are being handled by their family members, increasing the risk of further transmission.”

    Congolese health officials traced the outbreak back to an index case, a nurse who first presented with Ebola symptoms at a Bunia health facility on April 24. Early symptoms of Ebola include fever, vomiting, and haemorrhaging, progressing to severe organ failure and internal bleeding in advanced cases. The virus, which is thought to originate in bat populations, spreads between humans through direct contact with bodily fluids or infected blood; victims only become contagious once symptoms develop, and the incubation period can last up to 21 days.

    On Saturday, officials confirmed that the outbreak has already crossed international borders, with one Congolese national dying of the disease in neighboring Uganda. Medecins Sans Frontieres (MSF, also known as Doctors Without Borders), the leading medical aid group working on the ground, is mobilizing for a large-scale emergency response, but has flagged multiple barriers to effective action.

    “The number of cases and deaths we are seeing in such a short timeframe, combined with the spread across several health zones and now across the border, is extremely concerning,” said Trish Newport, MSF’s Emergency Programme Manager. The DRC’s poor transport and communications infrastructure, a longstanding challenge for public health responses, has slowed the movement of critical medical supplies to affected regions. The country, home to more than 100 million people and four times the size of France, has limited paved road networks in remote rural areas where the outbreak first took hold.

    Most of the early transmission has occurred in hard-to-reach areas, meaning only a small share of suspected cases have been confirmed via laboratory testing. Even so, the WHO says early indicators point to a far larger outbreak than currently documented: high positivity rates from initial tested samples, cross-border transmission, and rising numbers of suspected cases “all point towards a potentially much larger outbreak than what is currently being detected and reported, with significant local and regional risk of spread.”

    This outbreak comes just months after DRC declared an end to its previous Ebola outbreak in the same region, which was declared eradicated in December 2024 after killing 34 people. Since Ebola was first identified in 1976, the virus has killed roughly 15,000 people across Africa, despite major medical advances in prevention and treatment over the past decade. The 2018-2020 Ebola outbreak in eastern DRC remains the deadliest in the country’s history, killing nearly 2,300 people before it was contained.

  • How worrying is the Ebola outbreak in DR Congo?

    How worrying is the Ebola outbreak in DR Congo?

    An evolving Ebola outbreak in the Democratic Republic of the Congo (DRC) has triggered urgent global concern, after weeks of undetected spread in a conflict-ravaged region that complicates containment efforts. Health officials warn that this outbreak, driven by the rare Bundibugyo Ebola species, carries unique challenges that put the global public health community at a critical turning point.

    As of current reporting, nearly 250 suspected cases and 80 confirmed deaths have been recorded, with significant uncertainty around the true scope of transmission due to the late detection of the outbreak. The World Health Organization has designated the event a Public Health Emergency of International Concern (PHEIC) — a designation that does not predict a COVID-19-style global pandemic, but signals the complexity of the situation requires coordinated cross-border action.

    “The overall global risk posed by this Ebola outbreak remains extremely low,” experts emphasize, echoing a reality seen even during the 2014-2016 West African disaster, the largest Ebola outbreak on record that infected more than 28,600 people and killed over 11,000, which only resulted in three cases in the United Kingdom, all among volunteer healthcare workers. But for the affected region and global public health, the stakes remain high.

    Unlike more common Ebola strains that have proven vaccines and targeted treatments, Bundibugyo Ebola has only caused two prior outbreaks, recorded in 2007 and 2012, with mortality rates ranging between 30% and 50% of those infected. No vaccines or antiviral therapies have been formally approved for this specific strain, though a small number of experimental candidates are available. Even diagnostic testing for Bundibugyo is unreliable: initial test results for this outbreak returned negative for Ebola, requiring advanced laboratory analysis to confirm the rare strain was responsible.

    Prof Trudie Lang, an expert from the University of Oxford, describes Bundibugyo as “one of the most significant concerns” of the current response. Ebola, a zoonotic disease that originates in wild animal populations (primarily fruit bats), spreads to humans through close contact with infected animals, then passes between people via exposure to infected bodily fluids, most often after symptoms develop.

    Symptoms of Ebola emerge between 2 and 21 days after infection, beginning with flu-like indicators including fever, headache and fatigue, before progressing to severe vomiting, diarrhea, organ failure, and in some cases internal and external bleeding. Without approved targeted treatments for Bundibugyo, care relies on optimized supportive care — managing pain, secondary infections, fluid balance and nutrition — with early intervention dramatically improving survival odds.

    The delayed detection of this outbreak is among the most worrying factors. The first confirmed case, a nurse, developed symptoms on April 24, but it took three weeks to confirm an Ebola outbreak was underway. “Ongoing transmission has occurred for several weeks, and the outbreak has been detected very late, which is concerning,” explained Dr Anne Cori of Imperial College London. This delay has put response teams at a disadvantage, with the World Health Organization noting the true number of infections is likely far higher than current reported figures.

    Containment efforts are further complicated by the chaotic context of the outbreak zone: the eastern region of DRC has been torn by ongoing civil conflict, displacing more than 250,000 people from their homes. Most affected communities are located in mobile mining towns, where transient populations move frequently between local communities and across national borders, amplifying the risk of wider spread.

    Despite these steep challenges, experts note that the DRC has accumulated extensive experience responding to repeated Ebola outbreaks over the past two decades. Dr Daniela Manno, a researcher at the London School of Hygiene & Tropical Medicine, points out that the national and international response capacity is “significantly stronger today than it was a decade ago,” ahead of the 2014 West African outbreak.

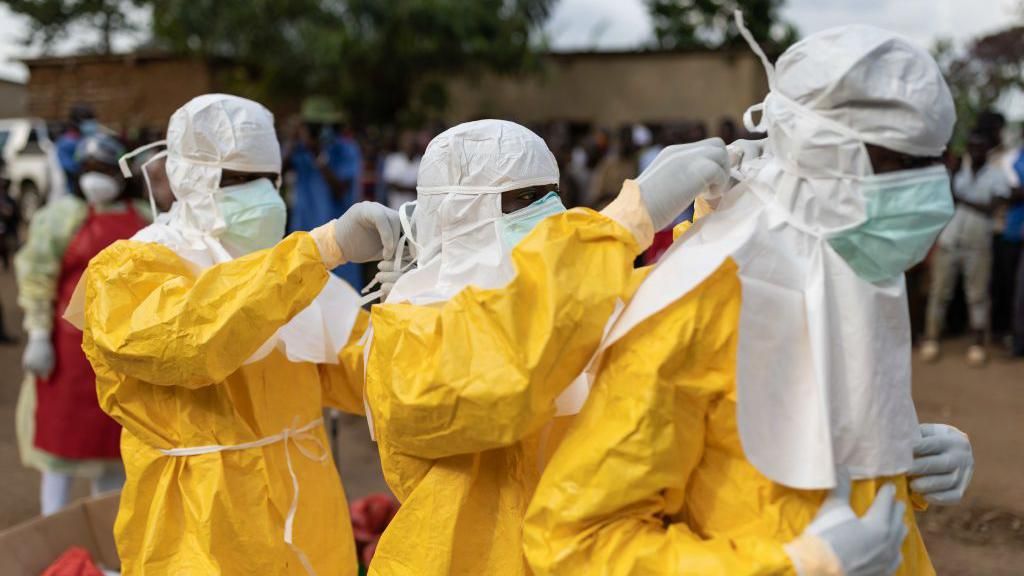
    Core containment strategies focus on rapid identification of infected cases, contact tracing to stop chains of transmission, preventing spread within healthcare facilities where patients are most contagious, and conducting safe burials for victims, as deceased bodies remain highly infectious. The trajectory of the outbreak — whether it is quickly contained or spirals into a large-scale disaster like the 2014-2016 event — will depend entirely on the speed and effectiveness of the current response.

  • WHO declares global health emergency over Ebola outbreak in Congo and Uganda

    WHO declares global health emergency over Ebola outbreak in Congo and Uganda

    On Sunday, World Health Organization Director-General Tedros Adhanom Ghebreyesus issued the highest global alert level for an ongoing Ebola outbreak spanning the Democratic Republic of the Congo and neighboring Uganda, following a surge in suspected infections that has already claimed 88 lives. As of the latest official count, more than 300 suspected cases have been documented across the two East-Central African nations.

    In a public update posted to the social platform X, the WHO moved quickly to clarify that the outbreak does not qualify for a pandemic-level classification on par with the COVID-19 crisis, and explicitly recommended against nations closing international borders to contain the spread.

    Ebola is a severe, highly contagious viral disease that spreads through direct contact with infected bodily fluids, including blood, vomit and semen. While outbreaks of the disease remain relatively rare, infections frequently result in death for affected patients. What makes the current crisis particularly challenging for global health authorities is that it is driven by the Bundibugyo variant — a rare strain of Ebola for which no approved vaccines or targeted treatments currently exist.

    According to WHO data, the overwhelming majority of cases are concentrated in the Democratic Republic of the Congo, with only two confirmed cases detected across the border in Uganda. The outbreak was first officially reported last Friday, originating in the DRC’s eastern Ituri Province, a border region adjacent to both Uganda and South Sudan. By the following day, the Africa Centres for Disease Control and Prevention had logged 336 suspected cases and 87 confirmed deaths.

    Ugandan health authorities confirmed their first imported case from the DRC on Saturday; that patient later died in a Kampala hospital, and a second case was shortly after confirmed in the capital. WHO officials noted that the two Ugandan cases have no known epidemiological links to one another, and both patients had recently traveled from the DRC.

    Tedros acknowledged deep uncertainties surrounding the full scope of the crisis, telling reporters: “There are significant uncertainties to the true number of infected persons and geographic spread associated with this event at the present time. In addition, there is limited understanding of the epidemiological links with known or suspected cases.”

    This is only the third documented outbreak of the Bundibugyo variant in recorded history. The strain was first identified during a 2007-2008 outbreak in Uganda’s Bundibugyo District, which infected 149 people and killed 37. The second outbreak occurred in 2012 in Isiro, DRC, where 57 cases were reported and 29 people died from the infection. More than 20 Ebola outbreaks of various strains have occurred across the DRC and Uganda in modern history.

    The WHO’s declaration of a Public Health Emergency of International Concern, or PHEIC, is formally intended to accelerate international action and mobilize funding, supplies and coordination from donor nations and global aid agencies. But the move has drawn scrutiny amid a mixed track record for past emergency declarations. When the organization declared mpox outbreaks across the DRC and other African nations a global PHEIC in 2024, public health experts criticized the global response for failing to rapidly deliver critical supplies including diagnostic tests, therapeutics and vaccines to affected regions.

  • WHO declares Ebola outbreak in DR Congo a global health emergency

    WHO declares Ebola outbreak in DR Congo a global health emergency

    The World Health Organization (WHO) has issued its highest-level alert for the ongoing Ebola outbreak spreading across eastern Democratic Republic of the Congo (DRC), classifying the event as a Public Health Emergency of International Concern (PHEIC). As of the latest official update, the outbreak — which is caused by the rare Bundibugyo Ebola strain — has recorded roughly 246 suspected cases and 80 confirmed deaths across the region, though global health officials stress that the event does not rise to the level of a pandemic emergency.\n\nIn an official statement, WHO Director-General Dr Tedros Adhanom Ghebreyesus highlighted critical gaps in current outbreak data, noting that “significant uncertainties remain around the true size of the infected population and the full geographic scope of the virus’s spread.” Unlike more common Ebola strains, for which multiple approved vaccines and antiviral treatments exist, there are currently no licensed medical countermeasures for the Bundibugyo strain, raising additional concerns for frontline response teams.\n\nTo date, eight cases have been definitively confirmed through laboratory testing. Infections and suspected deaths have been recorded across three high-risk health zones: Bunia, the provincial capital of Ituri; Mongwalu, a major gold-mining hub; and Rwampara, another mining-focused town. Alarmingly, the virus has already crossed international borders, with two confirmed cases detected in neighboring Uganda. Ugandan health authorities confirmed that one of those cases, a 59-year-old man, died from the virus earlier this week.\n\nThe WHO warns that all countries sharing a border with the DRC face elevated risk of further spread, driven by high volumes of cross-border population movement, routine trade activity, and regular travel between affected and unaffected regions. In response to the outbreak, the global health body has issued a series of formal guidance for affected and at-risk nations. It has called on the DRC and Uganda to immediately activate emergency operations centers, tasked with scaling up case monitoring, contact tracing, and evidence-based infection prevention protocols. To curb transmission, the WHO recommends that all confirmed cases be isolated immediately and receive clinical care until two consecutive Bundibugyo-specific PCR tests, collected at least 48 hours apart, return negative results.\n\nFor neighboring countries that have not yet recorded cases, the WHO advises strengthening routine disease surveillance and improving real-time public health reporting to detect imported cases early. The agency has also pushed back against overly restrictive public health measures, emphasizing that countries outside the affected region have no scientific justification for closing borders or imposing broad bans on travel and trade, noting that such actions are typically driven by public fear rather than data.\n\nFirst identified in 1976 in what is now the DRC, Ebola is a zoonotic virus believed to originate in bat populations, and this current event marks the 17th Ebola outbreak the country has faced since the virus was first discovered. The pathogen spreads through direct contact with infected bodily fluids or broken skin, and causes progressive illness that often leads to severe internal bleeding and multiple organ failure. Early, non-specific symptoms include fever, muscle aches, extreme fatigue, headache, and sore throat, which quickly progress to vomiting, diarrhea, widespread rash, and abnormal bleeding. The WHO reports that the average global fatality rate for Ebola sits around 50%, and no universal curative treatment has been fully validated for all strains to date.\n\nThe Africa Centres for Disease Control and Prevention (Africa CDC) has previously echoed the WHO’s concern over the outbreak’s trajectory, pointing to multiple elevated risk factors that could drive rapid spread. These include the presence of transmission in densely populated urban areas of Rwampara and Bunia, as well as informal, mobile workforces in Mongwalu’s gold mining sector that make contact tracing extremely challenging. Africa CDC Executive Director Dr Jean Kaseya emphasized that large-scale cross-border population movement between affected DRC regions and neighboring countries means coordinated regional action is non-negotiable to contain the outbreak.\n\nOver the past 50 years since Ebola was first discovered, approximately 15,000 people across African nations have died from the virus. The DRC’s deadliest Ebola outbreak on record occurred between 2018 and 2020, when nearly 2,300 people lost their lives to the disease. Just last year, another smaller outbreak in a remote DRC region killed 45 people before it was fully contained.

  • Canadian from hantavirus-hit cruise ship tests positive

    Canadian from hantavirus-hit cruise ship tests positive

    A new presumptive positive case of hantavirus has been detected in a Canadian passenger who traveled on the MV Hondius, the Dutch cruise ship that experienced a deadly viral outbreak among passengers in April, British Columbia provincial health officials announced this week.

    The infected individual, a resident of Yukon who is one of four Canadian passengers currently isolating on Vancouver Island after disembarking from the vessel, has only developed mild symptoms so far, according to provincial authorities. Dr. Bonnie Henry, British Columbia’s senior provincial health officer, confirmed that all four isolating passengers have had zero interactions with members of the general public since they returned to Canadian soil.

    This new case pushes the total number of confirmed hantavirus infections linked to the MV Hondius voyage to 11, with all cases tied to passengers who were on board the trip. To date, three passengers who sailed on the cruise have died, and two of those fatalities have been officially confirmed to be caused by the virus. Dr. Henry noted that the Yukon passenger’s test returned a presumptive positive result on Friday, meaning official confirmation is still pending from Canada’s national microbiology laboratory.

    “Clearly, this is not what we hoped for, but it is what we planned for,” Dr. Henry told reporters, according to comments published by Canada’s national public broadcaster CBC. She went on to clarify key differences between hantavirus and the more widely known respiratory viruses that global health systems have managed in recent years, adding, “I want to emphasise that hantavirus is a very different virus than the other respiratory viruses that we’ve been dealing with – like Covid, like influenza, like measles – and it remains one that we do not consider to have pandemic potential.”

    Of the six Canadian citizens who were on the MV Hondius when the outbreak unfolded, two are currently self-isolating in private homes in Ontario. The remaining four are staying in isolation on Vancouver Island: one couple from British Columbia, and the other couple from Yukon, the group that includes the presumptive positive case. As of the latest update, the other five Canadian passengers have all tested negative for the virus.

    The outbreak began after the cruise set sail from Argentina on 1 April, with early cases of the virus emerging mid-voyage. The ship was held at sea for multiple weeks while global health authorities coordinated a response, and it finally docked in Tenerife, part of Spain’s Canary Islands, earlier this month. All 147 passengers and crew members, who hail from 23 different countries, were allowed to disembark and enter mandatory isolation once the ship reached port.

    On 10 May, all Canadian passengers were flown back to Canada from Tenerife to complete their isolation periods. The World Health Organization currently recommends a 42-day isolation period for anyone exposed to the outbreak. Canadian protocols initially required a 21-day isolation period for returning passengers, but Dr. Henry confirmed that this timeline is now under review and may be extended to align with global guidance.

    Hantaviruses are most commonly carried by wild rodent populations, and human-to-human transmission is rare for most strains. However, the Andes strain of hantavirus — which the WHO has confirmed is the variant that infected at least some passengers during the voyage, which traveled through South America — can spread between humans.

    Common symptoms of hantavirus infection include high fever, extreme exhaustion, body and muscle aches, abdominal pain, vomiting, diarrhea, and difficulty breathing. Canadian public health officials have reiterated that despite the new positive case, the risk of a large community outbreak of hantavirus linked to this cruise remains extremely low.

  • France says cruise ship Andes virus matches known South American viruses

    France says cruise ship Andes virus matches known South American viruses

    PARIS – France’s world-renowned Pasteur Institute has completed full genomic sequencing of the Andes virus isolated from a French passenger who fell ill after a voyage on the MV Hondius cruise ship, and confirmed that the pathogen matches well-documented strains already circulating in South America. As of the latest update, researchers have uncovered no evidence of new genetic traits that would increase the virus’s transmissibility or make it more lethal to humans.

    French Health Minister Stéphanie Rist shared the key findings in a public post on X Friday, emphasizing that the sequenced variant aligns with strains currently tracked by public health systems across South America. “At this stage, no element suggests the emergence” of a more transmissible or dangerous form of the virus, Rist wrote.

    Genomic analysis verified that the virus taken from the French patient is an exact match to samples collected from other infected cases on the same vessel, Pasteur Institute officials confirmed. It also bears a very close genetic resemblance to archived Andes virus samples from endemic regions across South America. All virus samples collected from passengers on the MV Hondius are identical to one another, and carry roughly 97% genetic similarity to known Andes strains circulating in South America, including variants found in rodent populations, the natural reservoir for the virus.

    Jean-Claude Manuguerra, head of the Pasteur Institute’s Environment and Infectious Risk unit, explained that the 3% genetic divergence seen in the sequenced samples falls within the expected range of natural viral variation. The small differences do not appear to alter the core biological characteristics of the virus that affect how it spreads or harms human hosts, he noted.

    The French passenger tested positive for Andes virus following her trip aboard the MV Hondius, and has since received inpatient care at a Paris medical facility. French public health officials previously disclosed that the patient was in serious condition when admitted. Currently, virological investigations remain ongoing, conducted in close collaboration between Pasteur Institute researchers, French national health authorities, and global public health partners. Rist added that the full genomic sequencing data will be shared openly with the international scientific community to support global monitoring and research efforts, noting that the new data will improve understanding of the virus and enable more rigorous ongoing public health surveillance.

  • No vaccine for latest Ebola outbreak, DRC warns as as toll hits 80

    No vaccine for latest Ebola outbreak, DRC warns as as toll hits 80

    The Democratic Republic of the Congo (DRC) is grappling with its 17th recorded Ebola outbreak, marked by a grim rise in fatalities and a troubling lack of targeted medical countermeasures for the rare strain involved. In a press briefing held in Kinshasa on Saturday, DRC Health Minister Samuel-Roger Kamba issued a stark warning about the unfolding crisis: the currently circulating Bundibugyo strain has no approved vaccine or specific antiviral treatment, and carries a mortality rate as high as 50 percent.

    By Saturday, official death counts from the outbreak had climbed to 80, up from the 65 fatalities reported just 24 hours earlier. Health authorities also confirmed the outbreak has already crossed international borders, claiming one life in neighboring Uganda. The victim, a 59-year-old Congolese national, died in Kampala earlier this week after being admitted to hospital, and genetic testing confirmed he was infected with the Bundibugyo strain— a variant first identified in 2007. His remains were repatriated to the DRC the same day he passed away.

    The outbreak, formally confirmed by African health officials on Friday, is centered in DRC’s northeastern Ituri province, which shares borders with both Uganda and South Sudan. Currently available Ebola vaccines only offer protection against the more common Zaire strain, which was first documented in 1976 and carries an even higher fatality rate of 60 to 90 percent.

    Public health experts warn the risk of widespread transmission is particularly high in this region, due to frequent and unregulated cross-border population movement between the DRC, Uganda, and South Sudan. As of Saturday, DRC health authorities reported 246 suspected cases of infection across the affected area. Patient zero, the index case for this outbreak, was a nurse who first sought care at a health facility in Bunia, the capital of Ituri province, on April 24 after developing classic Ebola symptoms: fever, hemorrhaging, and vomiting.

    Speaking on Friday, Jay Bhattacharya, acting director of the U.S. Centers for Disease Control and Prevention, described the event as a large-scale outbreak that demands urgent international attention. This is the first new Ebola outbreak in the DRC since August 2023, when a smaller outbreak in the country’s central region killed 34 people before being declared eradicated in December. The deadliest Ebola outbreak in DRC history, which ran between 2018 and 2020, claimed nearly 2,300 lives.

    First identified nearly 50 years ago, Ebola is a deadly viral hemorrhagic fever that is thought to originate in bat populations. The virus spreads through direct contact with infected bodily fluids or contaminated blood, and infected individuals only become contagious after they begin showing symptoms. The incubation period can last up to 21 days, making contact tracing and outbreak control particularly challenging. According to the World Health Organization (WHO), historical Ebola outbreaks have recorded mortality rates ranging from 25 percent to as high as 90 percent, depending on the strain and access to care. Overall, the virus has killed roughly 15,000 people across Africa over the past five decades, even with recent advances in vaccine and treatment development.

    The WHO has already moved to respond to the crisis, announcing Friday that it is preparing to airlift five tonnes of critical supplies—including personal protective equipment and infection prevention gear—from Kinshasa to the affected region. However, mounting an effective response poses major logistical challenges. The DRC is home to more than 100 million people, covers an area four times the size of France, and suffers from severely underdeveloped transportation and communication infrastructure that slows the movement of personnel and supplies to remote outbreak zones. In its statement, the WHO highlighted the deep uncertainty surrounding the current outbreak’s trajectory, noting: “Given the uncertainties and severity of the illness, there is concern about the scale of transmission in affected communities.”

  • Congolese report constant burials as deaths in new Ebola outbreak reach 80

    Congolese report constant burials as deaths in new Ebola outbreak reach 80

    A new Ebola outbreak in the Democratic Republic of the Congo’s eastern Ituri Province has claimed at least 80 lives, pushing public health authorities into a race against time to scale up border screenings, contact tracing and outbreak containment measures as of Saturday, local officials confirmed.

    Authorities first publicly declared the emergency on Friday, when they initially reported 65 fatalities and 246 suspected cases across affected areas of the province. As of Friday evening, Congolese Health Minister Samuel-Roger Kamba confirmed that eight cases had received positive laboratory confirmation, four of which have resulted in death. Genomic sequencing has identified the pathogen as the Bundibugyo strain, a less common Ebola variant that has not been the primary cause of past large-scale outbreaks in the country. This event marks the 17th Ebola outbreak the country has grappled with since the disease was first detected in Congolese territory in 1976.

    Ebola is an extremely contagious viral pathogen that spreads through direct contact with infected bodily fluids including blood, vomit, and semen. While the disease is classified as rare, it causes severe, acute illness that carries a high fatality rate for most infected patients.

    According to Minister Kamba, health investigators believe the suspected index case, or first patient to trigger the outbreak, was a nurse who died at a Bunia hospital three weeks prior, on April 24. Kamba noted the patient showed classic Ebola symptoms, though he did not confirm whether the nurse’s samples were tested for the virus.

    Local residents in Bunia, the capital of Ituri Province, described a growing climate of fear to Associated Press journalists on the ground, as communities face repeated burials of suspected Ebola victims. “Every day, people are dying … and this has been going on for about a week. In a single day, we bury two, three, or even more people,” said Jean Marc Asimwe, a long-time Bunia resident. “At this point, we don’t really know what kind of disease it is,” Asimwe added.

    The outbreak has already crossed Congo’s northern border, with Ugandan health authorities confirming an imported Ebola case from Congo on Friday. The infected patient died at Kampala’s Kibuli Muslim Hospital on May 14. The Uganda Ministry of Health later confirmed the patient’s remains were returned to Congo for burial, and no secondary locally transmitted cases have been detected in the country to date. As of Saturday, routine health screenings have been activated at the entrance of Kibuli Muslim Hospital to prevent further transmission.

    The Africa Centres for Disease Control and Prevention has issued a statement warning of high risk of further cross-border spread, due to the close proximity of affected Congolese areas to both Uganda and South Sudan. Some regional neighbors have already activated emergency preparedness measures: Kenya, a neighbor of Uganda, announced Saturday that it assesses the current risk of Ebola importation as moderate, driven by frequent regional travel and cross-border movement. In response, the Kenyan government has convened a dedicated Ebola preparedness task force and boosted public health surveillance at all border entry points.

    For many Ugandans, the new outbreak has stirred painful memories of past public health emergencies. “I really get scared because I remember burying my father without looking at his body during the COVID-19 pandemic,” said Kampala resident Ismail Kigongo.

    While the DRC has decades of experience responding to and containing Ebola outbreaks, the response to this latest emergency faces steep structural challenges. The country is the second largest on the African continent by land area, with vast distances between provinces that are frequently disrupted by ongoing armed conflict. Ituri Province, where the outbreak is concentrated, sits roughly 1,000 kilometers (620 miles) from the national capital Kinshasa, and has been ravaged by years of violence from insurgents affiliated with the Islamic State group.

    To date, the outbreak has been confirmed in three Ituri health zones: Bunia, Rwampara, and Mongwalu, with the bulk of cases concentrated in the latter two areas. The National Institute of Biomedical Research has only been able to process 13 blood samples from suspected cases, according to Kamba; eight returned positive for the Bundibugyo strain, while the remaining five could not be analyzed due to insufficient sample volume.

    Despite the growing death toll, daily life in central Bunia remained largely unchanged as of Friday, with businesses open and public activity continuing as normal. Local resident Adeline Awekonimungu called on national authorities to prioritize a rapid, coordinated response. “My recommendation is that the government take this matter seriously and that it takes charge of the hospitals so that this matter can be brought under control,” she said.

    Reporting for this article included contributions from Associated Press journalists Chinedu Asadu based in Abuja, Nigeria; Patrick Onen in Kampala, Uganda; and Evelyne Musambi in Nairobi, Kenya.

  • What is a ‘safe death’? Mentally ill woman asks for assisted dying in Canada

    What is a ‘safe death’? Mentally ill woman asks for assisted dying in Canada

    For nearly 30 years, 49-year-old Toronto-based performer Claire Brosseau has navigated a devastating path of severe, treatment-resistant bipolar disorder and post-traumatic stress disorder (PTSD). A veteran stand-up comedian and actor who has worked across film, television, and theatre worldwide, Brosseau says she has tried every available intervention for her conditions—from talk therapy and pharmaceutical interventions to electroconvulsive brain stimulation. None have brought relief. Today, she is unable to work, leave her home unaccompanied, or maintain consistent connection with her loved ones, describing her own condition as “functionally terminal.” Now, she is at the center of a high-stakes national debate over whether Canada should expand its existing legal medically assisted dying (MAID) framework to include people whose only qualifying condition is untreatable mental illness.

    Currently, MAID is legal in Canada for patients with terminal illnesses and irreversible serious physical disabilities, but it explicitly excludes those whose sole diagnosis is mental illness. Brosseau, who has lived with debilitating mental illness since adolescence and received psychiatric care in four major North American cities over three decades, is now asking an Ontario court for a special exemption to access MAID immediately, arguing that the existing law is discriminatory and unconstitutional. She says she wakes every day consumed by overwhelming dread and crippling anxiety, and she wants a peaceful, controlled death rather than being forced to die by suicide.

    “Stigma is at the root of this exclusion,” Brosseau explained in an interview with the BBC. “If I were diagnosed with terminal cancer tomorrow, I would be immediately eligible for MAID even if I chose to stop treatment. But people like me, living with unbearable, incurable mental suffering, are denied the same right that is already a standard part of Canadian healthcare. I am not asking for special treatment—only equal treatment.”

    Canada first approved MAID for terminally ill patients in 2016, and expanded it to include non-terminal patients with irreversible serious medical conditions five years ago, following a successful legal challenge by disability advocates. The federal government had initially planned to extend eligibility to patients with treatment-resistant mental illness by 2024, but has twice delayed the expansion, most recently pushing any decision to 2026, amid widespread concerns that the Canadian healthcare system lacks the infrastructure, training, and regulatory frameworks to safely implement the change. Prime Minister Mark Carney has confirmed he will not make a decision until he receives the final recommendations from a joint parliamentary committee tasked with reviewing the proposed expansion. “I will base my position on the full evidence presented to the committee,” Carney told reporters recently.

    Over two months of hearings, the cross-party committee heard conflicting testimony from medical experts, disability advocates, and international commentators that laid bare the deep divides on this issue. Critics of expansion argue that expanding MAID to mentally ill patients risks turning assisted dying into a substitute for inadequate social and medical support. They point to reports of Canadian healthcare providers offering MAID to disabled patients who never requested it, arguing that systemic gaps in affordable housing, disability support, and specialized mental healthcare leave many vulnerable people with no other option to end unaddressed suffering. “We are currently investing in ending lives instead of investing in improving lives,” said Krista Orr, president of national disability advocacy group Inclusion Canada, who called on the committee not just to reject expansion but to roll MAID back to only terminal illness cases.

    Other critics warn that medical science still lacks a full understanding of many severe mental illnesses, making it impossible to definitively distinguish between temporary suicidal ideation and irreversible, untreatable suffering. Dr. Sonu Gaind, former chief of psychiatry at a major Toronto hospital, told the committee that none of the core safeguards and assessment questions have been resolved since the expansion was paused. “We now have even more evidence that we are not prepared to safely offer MAID for mental illness,” Gaind said.

    International experience, particularly from the Netherlands—one of the only countries that already allows MAID for patients suffering solely from mental illness—has added fuel to both sides of the debate. The Netherlands requires all patients seeking MAID for psychiatric reasons to undergo a full assessment by a qualified psychiatrist, and approvals for these cases remain relatively rare, accounting for only 2% of all assisted deaths in the country. However, the number of approved cases has skyrocketed from just 2 in 2010 to 219 in 2024. Dutch psychiatrist Dr. Jim van Os warned Canadian lawmakers that this growing trend reflects what he calls a “suicide contagion effect,” arguing the Dutch experience is a clear warning for Canada. But fellow Dutch psychiatrist Dr. Sisco Van Veen pushed back, noting that approved cases remain rare and MAID provides critical mercy to patients whose suffering is unbearable and untreatable.

    The committee itself has faced accusations of bias from supporters of expansion. Brosseau says she requested to testify before the committee multiple times but was denied a spot. One sitting member, Alberta Senator Kristopher Wells, has publicly called the review “one-sided” and says he has no confidence in the final report. Committee co-chairs Marcus Powlowski, a Liberal MP, and Conservative Senator Yonah Martin—both of whom have publicly opposed expanding MAID to mental illness—defended the process in statements, noting that limited hearing time meant prioritizing testimony from medical professionals and industry associations, and adding that the committee has “dutifully listened to both sides” of the debate. The committee’s final report is not expected to be delivered to parliament until as late as October 2025.

    For Brosseau, who says her condition is worsening by the month and cannot wait for years of parliamentary review, the delay is a matter of life and death. Confined to her home, with even short trips to the local grocery store triggering crippling panic attacks, she says her legal challenge is not a campaign for death—it is a fight for equal human rights. “I’m not campaigning for death. I’m campaigning to be seen as not a subsection of human,” she said. “We deserve the same autonomy over our bodies and our suffering that people with physical illness already have.”

    Public opinion polling shows a majority of Canadians support broad access to medically assisted dying, but public opinion becomes far more divided when the question is limited to mental illness. Currently, 96% of MAID approvals in Canada go to patients with reasonably foreseeable death, mostly terminal cancer patients, with only 4% going to non-terminal patients with irreversible serious conditions. As the country waits for the committee’s final recommendation, Brosseau’s legal case is pushing the judiciary to address a gap in the law that the federal government has so far been unwilling to fill.