分类: health

  • Restoring dignity one haircut at a time in Kenya’s largest mental health hospital

    Restoring dignity one haircut at a time in Kenya’s largest mental health hospital

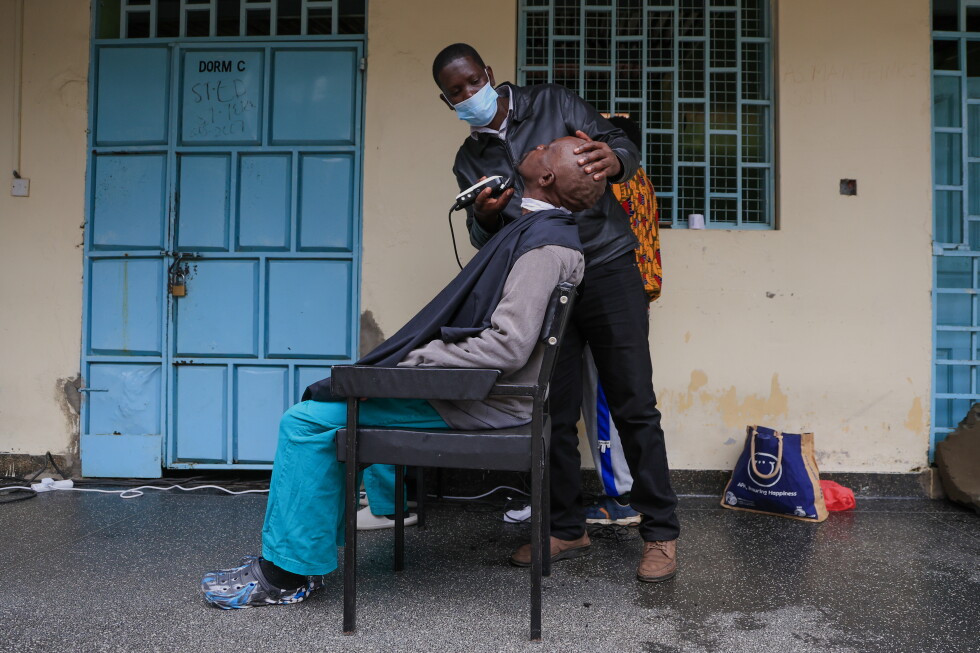
    At Mathari National Teaching and Referral Hospital, Kenya’s largest facility for specialized mental health care, a unique, community-led therapy program is transforming the recovery journey for male patients: monthly free personal grooming sessions delivered by volunteer barbers. As soon as barbers lay out their clippers, scissors and shaving supplies, a palpable wave of excitement moves through the waiting group of patients. One by one, men take their seat in the temporary barber chair, eager to walk away with a fresh cut and clean shave that many have not had in months.

    Healthcare providers at the facility explain that targeted self-care interventions like this fill a critical gap in standard mental health treatment. A common, widely overlooked symptom of many mental health conditions—particularly depression, which is one of the most prevalent mental health disorders in Kenya—is a gradual loss of motivation to maintain personal hygiene and physical appearance. For patients struggling with severe mental illness, this neglect can quickly spiral into lower self-worth, deeper social isolation, and slower progress toward recovery.

    Kenya’s mental health care system still faces major gaps in data and infrastructure, with limited national tracking of mental illness prevalence. The most recent official government policy framework, released in the 2015 National Mental Health Policy, estimates that 25% of all outpatient care attendees and 40% of inpatient admissions across Kenyan health facilities live with a diagnosable mental health condition. Mental health practitioners note that mood disorders like depression and anxiety top the list of most commonly diagnosed conditions, while substance use disorders remain an especially persistent and widespread challenge among male patients.

    The initiative comes as June marks global Men’s Mental Health Awareness Month, a moment that local health workers are leveraging to encourage a cultural shift in how Kenyan men address mental health struggles. Francis Kabugua, a senior nursing officer at Mathari Hospital, stresses that harmful cultural expectations of emotional stoicism often push men to cope with distress through harmful coping mechanisms rather than open discussion. “Many men with progressive depressive disorders start to withdraw from their families, step back from their responsibilities, and isolate themselves entirely,” Kabugua explained. Too often, instead of seeking professional support, they turn to alcohol and drugs to numb their symptoms, worsening their condition over time.

    The free grooming program is run by Uniquely Gifted, a community-based organization founded by Sheila Lugaliki, who drew on her own personal experience receiving inpatient psychiatric care to launch the monthly initiative. “I saw firsthand what it feels like to be hospitalized for months without anyone helping you care for your appearance, and how that makes you feel invisible and neglected,” Lugaliki said. She designed the program not just as a practical service, but as a gesture of human connection: the simple act of a haircut is intended to restore patients’ sense of dignity, rebuild their confidence, and remind them that they are seen and valued members of the community. “When someone has been admitted for half a year and no one has trimmed their hair, their outward appearance doesn’t just reflect neglect—it deepens the negative feelings they already have about themselves,” she added.

    Titus Enko, a psychiatric nurse at Mathari Hospital, echoes this perspective, noting that personal care is often sidelined in treatment plans that prioritize medication and traditional talk therapy. “We focus so much on clinical interventions that we forget the small, tangible acts of care that signal recovery. When a patient starts caring about how they look, that’s a clear sign they are starting to feel better about themselves,” Enko explained. “Personal grooming builds self-esteem, and that boost in self-worth directly supports long-term recovery and overall well-being.”

    By the end of the latest grooming session, as barbers finished trimming beards and cleaning up necks, one patient summarized the impact of the program in one simple, powerful word: he said he felt “alive.”

  • DR Congo bans mass gatherings in the  capital to prevent spread of Ebola

    DR Congo bans mass gatherings in the capital to prevent spread of Ebola

    The Democratic Republic of Congo (DRC) has implemented a sweeping ban on mass gatherings in its capital city Kinshasa and four neighboring provinces, a public health measure aimed at stopping the fast-spreading Ebola outbreak from reaching one of Africa’s most densely populated urban centers, the country’s interior minister has announced.

    As of Saturday, when the new directive was issued, the deadly viral outbreak has been officially confirmed in three eastern DRC provinces — Ituri, North Kivu, and South Kivu — located roughly 1,800 kilometers (1,100 miles) from Kinshasa, a megacity home to 18 million residents. The ban extends beyond Kinshasa to three additional eastern provinces that share borders with the affected regions: Tshopo, Haut-Uele, and Bas-Uele. Mass gathering restrictions have already been in place in the three core affected provinces for weeks, with Ituri bearing the overwhelming brunt of the crisis, accounting for more than 90% of all recorded infections.

    On the day the new ban was announced, health authorities recorded a single-day jump of 47 new confirmed cases, pushing the national total of infections to 1,274, with the confirmed death toll rising to 360. Neighboring Uganda has also detected cross-border spread of the virus, with 20 confirmed infections and two recorded deaths, according to the World Health Organization (WHO).

    This outbreak is unusual in that it is caused by the Bundibugyo strain of Ebola, for which no widely approved vaccine currently exists. Public health bodies including Africa’s Centres for Disease Control and Prevention (Africa CDC) and U.S. health agencies have warned that the outbreak has the potential to become one of the largest on record, because transmission went undetected for several weeks before the virus was formally identified. Ongoing armed conflict in eastern DRC, where the M23 rebel group controls large swathes of North and South Kivu, has further complicated outbreak response efforts, the WHO added.

    The implementation of the ban has already sparked political controversy, with major opposition figures arguing the restriction is a deliberate attempt to block a planned opposition protest scheduled for July 8. The demonstration is organized by the C64 coalition, an opposition alliance opposing a proposed new law that critics warn would allow current President Felix Tshisekedi to extend his time in office beyond the constitutional two-term limit.

    Opposition leaders point out that no Ebola cases have yet been confirmed in Kinshasa, making the public health justification for the ban unconvincing. Prince Epenge, spokesperson for the opposition Lamuka coalition, called the government’s decision an overtly political move. “It is not legitimate. We cannot accept this decision,” Epenge told the BBC Monday. Rodrigue Ramazani, secretary-general of the opposition Envol party, echoed those criticisms, saying the directive “reeks of a political manoeuvre rather than a public health measure,” and urged planned protesters to defy the ban and attend the march. As of Tuesday, the Congolese government has not issued any public response to the opposition’s allegations.

    While Kinshasa has no confirmed local cases to date, the city has been linked to a recent exported case: a doctor who worked at an Ebola treatment center in the outbreak’s epicenter passed through Kinshasa while traveling home to France, where he later tested positive for the virus. Shortly after the doctor’s positive test was announced, the DRC government implemented a 21-day quarantine mandate for all travelers moving from affected provinces to other parts of the country.

  • To beat China in the lab, America’s edge is trust not speed

    To beat China in the lab, America’s edge is trust not speed

    As geopolitical competition increasingly extends into the life sciences sector, the United States faces growing anxiety over China’s rapid ascent in global clinical drug research. While this concern is grounded in tangible data, framing reform of U.S. clinical trial systems as a zero-sum race risks overlooking a far more impactful goal: building a faster, safer, globally trusted model for medical innovation that benefits patients worldwide.

    At the center of U.S. reform efforts is a new pilot program launched by the U.S. Food and Drug Administration (FDA), part of a broader initiative led by the Department of Health and Human Services. The program is designed to cut red tape for early-stage clinical trials, with projections that it could shorten overall drug development timelines by 6 to 12 months. This move comes in response to a clear, ongoing industry shift: a growing share of early-stage drug research has relocated outside U.S. borders, drawn to destinations ranging from China to Australia by lower operational costs, streamlined regulatory approval processes, targeted tax incentives and more efficient clinical trial networks.

    The data behind U.S. policymakers’ concerns is stark. Federal officials confirm that China now conducts more clinical drug trials than the United States, and one 2024 estimate places China’s share of all global trials at 39 percent. This shift is far from trivial: early-stage trials are not just routine technical procedures, they are the foundational gateway to global biomedical innovation. The geographic location of these trials shapes which patient populations gain early access to cutting-edge therapies, which academic and medical institutions build specialized research expertise, where billions in global life sciences investment flows, and which nations’ regulatory frameworks ultimately set the global standard for drug development.

    Despite this shifting landscape, the central question facing U.S. leaders is not whether the country can “outcompete” China on trial volume alone. Instead, it is whether the U.S. can restructure its system to be fast enough to retain and attract global research investment, rigorous enough to protect trial participants, and transparent enough to produce clinical evidence that the entire world can rely on.

    The FDA’s proposed regulatory reforms move toward this goal. Under the new framework, the agency will provide pharmaceutical companies with earlier clarity on manufacturing requirements, dose selection and approval pathways, and will offer rolling review of some applications, allowing sponsors to submit materials incrementally rather than waiting to compile a full complete dossier before review begins. The FDA has also reaffirmed a new flexible approach: in select cases, a single high-quality late-stage trial, supported by robust confirmatory evidence, will be sufficient to support drug approval, replacing the longstanding requirement for two separate positive late-stage trials.

    Other federal agencies are joining the push for reform. The National Institutes of Health is set to explore innovative trial designs, integrate artificial intelligence and real-world patient data into research processes, and streamline the slow, fragmented ethics review process. Federal health technology officials are also working to break down data silos, exploring how interoperable electronic health record systems can connect more diverse patient populations to research studies.

    These steps are rooted in a clear diagnosis of U.S. system weaknesses. The American regulatory framework is not slow because regulators oppose innovation. Rather, friction accumulates across a series of disconnected stages: trial activation, contracting, ethics review, site selection, patient recruitment, data collection and communication between sponsors and regulators all operate as separate, uncoordinated layers. While each step was designed to serve a valid purpose, their cumulative effect creates costly delays that drive research activity overseas.

    Yet the reform effort carries a key risk: if speed becomes the only overriding goal, the U.S. could trade its greatest advantage for marginal gains. If faster trials come at the cost of thinner clinical evidence, weaker patient oversight or pressure to rush enrollment to meet arbitrary timelines, the U.S. will not strengthen its global position—it will erode public trust that takes decades to build, and is far harder to recover than a compressed regulatory timeline.

    When assessing China’s rise in clinical research, nuance is critical. China’s growth is not solely the result of subsidies and loose regulation. It reflects decades of deliberate, strategic investment: building dense, coordinated hospital research networks, leveraging its large diverse patient population, cultivating a growing pool of top scientific talent, and aligning industrial policy with public health goals to drive research growth. The U.S. would benefit from studying these strengths honestly rather than relying on caricature; learning from a competitor is not surrender, it is a mark of strategic maturity.

    At the same time, the U.S.’s enduring core advantage has never been primarily speed—it is credibility. FDA approval decisions carry global influence precisely because, for all its imperfections, the agency is widely viewed as methodologically rigorous and comparatively transparent. Instead of copying other nations’ models, the U.S. should anchor its competitive strategy in trust, building a reformed system that prioritizes both speed and credibility.

    One actionable step to achieve this is the creation of a national network of pre-certified “trial-ready” research sites. Rather than treating every study as a one-off project requiring new contracting, ethics review and data standardization from scratch, the government could certify standing research networks that already have master contracts, pre-agreed data standards, robust privacy safeguards, community engagement frameworks and shared centralized ethics review. Sponsors could connect to these networks far faster, and patients and providers would have clear visibility into which sites meet consistent quality benchmarks.

    A second key reform is expanding access to trials beyond major urban elite academic centers, reducing geographic barriers to participation. When patients must travel repeatedly to specialized research centers for trial visits, enrollment remains slow and unequal, excluding large swathes of diverse patient populations. A more practical, accessible model would integrate more trial activities into routine patient care, supported by interoperable electronic health records and strengthened local research networks. This would shift clinical trials from rare, exclusionary events to a normal, accessible part of healthcare for more patients.

    Policymakers also need to distinguish between two distinct forms of speed. Regulatory speed refers to shorter approval queues and clearer, earlier guidance for sponsors—this primarily benefits pharmaceutical companies by cutting development timelines and costs. Evidence speed, by contrast, refers to generating reliable clinical evidence faster through smarter trial designs, improved outcome measures, interoperable data systems, and earlier detection of treatment benefits and harms—this primarily benefits patients. A meaningful, durable reform agenda requires prioritizing both.

    For the broader Asia-Pacific region, the stakes of this reform extend far beyond the U.S.-China bilateral competition. If the U.S. succeeds in pulling large volumes of trials back to domestic sites, regional research centers across Asia could face heightened competition for global investment. But a far better outcome is within reach: a global clinical research ecosystem that is more distributed, interoperable across trusted regulatory jurisdictions, rather than splitting into rival geopolitical blocs. Regulators can compete on quality and efficiency while cooperating on core shared priorities: data integrity, patient protection and universal transparency.

    This collaborative model would benefit all nations: China has a clear stake in building global trust in its research output, the U.S. benefits from learning from efficient systems abroad, and patients everywhere gain faster access to therapies that have been rigorously proven safe and effective, rather than just heavily marketed.

    By this standard, the FDA’s new pilot initiative should be judged against three core tests. First, does it cut unnecessary bureaucracy without lowering standards for clinical evidence? Second, does it expand access to trial participation beyond elite academic centers and large urban hospitals? Third, does it produce transparent, reproducible evidence that other nations can examine, verify and trust?

    If the reforms pass these tests, the U.S. will do more than recapture market share in global clinical trial volume. It will redefine what global leadership in biomedical innovation actually means. In an era of intensifying great power competition, the most successful nation will not be the one that turns scientific research into another geopolitical battlefield. It will be the one that proves speed and public trust can advance together, for the benefit of patients across the world.

    This analysis comes from Y. Tony Yang, an endowed professor at George Washington University in Washington, D.C.

  • Europe’s record heat has overwhelmed Paris mortuaries and left families in distress

    Europe’s record heat has overwhelmed Paris mortuaries and left families in distress

    PARIS (AP) — For mortuary owner Zouhaeir Hertelli, business has taken an unthinkable turn amid Europe’s record-shattering 2022 heat wave: every few minutes, his phone buzzes with a desperate question from funeral directors and grieving families alike: do you have any cold storage space left for another body?

    With all 32 spots in his refrigerated mortuary already occupied, Hertelli has been forced to turn away hundreds of families, repeating the devastating word “No” again and again. “We’re facing a really catastrophic situation,” he told reporters. “I’m getting hundreds of calls.”

    As the blistering heat dome drifted eastward across Europe over the weekend, leaving a trail of fatalities in its wake, France has begun the grim work of counting the human cost of the extreme temperatures that first settled over the country in mid-June.

    Full official mortality counts will take weeks or months to compile, as public health teams cross-reference death certificates and verify heat as a contributing cause. But even the earliest data makes clear the unprecedented toll of this unrelenting heat event, which has hit older and isolated populations particularly hard.

    France’s national public health agency released its first preliminary assessment of the crisis, confirming a dramatic spike in deaths during the heat wave’s peak last week. Temperatures soared above 40 degrees Celsius (104 degrees Fahrenheit) across most of the country, and record-breaking overnight highs left vulnerable bodies with no chance to cool down and recover — a deadly one-two punch that overwhelmed natural defenses.

    On the nation’s all-time hottest day, which broke a record set just 24 hours earlier, more than 1,200 deaths were recorded across France. That number climbed to more than 1,400 the following day, and stayed at that elevated level on the third day of peak heat. For comparison, the average daily death toll in April and May 2022, before the heat wave arrived, ranged between 900 and 1,000.

    The agency estimates that at least 1,000 excess deaths occurred over just those three days, but warns the final toll will be higher. Many deaths occurred in private homes and elderly care facilities, where death registrations are often processed manually rather than electronically, leading to delays in official counting. “Mortality will as a consequence be higher than these first figures,” the agency stated.

    Eighty-five percent of the deaths registered so far from the three-day peak are people aged 65 and older, and deaths at home have jumped by roughly 40% compared to pre-heat wave levels, with the Paris region seeing the sharpest increase.

    Hertelli and other funeral industry professionals across the capital report that all municipal and private mortuary cold storage filled within days of the heat peak. Paris City Hall has responded by installing two temporary cold storage units with 20 spots each at municipal mortuaries, and local hospitals have made an additional 50 spaces available.

    Even with the extra capacity, the shortage remains acute. Hertelli says funeral directors he has spoken with are transporting bodies as far as Chartres, 50 miles southwest of Paris, to find available storage. He has submitted a request to local authorities for permission to park temporary refrigerated shipping containers outside his mortuary, located near Paris Orly Airport, but has not yet received approval. “Families are suffering,” he said. “We have no solution to offer them, because the funeral homes are full. So we are deeply affected, we have empathy for them, but there’s nothing we can offer. We are really facing a problem, a big problem.”

    This heat wave has already surpassed the 2003 European heat event that killed an estimated 15,000 people in France and sparked a national reckoning over the care of vulnerable elderly populations. A 2021 heat wave also killed more than 5,700 people across the country. Many funeral and public health professionals worry that the hard-won lessons of past heat crises have been forgotten as record heat becomes more common.

    Véronique Bertrand, a funeral director based in Paris, notes that most of the recent fatalities she has handled were isolated seniors who lived alone at home. “Given the circumstances in which they were found, there can be no other conclusion than that these were deaths caused by the heat,” she said.

    Bertrand called for a renewal of the community solidarity that emerged after the 2003 tragedy, when neighbors began checking in on isolated older residents to ensure they were staying hydrated and cool. “I think people absolutely need to wake up, that solidarity needs to come back, that what happened in 2003 led to a movement in that direction, with people thinking about their neighbors, of those around them who live alone and perhaps checking from time to time that they’re drinking water and are being looked after,” she said. “With the passing years, we’ve perhaps forgotten that it could happen again and that things would even perhaps be worse.”

  • China-Zimbabwe health partnership delivers new hope to patients

    China-Zimbabwe health partnership delivers new hope to patients

    Across Zimbabwe, thousands of people living with chronic pain, life-threatening acute conditions, and treatment-resistant illnesses are finding new hope through a decades-long health partnership between China and Zimbabwe, centered on expanding access to both traditional Chinese medicine (TCM) and cutting-edge modern medical technologies.

    At the Zimbabwe-China Traditional Chinese Medicine and Acupuncture Center based at Harare’s Parirenyatwa Group of Hospitals, the nation’s top public referral institution, the 10-member 23rd Chinese medical team has built a reputation for life-saving care and transformative treatment. Led by Ma Zheng, a public health specialist from China’s Hunan Provincial Center for Disease Control and Prevention, the team draws on cross-disciplinary expertise from leading Hunan hospitals to treat an average of 30 patients daily, combining TCM practices with modern critical care techniques.

    Stories of dramatic recoveries have spread far beyond Harare’s city limits, drawing patients from hundreds of kilometers across all 10 of Zimbabwe’s provinces, many traveling for more than six hours to access care the center provides. One of the team’s most notable achievements involved rescuing an elderly HIV-positive patient who had developed multiple organ failure stemming from acute heart failure and cardiogenic shock. Local clinicians had been unable to secure venous access after the patient’s peripheral veins collapsed from widespread swelling, but coordinated multidisciplinary emergency intervention from the Chinese team stabilized the patient and pulled him back from the brink of death.

    In another high-stakes case, the team rapidly treated a patient with an acute ischemic stroke within the critical 4.5-hour window that determines long-term outcomes, preventing permanent disability and adding another success story to the growing list of results that have built public trust in Chinese medical expertise among Zimbabweans.

    For patients living with chronic pain that has resisted conventional Zimbabwean healthcare treatments, TCM practices including acupuncture, cupping, moxibustion, massage, and herbal medicine have delivered life-changing relief. Revayi Roselinah Chaitezvi, a Chitungwiza resident who lived with disabling back pain for five years, saw her symptoms subside dramatically after just three acupuncture sessions. For 27-year-old Jomarie Nhari, persistent shoulder pain and muscle strain that failed to respond to expensive conventional physiotherapy also improved dramatically after acupuncture, exceeding all her expectations. Sixty-one-year-old Ivy Gundam, who lives with high blood pressure and chronic knee pain, now says acupuncture has let her regain control of her daily life after years of being limited by discomfort.

    Beyond direct patient care, the partnership is driving long-term progress for Zimbabwe’s entire healthcare system. The Chinese team has introduced advanced neuromodulation technologies—including deep brain stimulation and spinal cord stimulation—for the first time in the country, allowing local clinicians to treat Parkinson’s disease, severe neuralgia, and spinal cord injuries that once required patients to travel abroad for costly care. The team also plans to roll out affordable, easy-to-use rapid multiplex detection testing that can screen for HIV, syphilis, and hepatitis B in a single test, a tool ideal for grassroots community outreach. Regular training programs for local doctors and nurses are also building local capacity to diagnose and manage infectious diseases, creating sustainable skills that extend beyond the team’s deployment.

    The work of the medical team has also inspired a new generation of Zimbabwean healthcare workers to carry TCM practice forward across the country. Charlotte Muziri, a former Miss Zimbabwe Queen and University of Zimbabwe graduate, first connected with the team when her father had a stroke in 2017, and the successful treatment restored hope to her entire family. Today, she volunteers as a trainee at the center and plans to pursue advanced medical studies in China. Munashe Mboneka, one of Zimbabwe’s first locally trained TCM practitioners, completed specialized training in Hunan province in 2022 and now works full-time at the center, where patient demand consistently outstrips available capacity. “The Chinese doctors have become a beacon of hope for Zimbabweans who had exhausted other treatment options,” Mboneka said.

    In addition to fixed care at the Harare center, the team regularly hosts mobile outreach camps across remote rural communities, providing free consultations, acupuncture treatment, disease screening, and health education to thousands of people who would otherwise lack access to these services.

    This current chapter of collaboration builds on a health partnership that stretches back more than 40 years. China first sent medical teams to Zimbabwe in 1985, and has since supported the construction of major public healthcare facilities including Chinhoyi Provincial Hospital and the Mahusekwa China-Zimbabwe Friendship Hospital. Today, the partnership’s impact is measured not just in infrastructure and technology transfer, but in the thousands of lives saved, chronic pain relieved, and hope restored for Zimbabweans who had nowhere else to turn for care.

  • How Aussies taught kids to stay safe in the sun

    How Aussies taught kids to stay safe in the sun

    Skin cancer has long been one of the most pressing public health challenges for sun-drenched nations like Australia, where high ultraviolet radiation levels put residents at constant elevated risk. Four decades ago, public health officials made a pivotal decision to tackle this crisis from the ground up, focusing on the youngest generation to build lifelong safe sun habits. In 1981, they launched a revolutionary nationwide public education campaign that swapped dense clinical messaging for approachable, memorable pop culture-style content to teach children how to protect themselves from harmful sun exposure.

    The centerpiece of this innovative campaign was Sid the Seagull, a cheerful yellow cartoon character paired with an upbeat, catchy jingle that quickly embedded itself in the national consciousness. Unlike traditional public health announcements that relied on dry warnings and statistics, the campaign framed sun safety as a simple, everyday habit children could easily adopt. By leveraging a beloved cartoon mascot and an easily recallable tune, public health experts made core lessons about seeking shade, wearing protective clothing, and applying sunscreen stick with kids far more effectively than any textbook or lecture could.

    Decades later, this pioneering initiative is still held up as a global model for community-focused public health education. What began as a single national campaign to reduce rising skin cancer rates has reshaped how countries around the world approach sun safety outreach, proving that accessible, engaging messaging targeted at children can create generational shifts in health behavior.

  • France confirms first Ebola case

    France confirms first Ebola case

    In a development that marks the first confirmed Ebola case on European soil, France has announced that a doctor returning from a humanitarian deployment in the Democratic Republic of the Congo (DRC) has tested positive for the deadly virus. The French Ministry of Health disclosed Wednesday that the infected medic was promptly isolated and admitted to a specialized treatment facility, where the patient currently remains in stable condition. The outbreak currently ravaging eastern DRC was formally declared by public health authorities last month, but epidemiologists have confirmed the virus had been quietly spreading in local communities for several weeks prior to the official announcement.

    As of the latest updates, the outbreak has already claimed more than 260 lives across the central African nation, with over 1,000 confirmed total infections. While this is the first confirmed Ebola case detected in Europe, an American healthcare worker who tested positive in DRC was transported to Germany for care just last month. Cross-border spread has already reached neighboring Uganda, where the World Health Organization (WHO) has documented 20 confirmed infections and two recorded deaths.

    Public health officials have moved quickly to reassure the general public that broad population risk remains minimal. French authorities emphasized the overall risk to French citizens is “very low”, a sentiment echoed by WHO Director-General Tedros Adhanom Ghebreyesus, who stated global risk remains low and there is no justification for widespread public panic. Contact tracing operations are currently active to identify and monitor all individuals who may have had close exposure to the infected French doctor.

    Healthcare workers on the frontlines of the outbreak response face disproportionately high danger, as Ebola spreads through direct contact with infected bodily fluids. Last week, WHO data revealed 17 out of 75 healthcare workers who contracted the virus in DRC have died from their infections. A complicating factor in this outbreak is that it is driven by the Bundibugyo strain of Ebola, for which no widely approved vaccine currently exists.

    In response to the imported case, France has activated a dedicated monitoring system to track all aid and humanitarian workers returning from DRC. Both the Africa Centres for Disease Control and Prevention (Africa CDC) and United States public health agencies have warned that the ongoing outbreak has the potential to become one of the largest Ebola events on record if containment efforts are not scaled up rapidly.

    Confirmed cases in DRC are currently concentrated in three eastern provinces: Ituri, North Kivu, and South Kivu. Ituri remains the epicenter of transmission, accounting for more than 90 percent of all confirmed infections. Persistent armed conflict in the region has severely hampered outbreak response efforts, according to WHO. The M23 rebel group maintains control over large swathes of both North and South Kivu, making it difficult for response teams to access affected communities, conduct surveillance, and deliver care to infected patients.

  • French health ministry confirms Ebola virus in patient who worked in Congo

    French health ministry confirms Ebola virus in patient who worked in Congo

    On Wednesday, French health authorities announced the country’s first confirmed Ebola case linked to the ongoing outbreak in the Democratic Republic of Congo, marking a worrying cross-border spread of the currently untreatable virus. The unnamed patient, who had just completed a humanitarian deployment in one of Congo’s active Ebola transmission zones, was quickly taken into specialized medical care immediately after entering French territory.

    According to the French Ministry of Health, the patient is currently in stable condition, and all required infection control protocols were activated from the moment the case was flagged. Strict isolation protocols were implemented, and the patient was transported to a specialized treatment facility via secure pathways designed to eliminate any risk of community contamination. Public health teams have also launched a full epidemiological investigation to track down every person who may have had close contact with the infected individual. All identified contacts will be placed under 21-day at-home isolation, a period matching the virus’s maximum incubation window, and monitored closely for any early symptoms of infection.

    The case comes as Congo grapples with a growing public health crisis that has so far recorded 1,094 confirmed Ebola infections and 277 confirmed deaths, according to Congolese health ministry data. What makes this outbreak particularly dangerous is that it is caused by the rare Bundibugyo Ebola strain, for which no approved vaccines or specific antiviral treatments currently exist.

    Outbreak officials have warned that the true caseload is likely much higher than official counts, as many infections in remote affected areas remain undetected. Since the outbreak was first officially declared on May 15, transmission has continued to accelerate, and experts caution that the worst of the crisis is still ahead. This imported case in France underscores the ongoing global risk posed by unmanaged Ebola outbreaks in central Africa, even as wealthy nations maintain robust systems to contain the virus after it crosses their borders.

  • Kenya minister found in contempt of court over US-backed Ebola centre

    Kenya minister found in contempt of court over US-backed Ebola centre

    In a high-profile legal ruling that has amplified tensions around a controversial public health project, Kenya’s Health Minister Aden Duale has been convicted of contempt of court for violating a court order to halt construction on a US-funded Ebola quarantine facility in Nanyuki.

    Last month, Kenya’s High Court issued an immediate stop-work order for the 50-bed isolation center, which is planned to be built on a local military base. The order paused all construction until the court could hear a legal challenge brought by Kenyan rights organization the Katiba Institute. But in Monday’s ruling, Justice Patricia Nyaundi confirmed that Duale had deliberately ignored the court’s command and permitted construction work to continue uninterrupted. Sentencing for Duale is scheduled to be handed down on Tuesday.

    The facility, funded through a US regional Ebola response package, is designed to quarantine US citizens suspected of exposure to Ebola during the ongoing outbreak centered in the eastern Democratic Republic of Congo. The project has sparked widespread public outrage and mass protests across Nanyuki, a town located roughly 140 kilometers north of Kenya’s capital Nairobi. Three people have been killed during clashes between demonstrators and police, who were deployed to disperse the crowds. Among the fatalities is 17-year-old high school student Sylvester Muigai Ndung’u, who had hoped to train as a Catholic priest. Witnesses report the teenager was shot in the head during the unrest, though police have stated they are waiting for post-mortem results to confirm the cause of his death, and have not yet responded to accusations that officers used excessive force against unarmed civilians.

    The Katiba Institute first filed its legal challenge to halt construction in May, warning in its petition that the facility poses “grave and imminent risks” to Kenyan public health. Following the stop-work order, Kenya’s Ministry of Health attempted to defend its actions by claiming it had not violated the court’s ruling. The ministry argued any ongoing work was being carried out independently by the Kenyan government, in the national interest of protecting Kenyan citizens from potential Ebola exposure. Justice Nyaundi rejected this justification outright in her ruling, stating the government cannot “avoid compliance by recasting or re-characterising the ongoing construction”. She emphasized that a court order “is not an invitation to ingenuity – it is a command to be obeyed”, and confirmed Duale clearly understood the requirement to stop all work at the Nanyuki site, yet chose to allow construction to proceed.

    In recent weeks, Kenyan President William Ruto has publicly defended the quarantine facility project. Ruto stated he received an official request from the US government to host the center, and argued that turning down the request would be “inhuman”. He has also urged Kenyan politicians not to politicize the Ebola response, calling for an end to “reckless” rhetoric around the project.

    As of Monday, Kenya had not recorded any confirmed cases of Ebola. The ongoing outbreak is concentrated in the Democratic Republic of Congo, where more than 1,000 confirmed cases have been recorded, with an additional 20 confirmed cases reported in neighboring Uganda, nearly all of which are imported from DR Congo. Notably, the outbreak epicenter in Bunia, DR Congo is more than 780 kilometers from Nanyuki, with Uganda lying between the two locations.

    The project has also faced fierce pushback from the Kenya Medical Practitioners, Pharmacists and Dentists Union (KMPDU), one of the country’s largest medical professional associations. Union leaders have publicly questioned why Kenya was selected to host a quarantine facility for exposed American workers, amid an outbreak centered hundreds of kilometers away in another country. KMPDU Secretary General Davji Bhimji Atellah stated the union “will not sit back and watch Kenya be treated as a containment colony for a lethal pathogen that we did not generate”.

    A spokesperson for US Secretary of State Marco Rubio confirmed that Washington has committed $13.5 million (£10.7 million) to fund Kenyan Ebola preparedness initiatives, including the Nanyuki facility. That funding is part of a broader $112 million US commitment to support regional Ebola outbreak response across Central and East Africa.

  • DR Congo Ebola cases top 1,000

    DR Congo Ebola cases top 1,000

    KINSHASA, June 22 — Health authorities in the Democratic Republic of the Congo (DRC) announced in an updated epidemiological briefing on Sunday that the total number of confirmed Ebola cases across the country has crossed the 1,000 threshold, marking a worrisome milestone in the ongoing outbreak.

    Latest official data released by the DRC Ministry of Health puts the current cumulative confirmed caseload at 1,003. As of the update, the outbreak has claimed 254 lives, bringing the overall case fatality rate to 25.3 percent. Of the active cases, 365 patients are currently receiving care in isolation facilities or hospital wards, while 100 people who contracted the virus have successfully recovered and been discharged.

    The outbreak is concentrated across three provinces in the eastern part of the country, where public health teams are working to trace all close contacts of confirmed cases to slow transmission. Current data shows that just 58 percent of identified contacts are successfully being monitored and followed up, a gap that response teams are working to address.

    Even as case numbers continue to climb, health authorities emphasize that all outbreak response operations remain fully active. Response measures include enhanced pathogen surveillance at border crossings and community levels, expanded public outreach and education campaigns to raise awareness of transmission risks, and ongoing work to boost clinical case management and expand diagnostic testing capacity across affected regions. The photo provided, captured on June 16 at an Ebola treatment center in Rwampara, eastern DRC, shows frontline health workers drying disinfected protective gloves ahead of their next shift caring for patients.